
You can tell when an insurance verification form is weak because the problems don't stay at the front desk. A missing member ID, an unconfirmed plan type, or a skipped authorization check turns into a denial later, then billing staff spend time chasing payer portals, calling patients, and correcting claims that should never have gone out incomplete. In a busy practice, that isn't a paperwork problem, it's a revenue cycle problem.
The better way to think about the insurance verification form is as a live operational checkpoint. It should collect the minimum data needed to confirm eligibility, benefits, and authorization status, then feed that information into your EMR, clearinghouse, and front-desk workflow before the visit. For practices that use remote staffing, it also becomes a clean handoff tool for virtual insurance verification specialists who can work inside your systems during clinic hours.
That matters because verification isn't just about whether a patient is “active.” It's about whether the planned service is covered, whether the patient owes a copay or deductible, and whether the visit can move forward without creating avoidable rework. The practices that handle this well don't treat verification as a one-time check. They treat it as a process that starts when the appointment is booked and gets checked again before the patient walks in.
The Operational Reality of Insurance Verification
A front-desk coordinator finishes intake, sees that the patient's insurance card looks familiar, and moves the schedule along. The claim comes back later because the plan had changed, the subscriber ID was keyed wrong, or prior authorization was required and nobody caught it. That's the daily cost of treating verification as a quick administrative task instead of a control point.
Industry reporting cited in 2026 says eligibility and authorization errors account for 23% of initial claim denials, while manual verification can take 15 to 20 minutes per patient compared with 2 to 4 minutes for automated workflows, with a practice handling 80 appointments per week spending about 22 hours weekly on verification in a manual model versus about 4 hours with automation (automating insurance verification in medical practices). That's why the form matters operationally, not just administratively. It gives staff a consistent place to capture the details that determine whether coverage can be confirmed before care is delivered.
Practical rule: if a field won't help you answer an eligibility, benefit, or authorization question, don't let it crowd the form.
For teams that want to see this as a workflow rather than a static intake document, an AI-powered insurance dashboard can help organize exceptions, but the underlying discipline still starts with the form itself. Clean inputs, clear ownership, and a documented review step matter more than any interface.
What the form is really doing
The best version of the form doesn't just gather insurance details. It creates a shared record that front desk, billing, and remote staff can use without guessing. When that record is incomplete, someone has to reconstruct it later from memory, scanned cards, or payer portals.
That's where practices lose time. The form should be designed so every field has a downstream purpose, whether that purpose is an eligibility inquiry, a financial counseling call, or a billing review.
Why Registration Quality Drives Claim Outcomes
A claim usually starts with the registration desk, so any weak field on the insurance verification form can turn into rework later. In Experian Health reporting, 48% of providers said data collected at registration or check-in was somewhat or not accurate, 56% said patient information errors are a primary cause of denied claims, and 22% of patients reported care delays due to insurance verification (Experian Health reporting). Those numbers show the cost of treating registration as a clerical step instead of a revenue control point.
From paper intake to structured data capture
Paper intake was built for collecting information, not for supporting eligibility decisions. Staff wrote down a policy number, scanned a card, and moved on. That approach breaks down once deductibles, referrals, plan rules, and service-specific authorization requirements have to be checked before the visit.
Nearly 60% of providers still use at least two different tools to gather the information needed for claim submission, and 43% said incomplete checks add at least 10 minutes of staff time per eligibility check (Experian Health reporting). That is why the form cannot live as a static PDF. It has to feed the eligibility inquiry, the billing review, and the handoff to remote staff who may be cleaning up exceptions later.
A clean intake process reduces uncertainty before the appointment. A messy one pushes that uncertainty into the claim.
A bad intake form creates work twice, once at registration and again when the claim is reworked.
For practices evaluating broader workflow change, healthcare revenue cycle automation only performs as well as the data it receives at the front desk. Automation can move information faster, but it cannot correct a poorly designed intake process.
What registration quality changes in practice
Clean registration gives billing teams fewer gaps to interpret and gives providers a clearer view of what the patient may owe before care starts. Incomplete registration does the opposite. It turns the claim into a scavenger hunt, with staff pulling details from charts, scanned cards, and payer portals just to rebuild what should have been captured once.
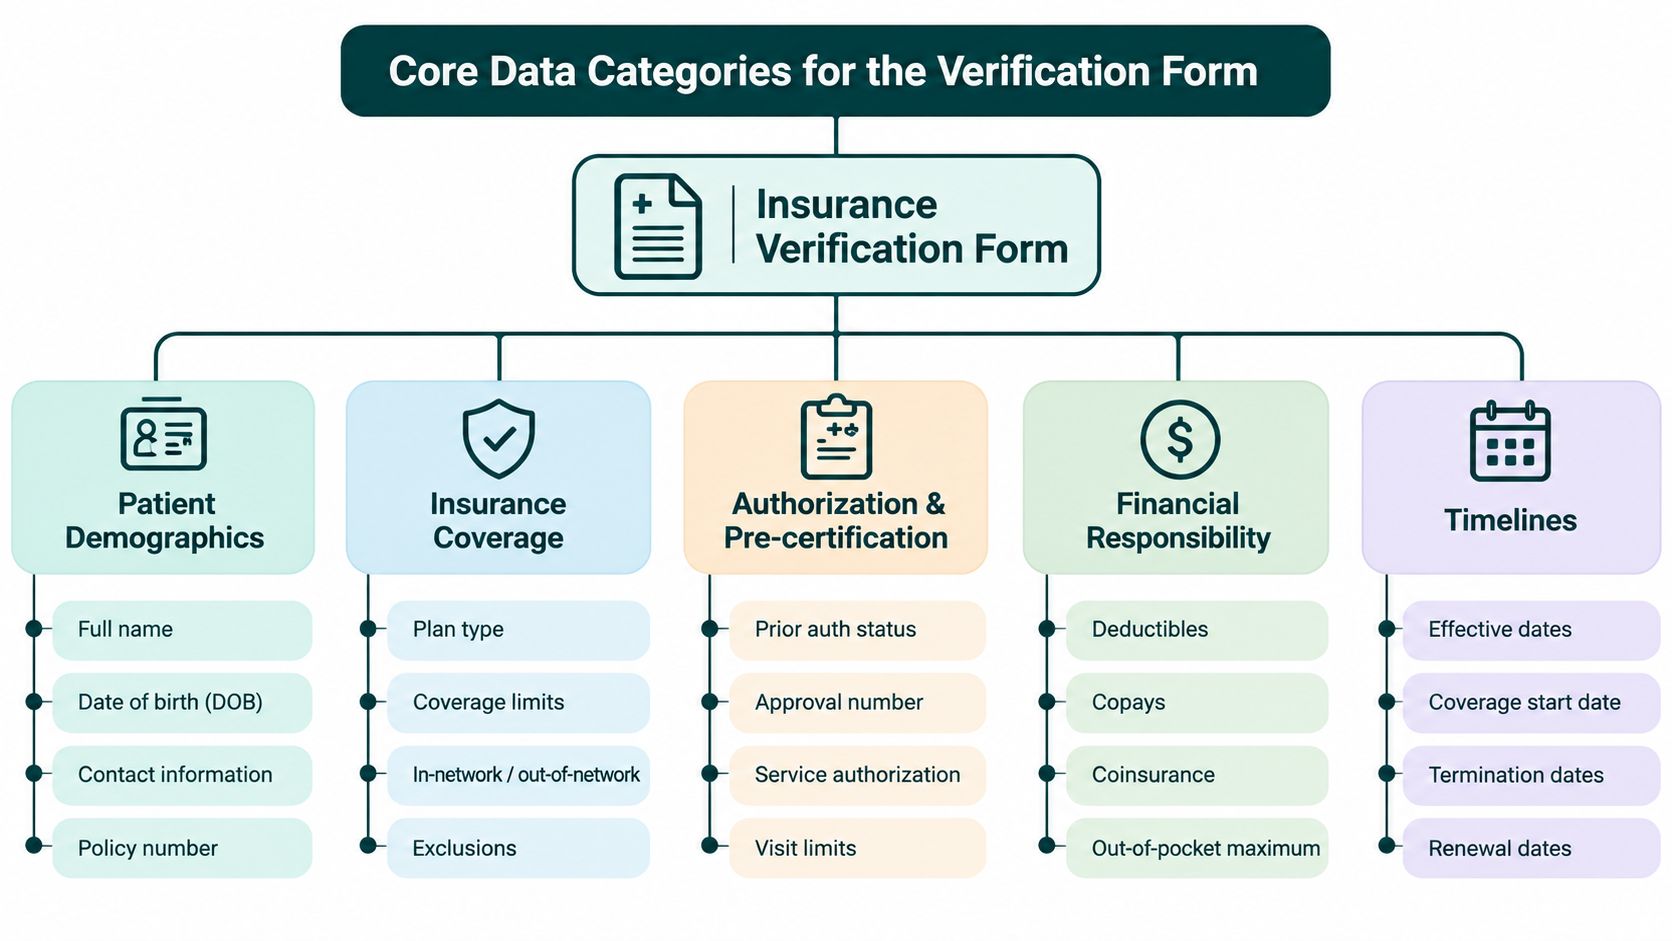
Core Data Categories for the Verification Form
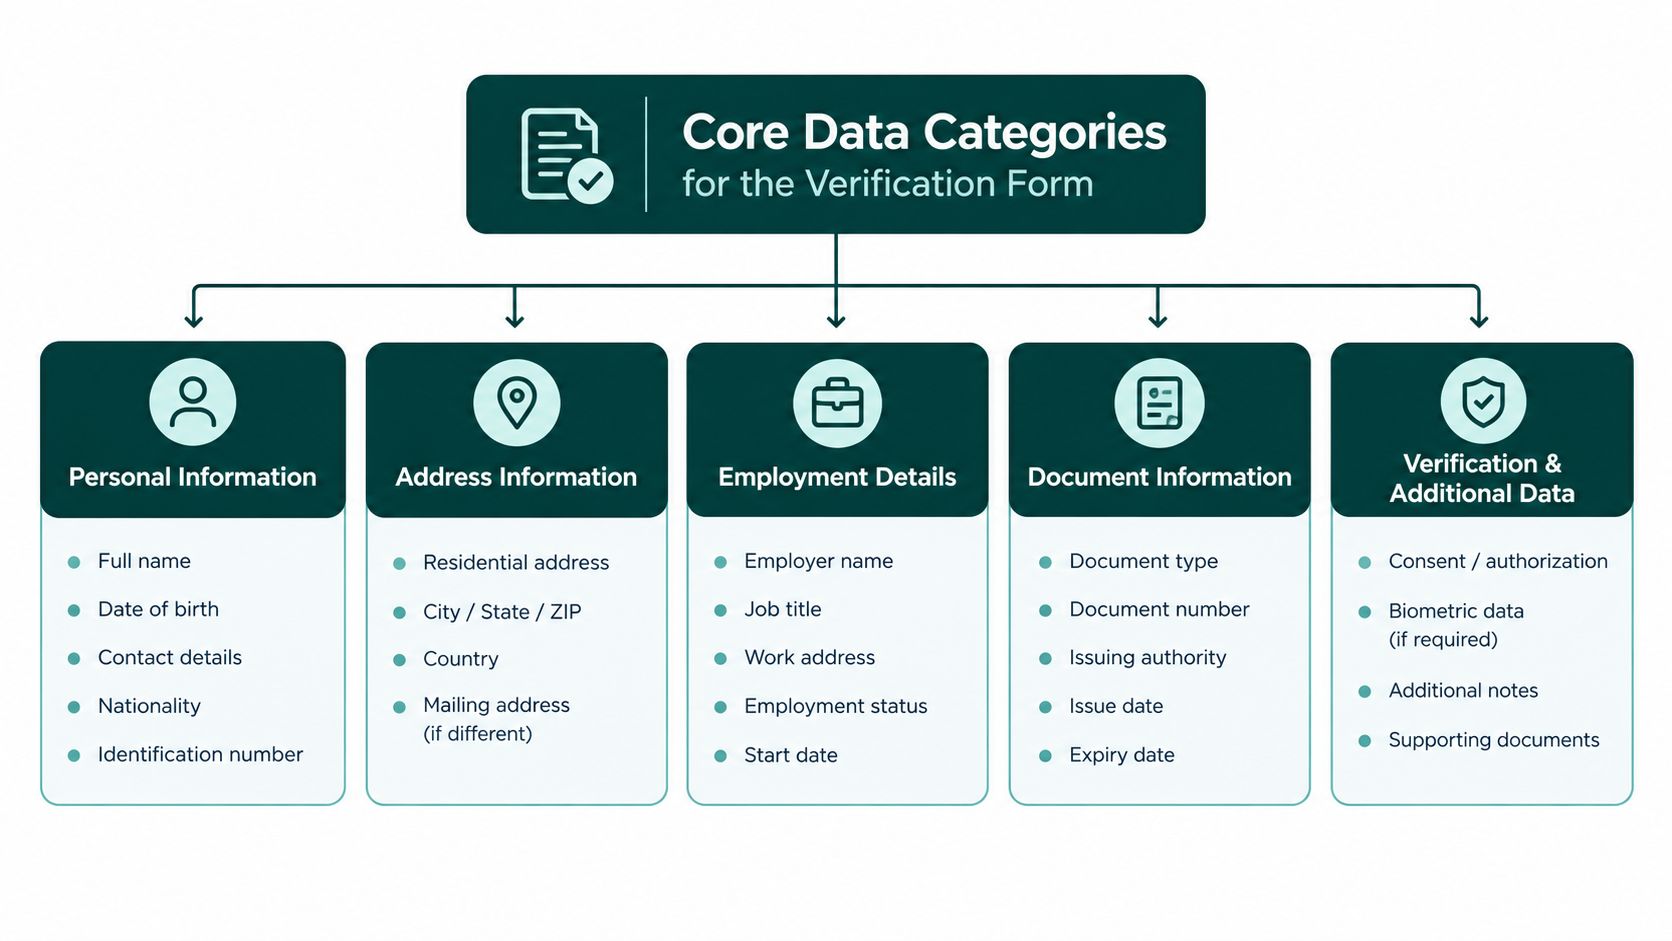
The technical backbone of a U.S. insurance verification form is the HIPAA-standard ASC X12 270/271 eligibility transaction set. The 270 is the inquiry the provider sends, and the 271 is the payer response that confirms active coverage and related benefit details (complete guide to eligibility verification). If your form doesn't capture the fields that support that exchange cleanly, staff end up typing the same information into multiple systems and fixing avoidable errors later.
Identity and subscriber data
Start with the basics that let the payer identify the correct member.
- Patient name and date of birth: these should match the insurance record exactly.
- Subscriber or member ID: this is the core routing field for the eligibility inquiry.
- Dependent versus subscriber relationship: important when the patient isn't the primary member.
- Patient demographics: enough to confirm the member when the ID alone doesn't resolve the record.
Plan and provider data
The form also needs the data that tells the payer which coverage and which provider are involved.
- Plan or payer name
- Policy and group numbers
- Provider NPI
- Date of service
- Service-type code when requesting benefits for a specific category such as mental health or chiropractic care
Service-specific fields
A useful layout separates the form into identity data, subscriber or plan data, and service-specific questions. That structure helps remote staff and front-desk teams map the collected information directly into the eligibility inquiry workflow and reduce mis-keyed entries.
The 271 response can show more than whether coverage is active. It can also support patient financial counseling before the visit by revealing benefit design, network status, and whether the planned service needs authorization. That's why the form should be built for decision-making, not just storage.
Working standard: if a field can't be tied to a 270/271 response, it probably belongs somewhere else in the chart, not on the verification form.
For a practical example, a therapy clinic may need service-type details that a primary care practice doesn't use every day. A multi-specialty group, by contrast, should standardize the core fields but leave room for specialty-specific prompts so staff aren't guessing at the point of entry.
Detailed Benefit and Authorization Entries
A patient arrives with an active plan, yet the claim later denies because the scheduled service needed authorization. The intake record showed eligibility, not complete coverage. A denial-prevention workflow must separate eligibility, benefit coverage, and prior authorization. An eligible patient is not automatically covered for every service, and missing authorization can still invalidate a claim (insurance verification training reference).
The fields that determine patient responsibility
The form should capture the details that affect reimbursement and the amount discussed with the patient before check-in. Record active or inactive coverage, effective and termination dates, plan type, in-network status, copay, deductible, coinsurance, out-of-pocket maximum, coordination of benefits, and authorization requirements (eligibility and benefits guide).
| Form Field Category | Specific Data Points | Denial Risk if Missed |
|---|---|---|
| Coverage status | Active or inactive, effective date, termination date | Claim may be filed to a plan that is no longer valid |
| Plan structure | Plan type, network status, coordination of benefits | Wrong payer or wrong benefit assumptions |
| Patient responsibility | Copay, deductible, coinsurance, out-of-pocket maximum | Patient balance is misquoted, collections get harder |
| Service rules | Referral needs, visit limits, exclusions, authorization requirements | Service may be denied even when the patient is eligible |
Why 48-hour advance verification prevents denials
The verification checkpoint should occur before the appointment, commonly 48 hours in advance. That timing gives staff room to correct a stale insurance card, identify missing authorization, and explain expected out-of-pocket responsibility before the patient arrives.
The form should support an automated 270 inquiry and a structured 271 response, not sit as a separate front-desk document. A remote virtual assistant can submit the inquiry, review benefit and authorization responses, and enter confirmed values into the EMR. Staff can then work from exception flags instead of rekeying every patient record.
Specialty services require closer review. Imaging, behavioral health, chiropractic care, and outpatient procedures may have referral, visit-limit, exclusion, or authorization rules that routine office visits do not. If the form combines “coverage verified” with “service authorized,” staff can close the task after confirming eligibility alone. Keep those statuses separate, with the payer response and verification date recorded in the EMR.
Cross Referencing Verification Across the Patient Journey
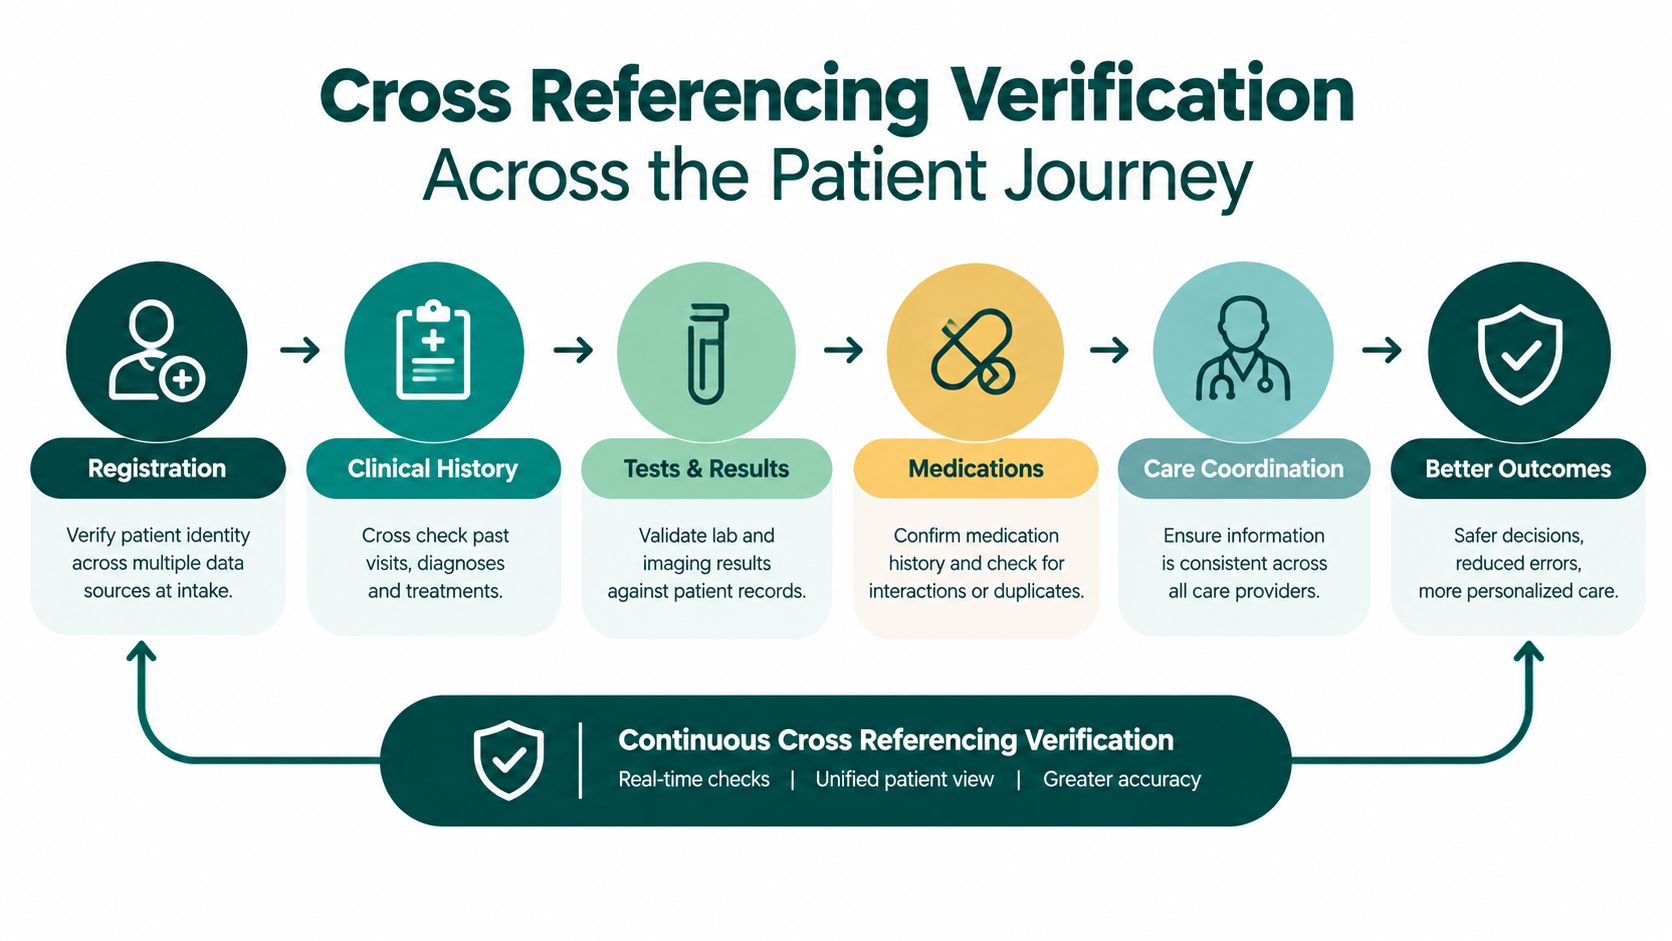
The most reliable verification workflow is not a single check at intake. It's a sequence. Tebra's workflow guidance recommends checking eligibility as soon as the appointment is scheduled, re-checking coverage one to three days before the visit, confirming again at check-in, and escalating to the payer if there are discrepancies or if the service needs prior authorization (patient insurance eligibility verification workflow). That sequence keeps stale data from slipping through.
A practical verification timeline
- At scheduling. Capture the insurance details and run the first eligibility check.
- One to three days before the visit. Re-check the plan, benefits, and authorization status.
- At check-in. Confirm the patient still has the same coverage and that nothing changed since the pre-visit review.
- When there's a mismatch. Escalate directly to the payer or request updated documentation.
This timeline is more than housekeeping. It catches contract-year deductible resets, benefit changes, and payer rule changes before the provider sees the patient. It also gives staff a chance to contact the patient with a clear explanation instead of handing them a surprise balance later.
Where credentialing and verification overlap
For practices that manage specialty care or new payer enrollments, medical credentialing services sit close to this process. Credentialing confirms the provider relationship with the payer, while verification confirms the patient's coverage and plan rules on a given date. Those are separate jobs, but if one is weak, the other gets blamed.
The operational lesson is straightforward. Verification should be rechecked at every point where the coverage picture can change. That's especially true for practices that book out weeks in advance or see patients with evolving benefit designs.
Automating the Form and EMR Integration
Manual retyping is where good verification workflows go to die. A staff member fills out the form on paper, then keys the same information into the EMR, then again into a clearinghouse or payer portal. The risk of mismatch climbs each time the data is copied, especially when the front desk is busy.
What automation should do
Your EMR should trigger an eligibility check when a new appointment is created or when patient demographics change. The best setup uses real-time payer transactions and APIs such as 270/271 to validate active coverage, effective dates, deductible and copay amounts, coordination of benefits, and network status before care is delivered (eligibility checking products). If the system returns an exception, it should flag the record for human review instead of forcing staff to hunt for the problem later.
A simple integration checklist
- Map the form fields to EMR fields so the intake data lands in the right place the first time.
- Trigger eligibility automatically on scheduling and again near the date of service.
- Create exception flags for missing subscriber data, inactive coverage, or authorization requirements.
- Keep a fallback path to payer portals or phone calls when real-time responses aren't available.
- Document the outcome so billing sees what was verified and when.
The value here isn't only speed. It's consistency. A well-configured workflow reduces the number of manual touches and makes it much easier to see where a verification break happened. For that reason, teams that manage multiple systems often benefit from a connectors and data governance guide before they add more automation layers.
When you're building this out, the all skills overview can help you think through what tasks belong in the EMR, what belongs in payer portals, and what can be handed to remote staff without creating confusion.
Delegating Verification to Remote Healthcare Staff
Most practices don't need more people standing at the front desk. They need someone who can work the verification queue without pulling the receptionist away from phones, walk-ins, and check-in traffic. That's where trained remote healthcare staff can make a real difference, especially when they're operating in your EMR and payer portals during clinic hours.
Where remote staff fit best
Insurance verification is a good candidate for delegation because it follows a repeatable process. A virtual insurance verification specialist can check eligibility, review benefits, flag authorization needs, and follow up on discrepancies without interfering with the in-office patient experience. For many practices, the practical gain is less front-desk bottleneck and fewer rushed checks done at the last minute.
MedicalVirtual offers an insurance verification service that places a dedicated specialist inside the practice's PMS and payer portals on a flat monthly basis. Used correctly, that setup supports the same core workflow a strong internal team would run, with the advantage of US-hours coverage and a staffing model built around the practice's schedule.
What to look for in a remote verifier
- Claims and payer familiarity so the person understands benefit language
- EMR navigation comfort so data lands in the right place
- Clear documentation habits so every check is traceable
- Patient communication skill when coverage gaps need explanation
- Escalation discipline when authorization or benefit details are unclear
The trade-off is simple. Remote staffing works well when the practice has a clear process and strong oversight. It works poorly when managers expect the assistant to invent workflow on the fly. Verification is not a judgment-heavy job, but it does require precision and documentation.
If you already have a busy front office, moving verification off the desk can also improve the tone at check-in. The staff member greeting the patient isn't trying to run eligibility in real time while answering the phone.
Quick Reference Checklist for Verification Exceptions
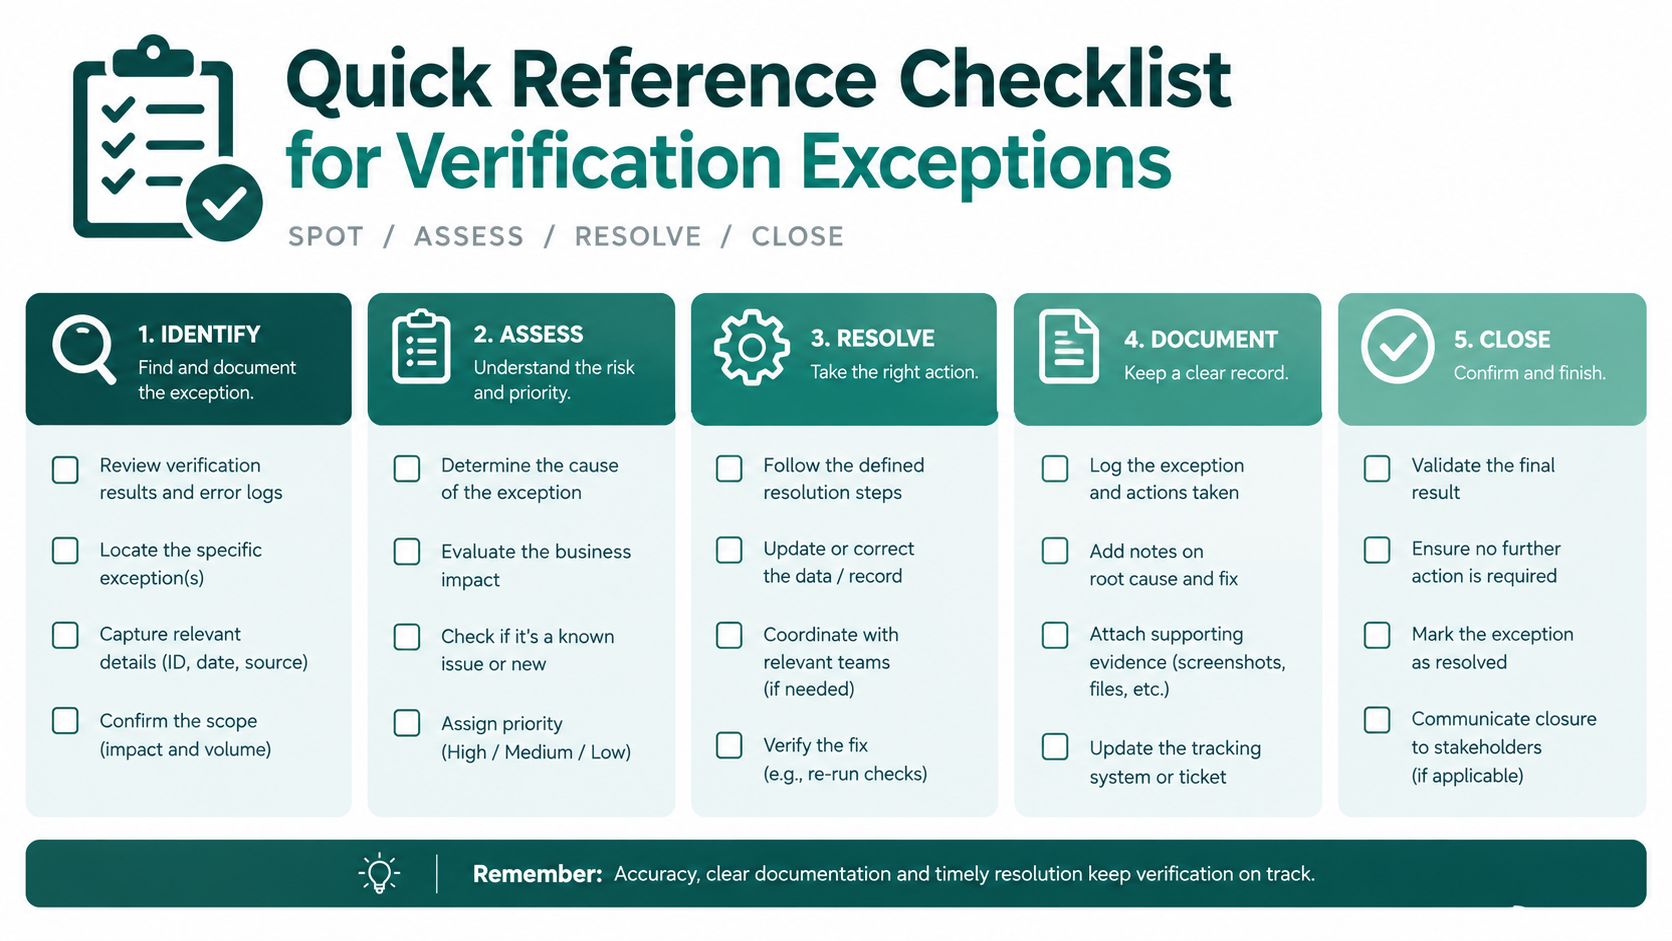
An incomplete electronic response should trigger a defined exception workflow, not a last-minute judgment call. The form should capture each step so front-desk staff, a remote verifier, and the billing team work from the same record.
Verification exception checklist
- Confirm the identity fields again. Compare the patient's name, date of birth, and member ID with the insurance card and EMR record.
- Check whether the issue is eligibility, benefits, or authorization. Active coverage does not confirm payment for the planned service, and missing authorization can still produce a denial.
- Move to the payer portal or phone line. Use the fallback when the electronic 271 response does not return sufficient benefit detail. Record the source and time of the follow-up.
- Verify coordination of benefits. Incorrect primary or secondary coverage can delay reimbursement and assign responsibility to the wrong party.
- Document the patient conversation. If coverage remains uncertain, record what was explained, what needs confirmation, and who owns the next action.
The distinction between eligibility, benefits, and prior authorization belongs in both the form and the exception queue. Staff training should reinforce these separate checks, as shown in this insurance verification training reference.
Operational habit: If the record is incomplete, do not let the patient assume the visit is fully covered. Clear documentation protects the patient, the practice, and the claim.
Recurring visits deserve the same discipline. “Same insurance as last time” is not a verification result. Make exception review part of the daily workflow, with unresolved items visible in the EMR until someone confirms the answer.
The Takeaway
The insurance verification form is not a front-desk convenience. It's a denial-prevention workflow that ties patient intake, eligibility inquiry, benefit review, and authorization checks into one operating system for the practice. When the form is built around the right data, updated before the visit, and connected to the EMR, it helps staff catch problems before they become claim rework.
The practices that get this right don't rely on memory or tribal knowledge. They use a repeatable timeline, clear exception handling, and the right mix of in-office and remote support to keep coverage checks consistent. That's what turns verification from a rushed intake task into a reliable part of the revenue cycle.
If you're still asking front-desk staff to do this between phones, walk-ins, and check-in lines, the process is working against you. Rebuild the form around the workflow, not the other way around.
MedicalVirtual places pre-vetted remote healthcare staff who can handle insurance verification, prior authorization support, and related front-office work inside your systems during clinic hours. If you want to compare that model with your current workflow, visit MedicalVirtual and review how their team fits verification-heavy practices.
A referral is faxed to a specialist, but no one confirms receipt. The patient becomes the messenger between offices, while the primary care team assumes the appointment is progressing. That failure shows why care coordination needs more than communication. Each handoff requires a named owner, a defined next action, and a record that the action occurred.
A patient may schedule an appointment, wait for insurance verification, need a referral, complete intake forms, see a specialist, and require follow-up afterward. Any step can fail independently. Missing approval can delay imaging, an incomplete record can make a provider repeat work, and an unanswered message can leave a clinical question in the wrong queue. The operational cost can include delayed care, avoidable staff time, privacy risk, lost revenue, or a break in continuity.
AHRQ defines care coordination as deliberately organizing patient-care activities and sharing information among everyone involved so care is safer and more effective. In a U.S. medical practice, that work crosses the front desk, referral management, documentation, revenue cycle, behavioral health, and transitions of care. The examples in this article examine who owns each handoff, what information must move, where trained remote staff can help, and which controls protect patients, privacy, revenue, and continuity.
Remote staff can handle administrative and documentation tasks within an approved scope. They cannot diagnose, provide independent clinical advice, or replace licensed judgment. Give them secure system access, documented scripts, clear escalation rules, and a clinical supervisor who remains accountable for decisions. A workable process also states what happens when information is missing, a patient does not respond, or a clinical concern requires immediate review.
Care coordination examples that protect access and revenue
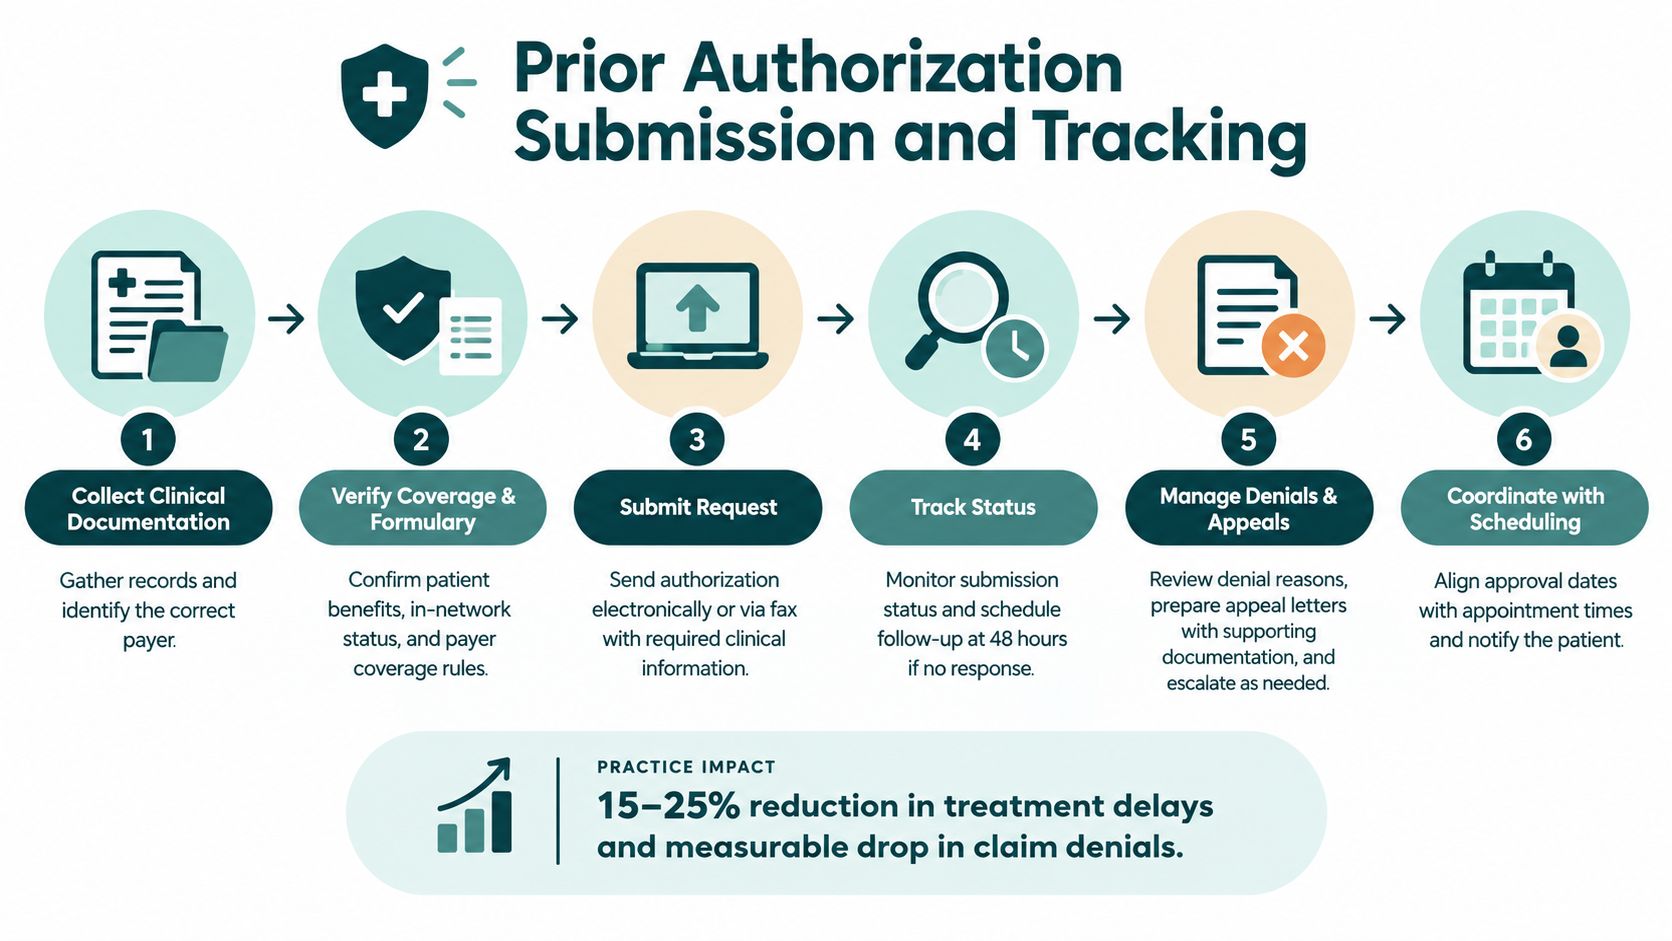
1. Prior authorization submission and tracking
A prior authorization workflow begins when a provider orders a service, medication, or referral that requires payer approval. The ordering provider owns the clinical rationale, while the prior authorization specialist owns the administrative file. That file should contain the order, supporting documentation, diagnosis information, payer requirements, submission record, and next follow-up date.
Submission is only one handoff. The assigned coordinator tracks the request, records payer responses, follows up on delays, and routes missing information to the correct owner. A denial should go to the provider or designated clinical reviewer for a medical-necessity decision, while administrative corrections remain with the authorization team.
A cardiology practice might route an echocardiogram order to a coordinator who confirms payer requirements before scheduling. A behavioral health clinic may check formulary restrictions before a prescribed medication is filled. An orthopedic center may assign a specialist to monitor surgical authorization and prepare the file for a provider-led appeal if the payer denies the request. These workflows protect access, but they also require staff time, documented ownership, and a clear decision about when a case needs clinical review.
Practical rule: An authorization isn't complete until the practice has documented the payer's decision and communicated the result to scheduling, the provider, and the patient.
The tracking dashboard should show the patient, service, payer, submission date, current status, required documents, next follow-up, and escalation owner. A standard checklist reduces avoidable resubmissions. A denial log helps managers identify recurring documentation gaps and payer-specific problems. Remote prior authorization specialists can collect records, submit requests, and track responses through approved systems. Clinical staff must make or approve medical-necessity statements and appeal arguments.
2. Insurance eligibility and benefits verification
Eligibility verification connects the appointment schedule with the payer's current information. Before the visit, an insurance verification specialist confirms active coverage, network status, benefit limitations, copay or deductible information, and whether the planned service needs authorization. The verification result belongs in the electronic medical record or practice-management system, with the date, payer contact details, source of the information, and unresolved uncertainty.
In primary care, the verifier may identify a coverage gap before check-in and alert the patient or manager. In a mental health clinic, the coordinator may confirm behavioral-health benefits and session limitations during intake. Dental, orthodontic, and specialty practices may also need to explain annual maximums or treatment-specific exclusions. Staff should describe what the payer reported without promising that the payer will cover the service.
Use insurance verification services when dedicated capacity is needed for this work, while keeping a firm boundary between verifying benefits and guaranteeing payment. Payer information can change, and a verification call does not remove every claim risk. The practice still owns patient communication, financial policy, and the final decision about how to proceed.
A reliable process includes:
- Standardized capture: Record active status, network information, patient responsibility, limitations, authorization requirements, and the source of the information.
- Manager escalation: Flag new patients, inactive coverage, conflicting payer data, and unusual benefit restrictions for review before the visit.
- Patient-friendly communication: Explain what the payer reported and distinguish an estimate from a final obligation.
- Schedule integration: Place verification in appointment preparation instead of leaving it to the front desk during check-in.
3. Appointment confirmation and reminder workflows
A patient who does not confirm may create an unused appointment slot, delayed care, and avoidable scheduling work. The coordinator owns the outreach record, confirms attendance, provides arrival and preparation instructions, records the patient's response, and alerts scheduling when a cancellation or reschedule creates an open slot. If the patient does not respond, the workflow should specify whether staff send another approved message, call again, or leave the appointment in place.
A primary care practice may ask patients to bring current insurance information. A pediatric clinic may remind a parent about forms or documents needed for a new patient visit. A dermatology practice handling a procedure may use the confirmation call to review preparation instructions that the clinical team has already approved. Remote patient coordinators can manage routine outreach, unanswered messages, rescheduling, waitlist calls, and patients with more complicated preparation needs.
The script should contain only information the practice has authorized staff to communicate. It should identify the appointment, location, arrival expectations, required documents, preparation instructions, and the correct number for clinical questions. Staff should not improvise medical guidance or discuss sensitive details where another person could overhear.
Consent and communication preferences belong in the patient record. Document whether the patient prefers phone, text, portal, or email reminders, and honor opt-out requests. Automated reminders can handle routine confirmations, while staff escalate clinical questions and exceptions to the appropriate team. A virtual phone system can support distributed teams, and you can set up a virtual number affordably without replacing your existing practice line, provided access and recording controls are configured first.
Care coordination examples that prepare the clinical team
4. New patient intake and medical records coordination
New patient intake combines scheduling, forms, insurance, records requests, and chart preparation. The patient intake coordinator sends the appropriate packet after scheduling, follows up on incomplete information, requests records from prior providers, verifies coverage, and enters approved information into the practice system. The clinical team then receives a chart that is ready for review rather than an administrative backlog to solve during the visit.
For primary care, that may include records from previous physicians and a current medication list. A cardiology practice may need prior electrocardiograms, stress-test results, imaging, and referral notes. A mental health clinic may collect screening responses and prior treatment information, while ensuring that sensitive material is routed according to the provider's workflow.
The coordinator shouldn't interpret screening results, reconcile clinical discrepancies independently, or decide which historical condition is clinically significant. Those tasks belong to licensed or designated clinical staff. The remote coordinator can identify missing information, enter data according to approved procedures, and flag allergies, adverse reactions, medications, or other items that require provider attention.
A useful intake control includes:
- One source of truth: Use the patient portal or approved intake system rather than scattered email attachments.
- Records ownership: Assign one person to request, follow up on, receive, index, and route records.
- Exception flags: Mark incomplete forms, conflicting demographics, missing medications, and urgent provider-review items.
- Patient access support: Offer alternatives for patients who have limited portal access or need language assistance.
5. Real-time clinical documentation and EMR note closure
A virtual medical scribe supports care coordination by moving information from the encounter into the electronic medical record while the visit is taking place. The provider remains responsible for the clinical content, assessment, plan, orders, and signature. The scribe documents only within the agreed workflow and should never make an independent diagnosis, change a treatment plan, or sign on the provider's behalf.
In primary care, the scribe may capture the history, medication discussion, examination findings, and plan as the provider speaks. In mental health, the workflow may include session content, treatment-plan updates, and safety-related documentation, with any concern immediately escalated according to the clinic's protocol. In orthopedics, the scribe may organize information from a preoperative or postoperative visit and prepare the note for surgeon review.
AHRQ's care-coordination framework includes communicating information, creating a proactive plan, monitoring follow-up, and supporting self-management. Documentation is the connective tissue that makes those activities visible to the next person on the care team. A note that is drafted quickly but contains unsupported or inaccurate content creates a new safety problem.
Set a specialty-specific template, define how a remote scribe will hear a virtual visit, explain the scribe's role to patients, and require provider review before signing. Quality assurance should include regular spot checks for accuracy, completeness, appropriate attribution, and protection of sensitive information. Same-day closure can be a useful internal target, but the provider's review remains the controlling step.
6. Inbound call triage and message management
Inbound call coordination begins with classification, not clinical advice. A virtual medical receptionist determines whether the caller needs scheduling, records assistance, billing support, a refill message, a nurse callback, or urgent escalation. The receptionist records the reason for the call, relevant details, urgency category, preferred callback method, and destination queue.
A primary care office may route routine appointments to scheduling and symptom questions to a nurse or provider. A pediatric practice may receive calls from parents who need a clinical response rather than a receptionist's opinion. A dermatology clinic may separate cosmetic consultations, urgent concerns, prescription questions, and billing calls into different queues.
The routing tree should be written in plain language. It should tell staff what they can complete, what information they must collect, what they must never advise, and when to escalate immediately. Scripts should also include emergency instructions approved by the practice, without asking unlicensed staff to assess or diagnose the patient.
A remote receptionist can answer calls during clinic hours, manage overflow, document messages, and monitor unresolved items. The practice should review whether the phone system logs calls securely and whether the remote worker can access the correct patient record without seeing unrelated information. A medical receptionist and administrative skills team can support this work when the role is defined around routing and documentation rather than clinical triage.
A fast answer isn't enough. The message must reach the right person with enough context to act.
Care coordination examples that close the loop outside the practice
7. Referral coordination and external provider communication
A referral remains open until the patient receives the outside service, the referring practice receives the result, and a clinician reviews what happens next. Assign one owner to confirm that the receiving office obtained the referral, check appointment status, monitor authorization requirements, and retrieve the specialist's report. The receiving practice needs a corresponding process for returning findings, recommendations, and follow-up instructions to the referring clinician.
Practices still running referral traffic by fax should review the SendItFax healthcare guide for secure transmission options while a portal-based tracking log is put in place. Transmission confirms delivery of a document, not completion of care.
A primary care coordinator might send a cardiology referral with the relevant history, medication list, test results, and clinical question. A gastroenterology practice should return procedure and pathology reports through an approved channel. In behavioral health, a therapist referring a patient to psychiatry needs confirmation that medication management was scheduled, plus a method for notifying the therapist about follow-up needs.
The handoff should identify the information required for the next decision: referral order, clinical question, relevant records, insurance details, authorization status, appointment information, and final report. Administrative staff can check that these items are present and route missing records. They should not reinterpret clinical findings or summarize them in a way that changes the specialist's meaning. The referring provider reviews the report and decides whether treatment, testing, or patient contact is required.
A referral log can show the referral date, destination, authorization status, appointment date, results received, provider review status, and next action. Follow-up timing should reflect clinical priority and payer or specialty requirements rather than one universal interval. A medical credentialing services team may help organize external-provider information and administrative coordination, but credentialing does not replace referral tracking or clinical review.
8. Insurance denial review and appeals
Denial management connects the payer, billing team, clinical documentation staff, coding function, and provider. The denial specialist identifies the reason, such as missing authorization, a coding mismatch, a coverage exclusion, incomplete records, or a medical-necessity question. The practice then chooses the appropriate response: correct and resubmit, appeal, request documentation, or write off the balance under its policy.
A primary care practice may find that referral claims repeatedly lack supporting records. An orthopedic center may route a procedure denial to billing for file assembly and to the surgeon for clinical input. A behavioral health clinic may need a revised workflow when payer-specific telehealth or place-of-service requirements cause recurring denials.
Remote billing assistants can monitor remittance advice, categorize denial reasons, gather records, prepare draft appeal packets, and track deadlines. They should not alter clinical documentation, create unsupported medical-necessity language, or submit an appeal requiring provider attestation without review. Each appeal needs a named owner, a deadline, and a documented next action.
A denial dashboard should show:
- Root cause: Separate preventable process errors from coverage decisions outside the practice's control.
- Payer pattern: Group denials by payer, service, provider, and reason.
- Deadline control: Display appeal and resubmission deadlines.
- Clinical escalation: Send documentation and medical-necessity questions to the appropriate provider.
- Feedback loop: Share recurring problems with scheduling, authorization, coding, and clinical teams.
Recovery dollars matter, but AHRQ identifies coordination measures such as patient confusion, contacts needed to schedule care, unnecessary tests or hospitalizations, and patient hassle in its Care Coordination Measures Atlas. Apply that same lens to denials. Track whether the workflow prevents repeat errors and reduces avoidable contacts for staff and patients.
Care coordination examples for documentation, communication, and continuity
9. Clinical documentation for specialty follow-up
A second documentation scenario appears after the initial visit, when several teams need a consistent account of what happened next. Consider an orthopedic follow-up after imaging or therapy. The provider discusses symptoms, reviews results, changes restrictions, and updates the plan. A documentation specialist can prepare the note, attach the correct report, route orders, and place the chart in the provider's review queue.
This differs from general visit scribing because the handoff may involve outside imaging, physical therapy, surgery scheduling, and the primary care physician. The note must make the next step clear. It should distinguish completed actions from pending actions and identify which team is expected to contact the patient.
A remote scribe can support note preparation and EMR navigation when the practice gives that person controlled access and a defined template. The provider must confirm the clinical content, sign the note, approve orders, and make decisions about treatment. In mental health, additional care is needed around highly sensitive notes, proxy access, and the handling of safety-related information.
The operating control is a pending-action queue. It should show the patient, action, responsible person, due point, and completion status. Without that queue, a well-written note can still leave an imaging order, therapy referral, or patient callback unaddressed.
10. Message management across clinical and administrative queues
A message can begin as an administrative request and become a clinical issue. A patient may call to reschedule, mention a medication problem, ask about a test result, and request a work note in the same conversation. The receptionist needs a method for separating those requests, documenting them accurately, and routing each one to the correct queue.
The practice manager should define categories for scheduling, medication, results, records, billing, forms, referrals, and urgent concerns. Each category needs an owner, a response expectation, and an escalation path. The remote staff member can collect information and route the message, but shouldn't decide whether symptoms are benign, whether a medication should change, or whether a result is normal.
A secure phone and messaging system should identify the patient correctly and minimize unnecessary disclosure. Staff should verify identity using the practice's approved process before discussing protected information. They should also avoid copying sensitive details into unsecured notes or personal devices.
A daily queue review catches messages that were routed incorrectly or left without a response. Managers should sample completed messages for clarity and check whether the receiving clinician had enough information to act. The goal is not just fewer calls. It's fewer unresolved handoffs and fewer patients repeating the same request.
11. Referral results and closed-loop communication
Referral coordination deserves a separate workflow for the return journey. Sending the patient to a specialist is only the outbound half. The practice must know whether the appointment occurred, whether the report arrived, whether the referring provider reviewed it, and whether the patient received the next instruction.
CMS illustrates this connected model with a patient whose emergency-department records, test results, and new medication enter the electronic health record, trigger an alert to the primary care physician, support a cardiology referral, and lead to a later primary-care check-in after chart review. The example shows why care coordination depends on information moving across settings, not merely on assigning a task.
The receiving practice should use a results queue rather than relying on a report to land unnoticed in an inbox. A medical records specialist can index the report, match it to the correct patient and referral, route it to the provider, and record that review occurred. The provider then determines whether the plan changes and whether another message or appointment is required.
Remote administrative staff can also contact the specialist office when a report is missing and notify the patient that the practice is still working to obtain it. They shouldn't interpret the report or communicate clinical conclusions without provider-approved language. A referral is closed only when the necessary result has been received, reviewed, and connected to the next action.
Care coordination examples for transitions and patient financial support
12. Patient payments, self-pay collection, and account resolution
Patient payment coordination involves more than asking for money. The billing assistant explains the account, confirms that charges and insurance activity are documented, identifies questions requiring billing review, and applies the practice's financial-assistance and payment-plan policies consistently. The patient should understand what the practice is requesting and whom to contact if the account appears incorrect.
A primary care practice may assign an assistant to contact patients about aging balances and document each conversation. A specialty clinic may review expected out-of-pocket responsibility before a procedure. A community health center may screen for available hardship assistance and connect eligible patients with the appropriate program or community resource.
Remote billing staff can send statements, answer approved account questions, record payment arrangements, process payments through authorized systems, and escalate disputes. They shouldn't make undocumented promises, waive balances outside policy, or pressure patients who may qualify for assistance. Clear scripts help, but empathy and accurate account information matter more than aggressive collection language.
Controls should include:
- Written arrangements: Record the agreed terms and provide the patient with confirmation.
- Multiple payment channels: Use the practice's approved portal, phone, or mail options.
- Hardship pathway: Train staff to identify when a financial counselor or manager should review the account.
- Audit trail: Document contacts, disputes, payments, adjustments, and escalations.
- Privacy protection: Limit account access to the information needed for the assigned task.
13. Post-discharge transition follow-up
Discharge follow-up is one of the clearest care coordination examples because the patient moves from a hospital or facility back into community care. The practice needs a discharge notification, summary, medication changes, follow-up recommendations, and a named person responsible for contacting the patient or caregiver. That owner confirms what the patient understands, identifies barriers, and routes clinical concerns to a nurse or provider.
The historical need is substantial. A federal review reported that about 19% of Medicare hospital admissions resulted in readmission within 30 days, avoidable rehospitalizations in 2004 cost Medicare $17.4 billion, and nearly 31% of Medicare beneficiaries discharged from hospitals experienced two or more transfers to different care settings. These figures explain why medication reconciliation, discharge calls, referral scheduling, and communication with post-acute providers became central coordination tasks. The federal review of care transitions provides the historical context.
A remote coordinator can monitor an approved worklist, obtain missing discharge documents, contact the patient, schedule the follow-up visit, confirm medication access, and document barriers. The coordinator must escalate symptoms, medication discrepancies, or safety concerns according to the practice's clinical protocol. A provider or qualified clinical staff member remains responsible for clinical assessment and decisions.
14. Multidisciplinary transition planning
Some patients move among primary care, specialists, behavioral health, home services, pharmacies, and community organizations. A multidisciplinary transition plan gives each participant the same current information, including the patient's goals, medication list, follow-up appointments, pending tests, responsible clinician, and unresolved barriers.
The STAAR program at Massachusetts General Hospital combined reliability-focused discharge processes, cross-team communication, and post-discharge follow-up. Over a four-year implementation period, its reported 30-day readmission rate fell from 21.0% before the intervention to 14.5% afterward, a 30% relative decrease. The BMJ Innovations report on the STAAR program describes the intervention and its results.
The lesson for a smaller practice isn't to copy the hospital program wholesale. It's to make the handoff reliable enough that a patient doesn't become the sole messenger between organizations. A remote medical records specialist or patient coordinator can assemble the transition packet, confirm receipt, maintain the task list, and document outreach. The clinical team must establish the care plan, determine escalation thresholds, and review changes.
The network outside the clinic can be the hardest part. A 2026 Commonwealth Fund comparison across 10 countries reported that most primary care physicians didn't receive specialist reports within a week, and roughly four in 10 U.S. primary care physicians identified limited information about community providers as a major barrier when coordinating with social services. The Commonwealth Fund comparison of care coordination across 10 countries highlights why electronic connectivity alone doesn't guarantee timely communication.
12-Point Care Coordination Comparison
A useful comparison asks more than whether a workflow saves time. It identifies who owns the handoff, which information must move, where remote administrative staff can assist, and which control keeps clinical decisions with licensed staff. The table below compares twelve workflows without assigning unsupported performance percentages.
| Workflow | Implementation complexity | Handoff owner and information | Remote support | Controls and practical value |
|---|---|---|---|---|
| Prior Authorization Submission and Tracking | High, payer rules and multiple steps | Authorization specialist owns status; clinical team supplies diagnosis, order, and rationale | Submit requests, monitor portals, document payer responses | Provider approval, deadline tracking, fewer avoidable treatment delays |
| Insurance Eligibility and Benefits Verification | Moderate, payer systems vary | Verification staff owns the check; front desk receives coverage and cost details | Confirm eligibility, record benefits, flag uncertainty | Verify before service, protect privacy, reduce claim and billing disputes |
| Appointment Confirmation and Reminder Workflows | Low to moderate | Scheduling team owns contact preferences and appointment status | Send approved reminders, record responses, offer open slots | Consent-based messaging, accurate schedules, better slot utilization |
| New Patient Intake and Records Coordination | Moderate, several information sources | Intake coordinator owns completeness; clinician reviews history | Send forms, request records, index documents, flag gaps | Identity checks, minimum necessary access, prepared charts |
| Clinical Documentation and EMR Note Closure | Moderate to high, training and review required | Provider owns the note; scribe supports documentation | Draft notes, organize dictated content, route for signature | Provider review, access controls, clear correction process |
| Inbound Calls and Message Management | Low to moderate | Reception team owns routing; clinician owns clinical response | Capture caller details, schedule, document, and route messages | Escalation rules, message timestamps, no independent diagnosis |
| Referral Coordination and External Provider Communication | Moderate, outside offices may respond differently | Referral coordinator tracks the order and report; ordering clinician reviews findings | Send records, confirm receipt, monitor outstanding reports | Referral log, consent checks, escalation for missing results |
| Denial Review and Appeals | High, coding and clinical documentation may both matter | Billing lead owns the case; clinician supports medical rationale | Categorize denials, assemble records, track appeal deadlines | Coding review, provider sign-off, audit trail |
| Patient Payments and Account Resolution | Moderate, financial and privacy controls apply | Billing team owns balances; financial staff handles patient questions | Process payments, explain statements, document arrangements | PCI-compliant tools, identity verification, hardship escalation |
| Lab and Imaging Result Follow-Up | Moderate, results require clinical interpretation | Ordering clinician owns review and patient communication | Monitor incoming results, route abnormal flags, document outreach attempts | No result interpretation by remote staff, closed-loop status |
| Care Plan Task Tracking | Moderate, multiple roles share work | Care manager or designated clinician assigns tasks and due dates | Maintain task queues, send reminders, record completion | Named owner per task, overdue escalation, current plan in the EMR |
| Medication Refill Coordination | Moderate, refill rules and clinical review apply | Prescribing clinician owns approval; staff verifies request details | Collect pharmacy and medication information, route refill requests | Medication reconciliation, allergy checks, clinician authorization |
Remote staff can maintain queues, gather information, and document activity. They should not approve treatment, interpret results, promise coverage, or resolve clinical uncertainty. Each workflow needs a named owner, a documented handoff, and an escalation path that the practice can audit.
How to assign remote staff without weakening clinical control
Remote healthcare staff are most useful when the practice separates coordination work from clinical authority. A patient intake coordinator can request records, but a provider decides what those records mean. An insurance verification specialist can report payer information, but shouldn't guarantee coverage. A virtual receptionist can identify an urgent-sounding message and escalate it, but shouldn't triage the condition independently.
A practical role map can look like this:
- Virtual medical receptionist: Answers calls, schedules visits, confirms appointments, documents messages, and routes clinical questions.
- Patient intake coordinator: Sends forms, follows up on missing information, requests records, and prepares the chart.
- Insurance verification specialist: Checks eligibility and benefits, records payer information, and flags uncertainty.
- Prior authorization specialist: Submits and tracks requests, gathers documentation, and escalates clinical questions.
- Medical records specialist: Indexes records, tracks referrals, obtains missing reports, and manages document queues.
- Medical billing assistant: Reviews denials, follows payer activity, manages statements, and documents account resolution.
- Virtual medical scribe: Drafts encounter documentation in the EMR for provider review and signature.
The practice should limit each role's access to the systems and patient information needed for its work. Use individual logins, appropriate permissions, secure communication channels, documented training, and periodic access reviews. A Business Associate Agreement should be in place where applicable, and the practice should confirm its obligations with qualified compliance counsel. HIPAA alignment or training doesn't mean a vendor or employee is officially “HIPAA certified,” because HHS doesn't recognize an official HIPAA certification.
Before assigning a workflow, write the escalation rule in a form a new employee can follow. For example, “route all medication discrepancies to the nurse queue,” or “don't communicate a denial appeal outcome until the billing manager approves the message.” The rule should identify the destination, required information, urgency, and backup owner.
How to measure whether care coordination actually happened
Task completion alone can create a false sense of control. A referral may be marked sent even though the specialist never received it. A post-discharge call may be logged even though the patient couldn't explain the medication plan. A message may be closed without documenting who reviewed the result or what happens next.
AHRQ's care-coordination measurement framework maps operational activity to specific questions. It includes establishing accountability, communicating information, facilitating transitions, assessing needs and goals, creating a proactive plan, monitoring follow-up, supporting self-management, linking patients to community resources, and aligning resources with patient and population needs. AHRQ's care-coordination activities framework gives practices a useful structure for assigning ownership.
Track a small set of measures tied to the workflow:
- Completion: Was the referral received, appointment scheduled, report returned, or follow-up completed?
- Turnaround time: How long did the handoff take from initiation to the next confirmed action?
- Exception rate: How often did the workflow require escalation, resubmission, correction, or manager intervention?
- Patient friction: Did patients need repeated contacts, clarify confusing instructions, or report unnecessary hassle?
- Clinical review: Did the authorized clinician review the information and document the next decision?
For remote teams, process measures are especially valuable because they show whether added capacity is improving reliability rather than merely moving work to another queue. Review the data by specialty, payer, provider, and workflow. A measure that improves one department while increasing unresolved work elsewhere isn't a complete operational improvement.
Common implementation failures in medical practices
Care coordination usually breaks at boundaries. The referral coordinator assumes the specialist will send results automatically. The front desk assumes the nurse saw the message. The billing team assumes the authorization was recorded in the order. The patient assumes someone is watching the next step. Each assumption creates a gap.
Another failure is assigning work without giving the person authority to complete the administrative portion. If a coordinator can't access the payer portal, referral inbox, or records system, the workflow still depends on a busy clinician. If a scribe has no template or provider review window, documentation accumulates despite the extra staffing.
Avoid these patterns:
- Unowned queues: Every queue needs a primary owner and backup.
- Hidden exceptions: Staff need a visible place to record failed calls, missing records, payer delays, and patient barriers.
- Unclear clinical boundaries: Remote staff need written instructions for what to route and what they must never decide.
- Duplicate documentation: Decide where the authoritative status lives so employees don't maintain conflicting spreadsheets and notes.
- No feedback loop: Review recurring errors with the team that creates the originating information.
- Overreliance on automation: Automated reminders and alerts can support the process, but they don't replace judgment, patient contact, or closed-loop confirmation.
Start with one high-friction workflow rather than staffing every administrative function at once. Map the current steps, identify the most common failure point, assign each handoff, define the escalation boundary, and measure completion, turnaround time, and exceptions. Expand only after the practice can explain what improved and what still requires redesign.
The Takeaway
The strongest care coordination examples have the same operating features. They protect access and safety through clear call-routing and escalation rules, prevent delays through intake, eligibility, authorization, and referral tracking, and strengthen continuity through accurate documentation and closed-loop communication. The work is distributed, but accountability isn't vague.
Practice managers should choose one workflow that regularly creates delays or repeated contacts. Assign every handoff to a defined role, document what information must move, establish the point where licensed staff must review or decide, and measure completion, turnaround time, and exception rates before expanding support.
Remote roles such as virtual receptionists, patient intake coordinators, insurance verification specialists, prior authorization specialists, medical records specialists, billing assistants, and scribes can support these workflows when access controls, training, secure systems, provider review, and an appropriate Business Associate Agreement are in place. They can increase operational capacity without replacing clinical judgment or licensed care.
MedicalVirtual connects U.S. medical practices with pre-vetted LATAM healthcare talent aligned with U.S. clinic hours, including staff for reception, intake, documentation, revenue-cycle work, and care coordination. If you're evaluating remote support for one of these workflows, review the available roles and discuss a scope that keeps administrative ownership clear while leaving medical decisions with your clinicians.
MedicalVirtual offers pre-vetted LATAM healthcare staff who can work within your clinic hours and support calls, intake, referrals, documentation, prior authorization, insurance verification, and billing workflows. Visit MedicalVirtual to evaluate a role around the handoff your practice most needs to stabilize.
The dental front office is the clinic's revenue-control hub, where every unanswered call and unverified benefit can translate directly into lost production. No-show rates have been reported from 13.5% to 48%, with an estimated average of 23% across studies, so front-office systems must protect both patient access and chair utilization (systematic review of dental appointment no-shows).
A busy morning makes the problem obvious. One patient is checking in, another is calling about an insurance estimate, a hygienist needs a chart updated, and the phone keeps ringing. If the team treats reception as a collection of disconnected errands, calls go unanswered, benefits remain unclear, cancellations create empty chairs, and patients leave with financial questions instead of a clear next step. A well-run dental front office works differently. It manages intake, scheduling, communication, insurance, documentation, and payment as one operating system.
This guide explains how to build that system, when in-house staffing makes sense, where virtual medical assistants can extend coverage, and how to protect patient information while remote staff work inside practice workflows. The objective isn't to make the front desk busier. It's to give every task a defined owner, a reliable handoff, and a measurable effect on access, production, and staff workload.
The Strategic Role of the Dental Front Office
The dental front office controls the patient journey before treatment starts and after the patient leaves. A scheduler determines whether a new caller reaches a provider's calendar. An insurance specialist determines whether the patient understands expected responsibility before treatment. A checkout coordinator determines whether the next appointment is secured and whether the financial conversation ends clearly.
Those actions directly affect revenue control. A missed call can mean a lost new-patient opportunity, an unrecovered cancellation, or a question that never reaches the right team member. An incomplete benefit check can lead to a surprise balance, a disputed estimate, or a claim problem later. The front desk doesn't produce the clinical service, but it determines whether the practice has the information, attendance, and financial coordination needed to deliver it efficiently.
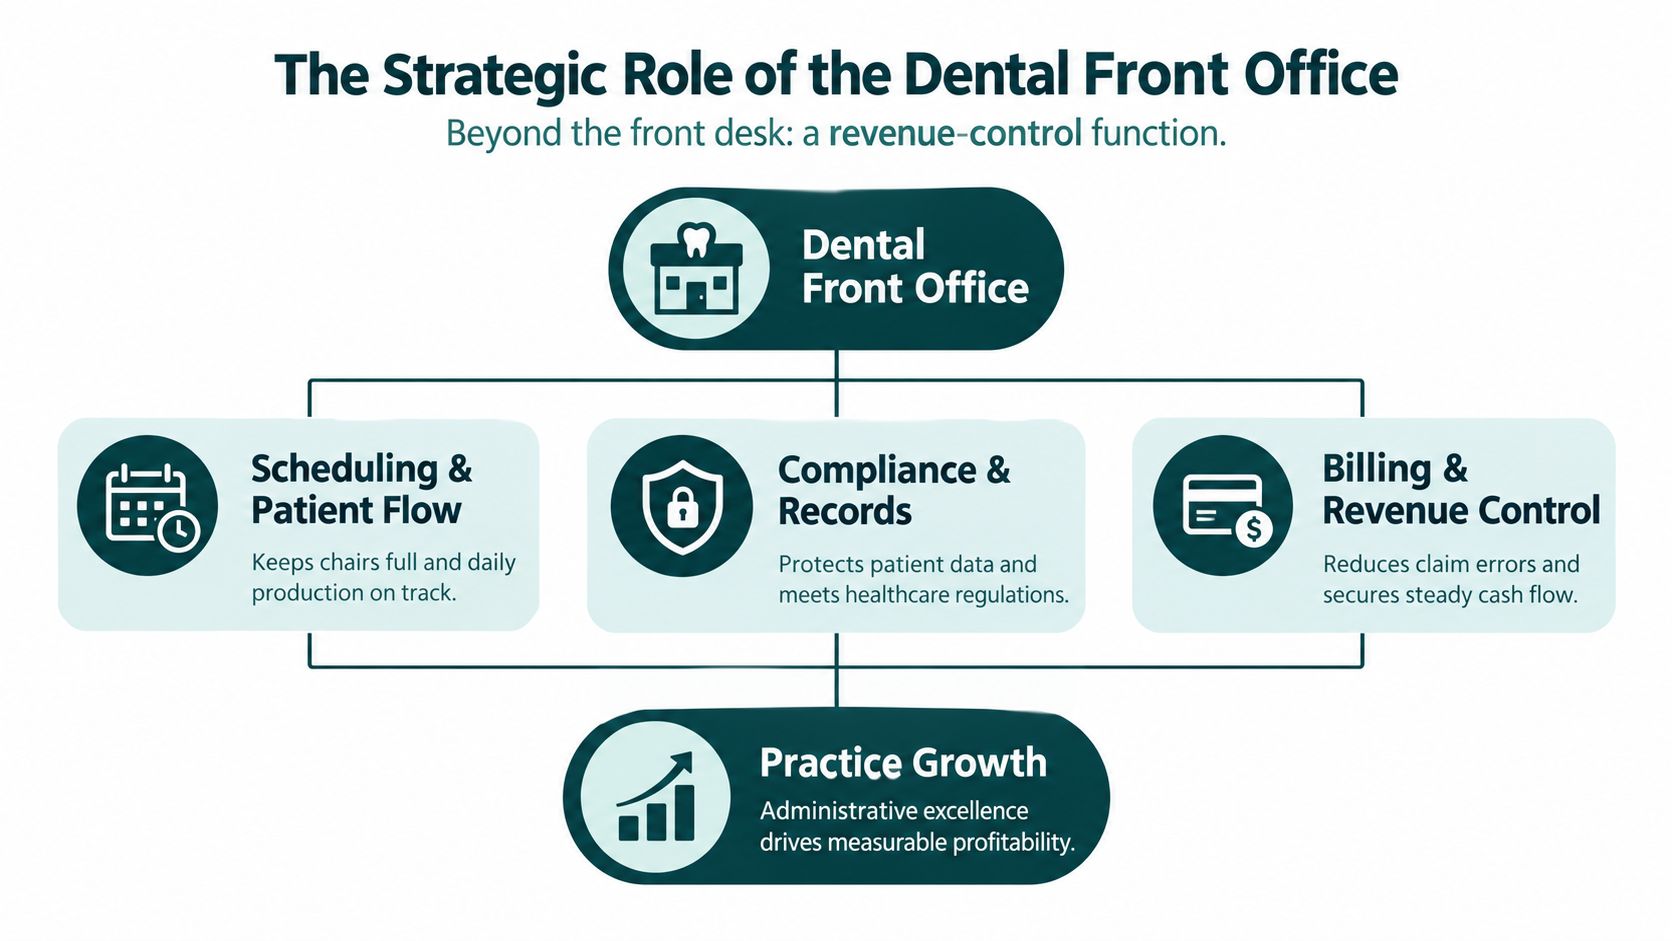
From reception to revenue control
Start by assigning ownership to the moments that influence production:
- First contact: Answer or return calls promptly, identify the caller's need, and move appropriate new-patient conversations toward an appointment.
- Pre-visit preparation: Collect forms, confirm demographics, request records, and verify benefits before the patient arrives.
- Schedule protection: Confirm upcoming visits, manage the waitlist, and offer open times to patients who can come in sooner.
- Checkout and follow-up: Schedule the next visit, explain the balance, document unresolved questions, and route clinical matters to licensed staff.
This structure also clarifies performance conversations. Instead of telling a receptionist to “be more organized,” a manager can ask whether same-day call returns are assigned, whether incomplete insurance checks appear on a work queue, and whether cancellations are offered to a defined waitlist. Specific ownership produces better coaching than general criticism.
Practical rule: If a front-office task can change whether a patient books, attends, accepts a financial plan, or pays correctly, manage it as an operational control, not an informal favor.
The model applies across specialties, but the emphasis changes. General dentistry often needs tight recall and hygiene scheduling. Orthodontic offices manage longer treatment relationships, recurring visits, and benefit limitations that can affect estimates over time. Pediatric practices need communication that works for both the child's caregiver and the clinical team. In each case, the front office should be designed around the patient journey, not just around who happens to be available at the desk.
For practices considering extended coverage, a dental and orthodontic practice support model can include reception, scheduling, reminders, intake, and administrative follow-up. The right arrangement depends on the practice's call pattern, software, hours, and privacy controls. Remote support can extend capacity, but it doesn't remove the need for clear escalation rules or accountable on-site leadership.
Core Front-Office Workflows Explained
A reliable dental front office depends on repeatable workflows. Staff shouldn't have to reconstruct the process every time a new patient calls, a cancellation appears, or an insurer gives an unclear answer. The following four workflows form the operational backbone.
Patient intake and first contact
The first call should produce more than a name and phone number. The team needs to identify the reason for the visit, preferred timing, relevant history the practice requires, referral information when applicable, and the next action. The staff member should also distinguish administrative questions from symptoms or urgent concerns that require clinical triage.
Call handling has two separate controls: answer rate and conversion quality. One analysis reports that practices answer about 75% to 80% of calls, while missed-call-focused reports place unanswered inbound calls at roughly 20% to 25%. Some top-performing clinics exceed 90% answer rates, and some benchmarks indicate that only about half of answered new-patient calls become scheduled appointments (dental call-handling benchmarks). The practical lesson is simple. A person or system must answer, but answering alone isn't enough. Staff need a consistent discovery and booking script.
Insurance verification and financial clarity
Eligibility verification should happen early enough for the practice to interpret benefits and communicate likely patient responsibility before treatment. The American Dental Association's eligibility verification guidance explains that verification on the date of service helps avoid future recoupment requests and commonly involves payer portals or the number on the patient ID card.
A complete workflow records the payer, member and group information, subscriber details, eligibility status, deductibles, frequency limits, annual maximum information, and procedure-specific restrictions when available. Verification isn't a promise of payment. It gives the practice a documented basis for an estimate and a reason to explain uncertainty when a payer's response is incomplete or benefits may change.
Current coverage identifies real-time insurance verification as a major daily operational challenge for dental practices, with 71% naming it their primary challenge in the cited 2026 coverage (dental insurance verification operations). That finding reinforces why verification deserves a queue, quality checks, and escalation path rather than being left to whoever has a spare moment.
Scheduling, confirmations, and recovery
Scheduling is a production-control process. The scheduler balances provider availability, procedure length, patient preferences, emergency access, and the likelihood that an opening can be filled. A cancellation list is only useful when it contains current preferences and when someone actively contacts appropriate patients.
Reminder design should match patient risk and preference. A randomized study of 13,505 outpatient appointments found no-show rates of 13.6% with a clinic staff reminder, 17.3% with an automated reminder, and 23.1% with no reminder (randomized reminder study00108-7/fulltext)). A private orthodontic study covering 1,193 appointments reported an average no-show rate of 2.43%, with phone calls at 3.49%, email at 2.68%, and SMS at 1.90%, although the differences weren't statistically significant (orthodontic appointment reminder study). Use automation for consistency, but reserve live outreach for high-risk visits, complex appointments, and schedule-recovery opportunities.
Tools can help with overflow and documentation. For example, practices evaluating automated call coverage can review Officehand AI Receptionist features alongside their requirements for escalation, scheduling access, call notes, and human follow-up. Technology should support the workflow, not create a second inbox that staff forget to monitor.
Checkout, claims, and follow-up
The appointment doesn't end when the patient leaves the chair. Checkout staff should confirm the next visit, collect according to the practice's financial policy, document unresolved questions, and route clinical explanations to the appropriate provider or team member. Billing support then works from accurate demographics, insurance data, procedure details, and documentation.
Practices can assign these tasks to one person or split them across roles. The choice matters less than the handoff. A claim queue should show what is missing, who owns the next step, and when follow-up is due. Without that visibility, front-office errors become delayed claims, patient calls, and avoidable rework.
For practices that need a dedicated process, insurance verification services can be evaluated as an extension of the existing team. Before assigning access, define which benefits must be checked, how findings are documented, what requires same-day rechecking, and who approves patient estimates.
Staffing Models and Virtual Support
The staffing decision should begin with workload, not ideology. An on-site employee may be essential for greeting patients, collecting documents, managing walk-ins, and coordinating with clinical staff in real time. A remote assistant may be more useful for call overflow, pre-visit verification, recall, confirmation campaigns, billing follow-up, or work that accumulates after the reception area becomes busy.
A hybrid structure often separates in-person presence from administrative throughput. The person at the desk handles immediate patient-facing needs. A remote team member works a defined queue and protects the tasks that otherwise get postponed. A fully remote model can work for practices with strong digital intake and limited walk-in traffic, but it requires dependable phone, scheduling, documentation, escalation, and privacy processes.
Staffing Model Comparison
| Feature | In-House Front Desk | Virtual Medical Assistant |
|---|---|---|
| Patient greeting | Directly manages arrivals, forms, payments, and face-to-face concerns | Doesn't replace the physical reception function |
| Phone coverage | Strong during staffed hours, vulnerable when the employee is helping a patient or away from the desk | Can focus on calls and callbacks during agreed clinic hours |
| Insurance work | Convenient when the team is already familiar with local workflows | Useful for dedicated eligibility and benefits queues |
| Schedule recovery | Can coordinate immediately with the clinical team | Can work waitlists, confirmations, and cancellation follow-up without standing at reception |
| Training | Practice controls onboarding, coaching, and daily supervision | Requires structured onboarding, access controls, documentation standards, and quality review |
| Privacy | Easier to observe the physical work environment, but local mistakes still create risk | Requires careful vendor review, written agreements, secure systems, and limited access |
| Best fit | High walk-in volume and constant in-person coordination | Repetitive administrative work, overflow coverage, and defined remote queues |
| Main trade-off | Higher fixed staffing commitment and coverage gaps during interruptions | Less physical presence and more dependence on process design and communication |
How to choose the model
Map the work for several ordinary days before deciding. Count unanswered calls, unworked voicemails, incomplete benefit checks, unconfirmed appointments, unresolved patient messages, and claims or balances waiting for follow-up. The point isn't to create a complicated dashboard. It's to identify work that is both repetitive and financially consequential.
A remote role should have a narrow initial scope. For example, an assistant might begin with confirmations, recall calls, and insurance verification, while the on-site team retains check-in, checkout, and clinical escalation. Once the handoffs are stable, the practice can add billing support or prior-authorization coordination.
Remote access also creates obligations. A person who can view protected health information isn't merely helping with scheduling. The practice must decide what systems the person may use, what information is necessary, how incidents are reported, and how supervisors review work. HIPAA requirements and state obligations can vary, so confirm the arrangement with qualified compliance or legal counsel.
Real-World Front-Office Scenarios
A dental front office proves its value during interruptions, not during quiet periods. The following scenarios are illustrative, but the operational patterns are common.
The unanswered new-patient call
The receptionist is checking in a child when a prospective patient calls. The caller reaches voicemail and doesn't leave a message. A practical recovery process assigns the missed call to a same-day callback queue, records the source and reason for calling when known, and gives the caller a clear path to schedule.
The callback shouldn't begin with a generic apology. Staff can confirm whether the caller is seeking an exam, an emergency visit, a specialty consultation, or information about an existing appointment. That short discovery step determines the correct appointment type and reduces the risk of placing a patient into an unsuitable slot.
The cancellation that opens a productive slot
A patient cancels a long appointment the day before treatment. The scheduler checks the waitlist for patients who requested that provider, procedure, and timing, then contacts the best matches in an orderly sequence. If no one accepts, the team can offer a shorter appointment, move another visit, or use the time for an appropriate administrative or clinical planning task.
The workflow works because the list is maintained before the cancellation occurs. A spreadsheet with outdated preferences isn't a recovery system. Each entry should show contact permission, preferred days, appointment needs, and the last outreach result.
In the cited 2024 dental scheduling report, average no-show rates declined from 7% in 2022 to 4% in 2023, while the top 10% of practices held no-shows to 1% (dental scheduling and retention report). The operational implication is that confirmation discipline and same-day schedule recovery deserve management attention because even a modest reduction in missed visits can improve access and chair use.
The complicated benefits question
A patient calls before restorative treatment and asks why the estimate doesn't match a previous explanation. The front-office specialist shouldn't improvise. They should review the documented verification, identify whether the issue involves frequency, waiting periods, remaining benefits, coordination of benefits, or a procedure-level restriction, and explain what is known and what remains subject to payer processing.
If the payer information is ambiguous, the staff member documents the call, escalates the interpretation according to practice policy, and avoids presenting an estimate as a guarantee. That approach protects the patient relationship and reduces the chance that an uncertain answer becomes a later dispute.
The frustrated caller
A patient says the office promised an appointment time that isn't on the schedule. The team checks the appointment record and any permitted call documentation, listens without arguing, and offers the available options. The goal is not to prove the patient wrong. It's to establish what happened, resolve the immediate scheduling issue, and document the outcome so the next staff member doesn't restart the conversation.
Building a Compliant and Efficient Team
Efficiency starts with role design. A virtual medical receptionist can manage calls and scheduling, an appointment coordinator can own confirmations and recall, an insurance verification specialist can work benefits, and billing support can handle claims or payer follow-up. Don't give one person every queue without deciding which work takes priority when the phone rings.
Hire for workflow judgment
Experience with dental terminology and practice-management software matters, but judgment matters just as much. Candidates should demonstrate that they can distinguish a scheduling request from a clinical concern, document a payer response without overstating it, protect privacy during a phone conversation, and escalate an issue instead of guessing.
A useful evaluation includes:
- Communication: Role-play a new-patient call, a cancellation, and a balance question.
- Systems ability: Test navigation of the practice-management system or a comparable training environment.
- Accuracy: Provide a sample eligibility response and ask the candidate to identify what can and can't be told to the patient.
- Documentation: Review a sample phone note for clarity, completeness, and appropriate escalation.
- Reliability: Confirm availability during the practice's working hours and ability to follow a defined queue.
Training should continue after onboarding. Use call reviews, payer examples, schedule audits, and short refreshers when a workflow changes. Managers should coach the behavior that affects the assigned role, rather than measuring every employee against the same standard.

Protect PHI before access begins
HIPAA isn't a badge or a marketing label. It is a set of requirements that apply to covered entities and their arrangements with business associates. The ADA's HIPAA guidance for dental practices states that dentists need a compliant written business associate agreement with each business associate. The agreement must describe permitted and required uses and disclosures of protected health information, prohibit unauthorized use or disclosure, and require the associate to follow relevant Privacy Rule obligations while performing covered work.
That means a remote staffing arrangement should be approved before the assistant receives access. Define the systems, role permissions, minimum necessary information, secure communication methods, incident reporting process, termination procedure, and supervisor responsible for review. A BAA supports compliance, but it doesn't replace access controls, workforce training, vendor oversight, or documented procedures.
Managers who want a broader operational refresher can review HIPAA compliance for clinicians, then confirm the practice's specific obligations with a qualified compliance professional. Avoid claims that any staff member or service is “HIPAA certified.” HHS doesn't recognize an official HIPAA certification.
Build a controlled remote workflow
Use separate accounts where possible, require approved devices and communication channels, and give each role only the access needed for its queue. A remote assistant shouldn't need unrestricted access to every chart, billing function, or clinical module because the practice-management system makes that convenient.
Document the handoff rules:
- Receive: The assistant accepts the call, task, or work item.
- Record: The assistant documents the action in the approved system.
- Escalate: Clinical, privacy, legal, or uncertain insurance matters go to the designated practice contact.
- Close: The assistant records the resolution, pending action, and owner.
- Review: A manager samples work for accuracy and timeliness.
Credentialing and access administration should remain separate from clinical decision-making. Practices can also use medical credentialing support when administrative records, provider information, or payer-related coordination require a defined owner, while keeping licensed clinical responsibilities with the appropriate professionals.
The Takeaway
The dental front office isn't just the place where patients check in. It controls first contact, appointment access, benefit clarity, schedule recovery, payment communication, and the handoffs that determine whether clinical capacity turns into completed care. Treating those responsibilities as a revenue-control function gives owners and managers a better way to find leakage and assign accountability.
Begin with a workflow audit. Review missed calls, callback ownership, incomplete verification, confirmation outcomes, cancellations, waitlist activity, and checkout documentation. Then choose the staffing model that matches the work. Keep patient-facing tasks on site when physical coordination demands it, and consider a defined remote queue for calls, reminders, verification, recall, or billing follow-up when those tasks are being delayed.
The strongest operation isn't the one with the most technology or the largest front desk. It's the one where staff know what to do, systems record what happened, exceptions reach the right person, and managers review the controls that protect patient access and production. A disciplined dental front office makes the entire practice easier to run.
MedicalVirtual connects U.S. dental practices with pre-vetted LATAM professionals for receptionist, scheduling, patient intake, insurance verification, billing, and related administrative workflows during U.S. clinic hours. If your team needs defined front-office coverage without handing remote staff unstructured access, visit MedicalVirtual to review the available staffing approach.
Dental receptionist duties cover scheduling, confirmations and recalls, message routing, intake, insurance verification, payment inquiries, and workflow coordination. The highest-priority work protects same-day access, urgent communication, and appointments already on the schedule.
At 8:15 a.m., the phones are ringing, a cancellation has opened a valuable treatment slot, a new patient's forms are incomplete, and someone at the front desk is asking why an insurance payment hasn't appeared. The receptionist has to keep the patient experience calm while protecting the schedule, documenting accurate information, and routing anything clinical or financially complex to the right person.
That's why dental reception goes beyond phone answering. The role connects patient access, clinical communication, records, insurance, payments, recalls, and daily schedule control. The American Academy of Pediatric Dentistry's recordkeeping guidance describes the first telephone contact as a point where staff may capture identifying information, medical history, the referring party, and the chief complaint before an appointment is scheduled, which shows how early the administrative work of care begins (AAPD recordkeeping guidance).
The seven duties below follow the patient and revenue workflow. Each includes practical scripts, prioritization rules, escalation boundaries, privacy controls, and guidance for deciding what an in-office or remote receptionist can safely handle.
1. Appointment Scheduling and Calendar Management
At 8:15 a.m., a cancellation opens a treatment slot while phones ring and a new patient asks for an appointment. The receptionist must protect provider time, match the visit to the right resources, and avoid promising a slot the practice cannot support.
Each appointment type carries different requirements. A new-patient exam, hygiene visit, emergency evaluation, restorative treatment, crown preparation, and follow-up may need different durations, rooms, equipment, providers, or preparation. Scheduling therefore works best from documented rules in the practice management system, including provider templates, blocked time, operatory assignments, and approved urgent-visit pathways.
A practical opening script keeps the call focused:
“I can help with that. I'll ask a few questions about the reason for your visit and then check the appointment types available with the appropriate provider.”
Record the patient's full name, date of birth, contact details, reason for the visit in the patient's own words, preferred location, and timing constraints. Document reported information without making a clinical judgment. “Patient reports a broken filling” preserves the patient's statement. “Patient needs a new filling” crosses into a conclusion the receptionist should not make.
For practices that accept web requests, FormBackend's booking form solution can feed booking details into template rules. Staff should still review each request before confirming it, particularly if the form lacks appointment type, location, or contact information.
Protecting the calendar
A cancellation should be matched deliberately. Check the approved short-notice list and patients waiting for treatment, then confirm that the replacement fits the provider, room, procedure length, and preparation requirements. Same-day access rules take priority over merely filling the gap.
Use defined boundaries for exceptions:
| Situation | Receptionist action |
|---|---|
| Double-booking concern | Pause and verify the template with the office manager or clinical lead. |
| Late arrival | Apply the written late-arrival policy and ask the provider whether the visit can proceed. |
| Urgent request | Follow the emergency decision tree rather than placing the patient into a routine opening. |
| Multi-location request | Confirm location, provider, records access, and insurance workflow before booking. |
Remote receptionists can maintain schedule accuracy during call surges when they use secure access, limited permissions, and the same live calendar as the office. Let them book approved appointment types and move visits within defined rules. Route exceptions to an in-office lead, and audit schedule changes so privacy, availability, and communication errors are traceable.
2. Appointment Confirmations and Recall Management
A patient confirms by text, then calls to reschedule. Another cancels without choosing a new date, while an overdue hygiene patient remains buried in the recall list. Without a defined workflow, the schedule appears full but still develops avoidable gaps and lost treatment opportunities.
Start with an automated reminder, then assign staff to unresolved responses. Record each outcome as confirmed, reschedule requested, declined, or no response. A no-response status should never be treated as confirmation. Before closing the task, check the patient's preferred communication method and correct outdated contact details.
Use a script that establishes the decision clearly:
“I'm calling from [Practice Name] to confirm your appointment with [Provider] on [Date] at [Time]. Would you like to keep that appointment, reschedule it, or ask a question before the visit?”
Keep reminders neutral and disclose only what the channel permits. Avoid placing unnecessary procedure details in an unsecured text message or voicemail. If the patient mentions pain, worsening symptoms, or a concern about treatment, stop the scheduling conversation and route the message to the clinical team.
Build recall queues around the next action
Recall work includes routine hygiene visits, overdue patients, unfinished treatment, and cancellations without a replacement appointment. Separate these groups so staff can apply the right script and priority. A patient who accepted treatment but never scheduled needs a different follow-up from someone due for preventive care.
A practical queue is:
- Time-sensitive: Clinician-requested follow-ups and unfinished treatment.
- Routine: Preventive visits and continuing-care reminders.
- Open-slot recovery: Patients willing to accept short-notice openings.
- Service recovery: Patients who canceled after a complaint or difficult experience.
The Princess Dental Staffing front-office task list includes confirmations, rescheduling, cancellations, no-shows, open appointment times, and patient information management among common front-office responsibilities.
Remote receptionists can manage outbound queues with a current list, approved scripts, and access to suitable openings. Limit permissions, require documentation of each contact attempt, and give an in-office lead authority over clinical questions, complaints, and exceptions. Recall staff may invite a patient to speak with the care team, but should not advise whether treatment remains necessary.
3. Message Triage and Patient Communication Routing
A voicemail about swelling can arrive beside a request to move a cleaning appointment. Both need a response, but they do not belong in the same queue. Calls, portal messages, emails, and faxes may involve scheduling, billing, medication questions, records, urgent symptoms, or complaints. The receptionist's first job is to identify the request, assess whether a clinical risk is present, and assign the right owner.
Use a dental-specific routing guide that defines the receptionist's boundaries. Administrative questions can be handled directly. Clinical questions go to the hygienist, assistant, or dentist according to the practice's protocol. An open-ended script gathers facts without inviting diagnosis:
“Can you tell me what's happening, when it started, and whether there's swelling, bleeding, fever, injury, or trouble breathing or swallowing?”
Record the patient's words, onset, symptoms, callback number, preferred contact method, and any relevant appointment or procedure. The receptionist can route the information, not interpret it, prescribe, read radiographs, or promise an outcome.
Route by risk and next action
Use a priority queue that connects each message to a response deadline:
- Immediate escalation: Trouble breathing or swallowing, serious injury, uncontrolled bleeding, rapidly increasing swelling, or another concern covered by the practice's emergency protocol.
- Same-day clinical review: Significant pain, a broken tooth or restoration, post-procedure concerns, or symptoms the dentist has marked for prompt review.
- Routine clinical message: Non-urgent treatment questions, records requests, and follow-up questions.
- Administrative request: Appointment changes, forms, payment questions, and general office information.
A potential emergency should be transferred or escalated under the written protocol. If the clinical team is unavailable, provide only the approved emergency instructions and document the time, wording, destination, and handoff. Complaints also need an owner, especially when they involve a recent visit, a billing dispute, or a request for clinical review.
Remote receptionists can perform first-line screening, create messages, track callbacks, and complete warm transfers. The healthcare administrative skills overview for medical virtual assistants can help practices define suitable nonclinical responsibilities. Give remote staff current scripts, limited permissions, and a named in-office escalation lead. They should not improvise clinical answers or resolve exceptions outside their authority.
Every message needs a status and an owner. “Sent to dentist” is only a routing event. The record should show when it arrived, who accepted it, the expected response time, and when the patient received an answer. Supervisors can audit overdue items and confirm that urgent messages were not buried under routine callbacks.
4. Insurance Verification and Eligibility Checks
A patient can arrive expecting a covered procedure and leave with an unexpected balance if verification was incomplete. The receptionist or verification specialist should confirm active coverage, network status, available benefits, copays, deductibles, annual maximums, and authorization requirements. Record the result so another team member can see what was checked, when, and through which source.
Use a clear script rather than promising payment:
“We've checked the information available from your plan, but the insurer makes the final payment decision after it processes the claim. We can review the expected patient portion and explain what may affect it.”
A useful verification record names the payer, date checked, portal or representative used, reference details when available, and any qualification attached to the benefit information. Keep the terms separate. Eligibility confirms whether coverage is active. Benefits describe the plan's provisions. Preauthorization and predetermination address approval or an advance review. Claim adjudication occurs after submission.
Set the review level by appointment risk
Verification effort should follow the financial and scheduling risk of the visit. Review a new patient, major treatment plan, procedure with a known authorization requirement, or unfamiliar payer earlier than a routine appointment with stable information. The reviewer should confirm:
- Active coverage: Is the plan active on the date of service?
- Network status: Is the provider or location participating?
- Patient responsibility: What copay, deductible, or coinsurance information is available?
- Benefit limits: Are there frequency or annual limitations?
- Authorization: Does the planned service require prior approval?
- Documentation: Is the verification note complete and dated?
The MedicalVirtual insurance verification service illustrates a role focused on eligibility and benefits work rather than general reception.
Remote staff suit repetitive, portal-based checks completed before the visit. Give them approved scripts, defined permissions, and a handoff rule. Send conflicting payer information, disputed estimates, nuanced financial questions, and treatment-specific decisions to the billing lead or practice manager. The office should identify who can delay booking, request authorization, or approve proceeding, then document that decision in the patient record.
5. Patient Intake and New Patient Onboarding
A new patient arrives with forms incomplete, a missing referral, and no record of a medication listed during booking. The receptionist needs a workflow that identifies these gaps before check-in, while keeping clinical decisions with the care team. Onboarding begins when the appointment is booked: send registration and health-history forms, confirm contact details, request prior records when appropriate, and explain what must be completed before arrival.
A practical message is:
“You'll receive the registration and health-history forms after we finish this call. Please complete them before your appointment if you can. If anything is unclear, contact us rather than guessing.”
Offer approved completion methods, including the patient portal, a secure form, phone assistance, or completion in the office. Record the submission status in the practice system. A remote coordinator may send forms, monitor missing fields, and issue a reminder, but must not request sensitive information through a personal email, text account, or shared spreadsheet.
Separate administrative intake from clinical review
Reception staff collect information and identify omissions. They do not decide whether a medical-history response is safe or whether treatment should proceed. If a patient reports a medication, condition, allergy, or symptom that could affect care, the receptionist records the wording accurately and routes it to the dentist or designated clinical professional.
Use clear status labels such as complete, incomplete, and awaiting clinical review. For example, a patient transferring from another practice may have submitted forms but still need radiographs and treatment notes. The coordinator places the record in the pre-visit review queue, records the outstanding request, and assigns an owner. No one should mark the intake complete merely because the patient returned the first form.
Onboarding coordination also needs a handoff map. Practices running intake across office and remote staff can use a structure similar to employee onboarding for hybrid teams to define who sends forms, checks returned records, contacts the patient, and escalates exceptions. A daily incomplete-intake report prevents requests from sitting without an owner.
For dental and orthodontic workflows, MedicalVirtual' support for dental and orthodontic practices describes administrative coverage that may include forms, scheduling, records, and front-desk communication. Remote onboarding works when access permissions, approved scripts, records-request steps, and escalation boundaries are documented. The remote coordinator manages the queue. The clinical team decides what requires follow-up.
6. Patient Payment Collection and Billing Inquiry Handling
A patient arrives expecting to pay one amount, then sees a different balance after insurance processes the claim. The receptionist must explain the administrative record clearly, collect authorized payments, and route questions without promising an outcome the practice cannot guarantee.
At check-in or checkout, confirm the patient's identity, review the amount assigned to the visit, collect payment through the approved platform, and provide a receipt. Explain whether the next step is a pending claim, a future statement, or scheduling recommended follow-up care. By phone, staff can review the statement and identify whether an insurance claim is still pending. They may explain approved payment options, but they should not change a charge, waive a balance, interpret a payer contract, or promise a specific reimbursement.
Use a consistent script:
“I can review the statement with you and explain what our records show. If the question involves a disputed charge or an insurance decision, I'll send it to our billing team for review.”
Set the escalation boundary before assigning this duty. A remote billing assistant or receptionist can handle routine balances and documented payment arrangements when the practice has written rules, an approved authority limit, and a named billing owner. Escalate:
- Claim disputes: The patient challenges how insurance processed a service.
- Clinical disagreement: The patient questions whether treatment was necessary.
- Refunds or adjustments: The requested action exceeds the receptionist's authority.
- Financial hardship: The patient requests an exception or customized arrangement.
- Complaint or service recovery: The issue concerns care or staff conduct.
The DentalPost receptionist FAQ describes the front office as a hub for customer service, clerical work, and insurance-related coordination. Its cited 2021 Dental Salary Survey reports that 48% of front-office team members earned less than $40,000 annually, while 38% earned between $41,000 and $60,000. Those figures illustrate the broad administrative and revenue-related scope of the role.
Use the practice's approved payment platform, never store card details in free-text notes, and verify identity before discussing an account. Limit financial permissions to the tasks assigned. Remote staff can process routine billing work and reduce interruptions for clinicians when the queue, escalation owner, documentation standard, and response expectations are explicit. Each inquiry should end with a recorded status, responsible owner, and next action.
7. Compliance and Implementation Controls
The seventh duty is the control system behind the other six. A dental receptionist works with protected health information, demographic details, insurance records, payment information, and messages that may describe clinical concerns. The practice must define who can view each record, who may edit it, and which situations require escalation.
HIPAA obligations apply to covered entities and business associates. Practices should confirm their specific responsibilities with qualified compliance counsel. The HHS summary of the HIPAA Privacy Rule outlines the federal framework for protecting protected health information. A product labeled “HIPAA certified” does not by itself establish compliance, because HHS does not recognize an official HIPAA certification.
Design the role before hiring
Write the workflow guide before assigning the work. Cover appointment types, scheduling permissions, emergency routing, message categories, intake requirements, insurance documentation, payment authority, and backup contacts. Test each instruction against realistic cases, such as a broken-tooth call, same-day cancellation, incomplete medical history, disputed estimate, or request for records.
Consent and authorization forms can be completed through secure eSign for dentists, allowing signed documents to reach the patient record without paper handling. Set a retention rule and confirm that staff know where the completed form belongs.
A remote receptionist should receive:
- Role boundaries: Administrative tasks they may complete and decisions they must escalate.
- System permissions: The minimum EMR and phone access needed for the role.
- Communication scripts: Approved wording for reminders, billing, intake, and urgent routing.
- Privacy procedures: Rules for screens, calls, documents, passwords, and device use.
- Quality review: A defined process for checking messages, scheduling changes, and verification notes.
Remote coverage should match clinic hours and the practice's time zone. Staff assigned to the busiest call window can protect access, while a verification specialist may work earlier to prepare the next day's schedule. Automation can handle predictable first-pass reminders. Staff should manage exceptions, non-responses, complaints, and requests requiring judgment.
Call handling also needs measurement. One dataset reported a 62% average answer rate across 4,280 calls from 26 practices, while industry summaries cited 75% as a typical average and 90% or more for top performers. The same source material indicated that roughly 20% to 38% of inbound dental calls were missed during business hours (Peerlogic's dental call-handling case study). Track a small operational set: answered calls, abandoned calls, completed callbacks, schedule gaps, confirmation status, intake completion, and unresolved messages. Every exception should have an owner, deadline, and documented disposition.
Dental Receptionist Duties: 7-Point Comparison
| Service | Implementation complexity | Resource requirements | Expected outcomes | Ideal use cases | Key advantages |
|---|---|---|---|---|---|
| Appointment Scheduling and Calendar Management | Medium–High (EMR integration, specialty rules) | Real-time EMR & phone access; trained receptionists; possible multi-staff coverage | Fewer no-shows, optimized provider utilization, faster booking | Multi-provider clinics, specialty practices, high-volume scheduling | Proactive gap-filling; accurate booking data; supports forecasting |
| Appointment Confirmations and Recall Management | Low–Medium (reminder systems plus scripts; compliance) | EMR reminder tools or third-party confirmation services; SMS/email/voice channels; consent tracking | Lower no-show rates, higher recall completion, improved quality metrics | Practices with preventive care programs or high no-show rates | Reduces no-shows 20–40%; converts cancellations to filled slots; audit trail |
| Message Triage and Patient Communication Routing | High (triage protocols, clinical judgment, escalation paths) | Triage flowcharts, trained staff, real-time EMR access, escalation contacts | Faster response for urgent issues, fewer inappropriate clinician interruptions, documented routing | Primary care, urgent care, behavioral health, high clinical call volume settings | Rapid routing of urgent cases; liability protection through documentation; better patient experience |
| Insurance Verification and Eligibility Checks | Medium (payer portals, pre-auth workflows) | Eligibility portals/clearinghouses, phone access to payers, experienced verification specialists | Fewer denied claims, reduced surprise billing, cleaner claims submission | Surgical/procedural practices, high-cost services, multi-payer environments | Identifies pre-auths and OOP costs; reduces claim denials; informs financial counseling |
| Patient Intake and New Patient Onboarding | Medium (forms integration, records requests, follow-ups) | Automated form distribution, intake coordinators, EMR access, records-request workflow | Faster check-in, higher intake completion, clinicians prepared with prior records | Practices onboarding many new patients or requiring prior records (specialty clinics) | Pre-populates demographics/history; reduces first-visit delays; captures consents |
| Patient Payment Collection and Billing Inquiry Handling | Medium (PCI/HIPAA compliance, payment integration) | PCI-compliant payment processor, practice management access, trained billing staff and scripts | Improved cash flow, reduced AR, fewer escalated billing disputes | Practices with substantial patient balances or frequent billing inquiries | Collects copays/balances; establishes payment plans; reduces write-offs |
| Aggregate Compliance and Implementation Considerations | High (cross-cutting legal and operational requirements) | SOPs, role-specific training, EMR & phone access, monitoring/reporting tools | Consistent, compliant workflows; measurable operational metrics; reduced risk | Practices deploying virtual receptionist services or selecting vendors | Centralizes compliance guidance; standardizes processes; enables quality monitoring |
The Takeaway
Dental receptionist duties form a connected operating system. Scheduling protects provider time, confirmations and recalls protect future access, message routing protects urgent communication, intake supports a prepared visit, insurance verification reduces avoidable surprises, and payment handling keeps financial questions from disrupting clinical work. The front desk also needs clear controls so that administrative staff never diagnose, interpret clinical information, or make decisions reserved for licensed professionals.
Prioritize work by urgency and appointment impact. Route potential emergencies first, protect today's schedule, complete time-sensitive intake and insurance tasks, then work routine recalls and billing questions. Before assigning duties to remote staff, document scripts, escalation rules, EMR permissions, communication preferences, and quality measures. The IHS dental front-desk job description reflects the breadth of common expectations, including confidential record handling, eligibility checks, provider-template scheduling, confirmations, cancellation recovery, and patient-policy communication.
Remote support is most effective when it supplements a defined workflow rather than trying to compensate for a missing one. A virtual medical receptionist can manage approved scheduling and communication tasks, while an insurance verification specialist, patient intake coordinator, or billing assistant can own more focused queues. Clinical judgment, emergency decisions, disputed treatment questions, and exceptions should remain with the designated in-office or licensed team.
MedicalVirtual can help U.S. practices scope a dental front-desk role and review a human-curated shortlist of pre-vetted Latin American healthcare professionals aligned with the practice's hours and workflow. That can be useful when you need coverage for calls, recalls, intake, insurance verification, or billing support without combining every responsibility into one undefined position.
MedicalVirtual connects U.S. dental practices with pre-vetted Latin American healthcare professionals for scheduling, patient communication, intake, insurance verification, and billing support during practice hours. Visit MedicalVirtual to define the role, review a shortlist built around your needs, and discuss coverage that fits your systems and escalation rules.
Yes, a remote medical receptionist can handle high-volume clinic calls when the practice uses formal call-center staffing logic rather than treating the role as ad-hoc administrative help. With about 88% of healthcare appointments scheduled by phone, staffing decisions must account for call timing, handle time, service targets, and escalation rules, not just the total number of calls.
The usual problem appears before the first provider finishes a visit. The phone rings while a patient waits at check-in, a nurse needs a message routed, an authorization is still pending, and the front-desk employee is expected to do all of it without letting the schedule fall apart. A remote receptionist can absorb that pressure, but only when the person has secure system access, clear boundaries, and enough coverage during the hours patients call.
This guide explains what the role includes, how it fits into phone and EMR workflows, when human staffing makes more sense than AI or a hybrid model, and how to vet LATAM-based support for a U.S. practice. It also addresses privacy, prior authorization coordination, bilingual communication, specialty differences, and the operational checks that separate a reliable remote team member from another inbox to manage.
Why U.S. Medical Practices Need Remote Front-Desk Coverage
A primary care office can lose control of its morning quickly. One patient calls to reschedule, another needs a new-patient appointment, a third wants to know whether a referral was received, and an established patient leaves a voicemail because nobody answers. Meanwhile, the in-office receptionist is checking in patients and collecting forms. The work isn't necessarily difficult, but it arrives concurrently, and interruptions create errors.
Healthcare has already moved much of this access work into centralized telephone operations. A 2022 NIH-indexed study of primary-care telephone access management found that most medical centers relied on centralized call centers for scheduling and nurse triage, while the organization and responsibility of those centers varied widely. The study is available through the Healthcare Contact Center Survey Report. A remote medical receptionist is therefore not an unusual add-on. The role is a smaller, distributed version of an established access-management model.

Phone demand still determines access
A 2024 healthcare scheduling analysis reported that about 88% of healthcare appointments were scheduled by phone, compared with 2.4% booked online. It also reported a 4.4-minute average hold time in U.S. healthcare call centers and a 16% abandonment rate, meaning nearly one in six callers disconnected before reaching a scheduler. The analysis is summarized in healthcare scheduling data from CCDCare.
The same source estimated that 30% to 40% of incoming outpatient clinic calls were appointment-related. That makes front-desk coverage an access issue, not merely a convenience. If the receptionist misses a call during a surge, the result may be a voicemail backlog, a delayed booking, an empty cancellation slot, or a patient who calls another practice.
Practical rule: Measure demand by hour and call type before you decide whether you need a person, an AI overflow layer, or both.
Remote coverage works best when the practice defines the problem precisely. A solo behavioral-health provider may need a bilingual person during clinic hours to answer calls and protect therapy time. A multi-site primary-care group may need queue coverage, centralized scheduling, recall outreach, and message routing. Those are different staffing designs, even if both use the title remote medical receptionist.
What a Remote Medical Receptionist Actually Does
A remote medical receptionist handles patient-facing administrative work from outside the clinic, using the practice's phone platform, scheduling software, EMR, and approved communication tools. The core role includes answering calls, booking and rescheduling appointments, confirming visits, managing cancellations, recording messages, and routing requests to the appropriate team member.
The scope can expand into virtual medical assistant work. That may include recall lists, new-patient intake, insurance verification, referral coordination, form follow-up, and prior-authorization paperwork. The person can gather records, submit documentation, track status, and escalate delays, but clinical judgment remains with licensed staff. A receptionist shouldn't diagnose, interpret symptoms, decide medical necessity, prescribe, or independently triage a clinical complaint.
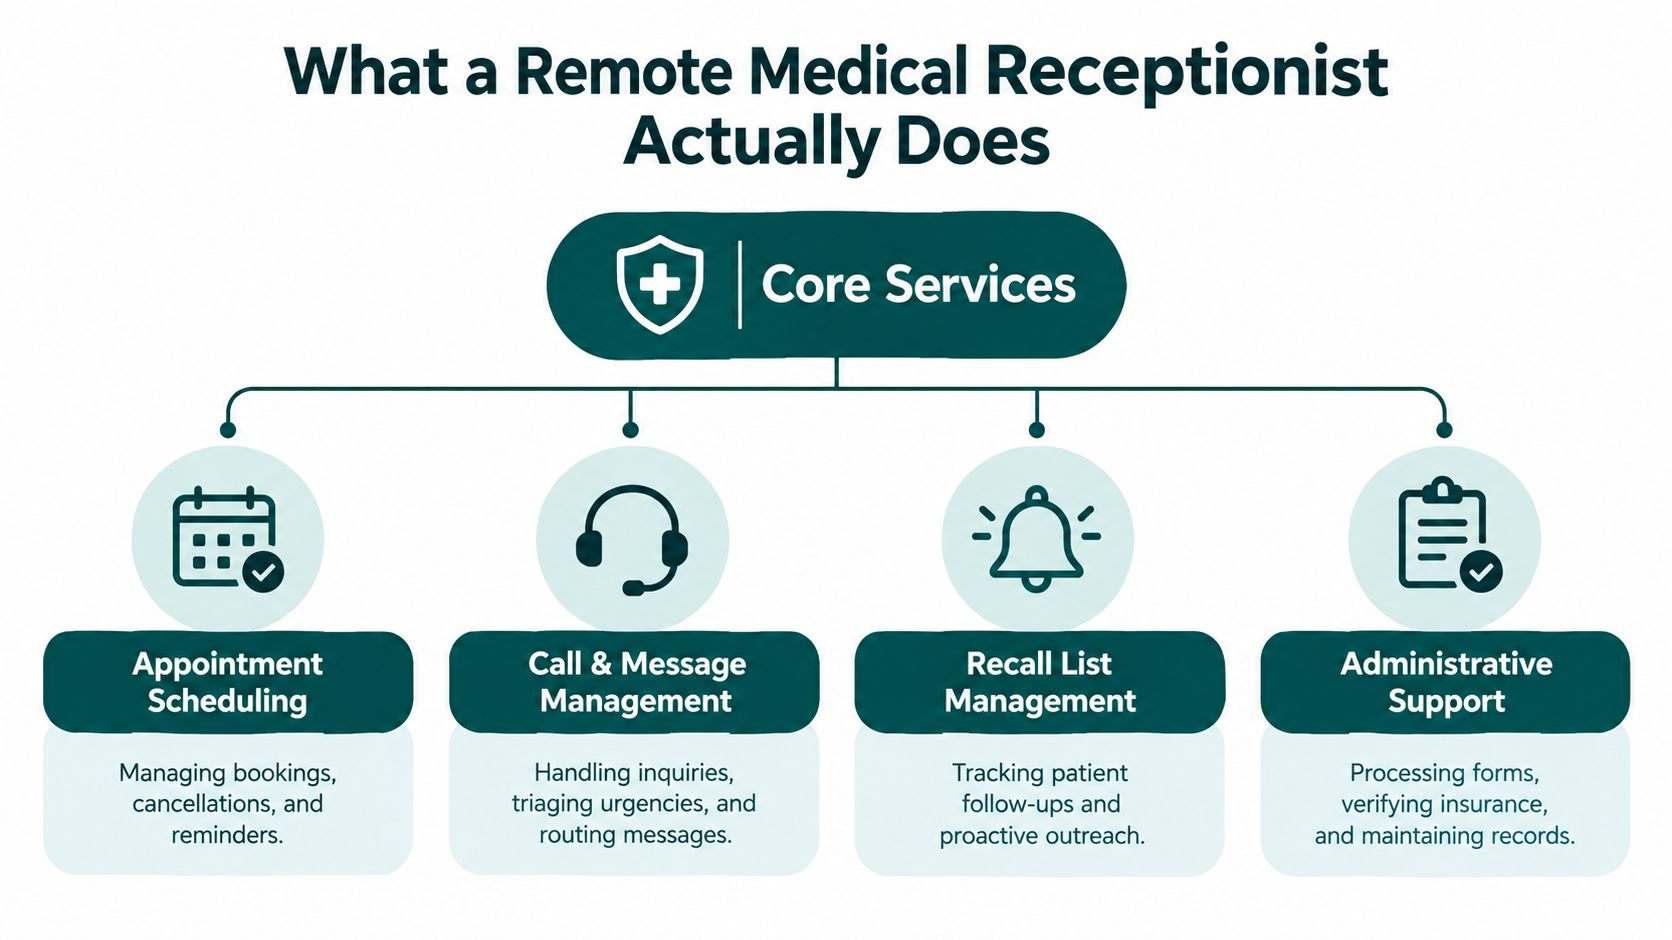
The daily responsibility map
| Function | Typical remote responsibility | Escalation boundary |
|---|---|---|
| Appointment scheduling | Book, cancel, reschedule, confirm, and fill openings from an approved waitlist | Clinical suitability and appointment urgency stay with the practice |
| Call and message management | Answer inquiries, document messages, and route them according to written rules | Symptoms, emergencies, and medical advice go to licensed personnel |
| Recall management | Contact patients about approved follow-ups, recalls, and unconfirmed visits | The clinical team defines who requires follow-up and when |
| Administrative support | Process forms, verify insurance, organize records, and support referrals | The receptionist doesn't interpret documents or make coverage guarantees |
| Authorization coordination | Gather documentation, submit requests, monitor payer status, and escalate | Medical necessity decisions and clinical peer discussions remain with providers |
The role also helps with the operational work that tends to disappear during busy sessions. A receptionist can maintain a cancellation list, contact patients who haven't confirmed, prepare registration forms, and route portal messages into a defined queue. A separate insurance verification specialist or prior-authorization specialist may be a better fit when those tasks consume substantial time.
For a clearer view of how reception, scheduling, intake, billing, and coordination roles differ, review the medical virtual assistant role categories. Practices hiring bilingual English and Spanish support can also compare expectations with bilingual customer service jobs on Virtustant Jobs, particularly for phone etiquette, written communication, and language proficiency.
Remote doesn't mean detached
An in-office receptionist can greet patients and manage physical check-in. A remote employee can't hand someone a clipboard or observe a waiting-room interaction, but can protect the in-office team from phone and inbox interruptions. That distinction matters for dental, optometry, veterinary, and multi-location practices, where physical presence may still be necessary for check-in while remote staff manage calls, recalls, insurance questions, and schedule changes.
The strongest arrangement assigns ownership rather than vague availability. The receptionist should know which appointment types they can book, which messages need same-day routing, which forms require staff review, and what to do when a provider's schedule changes. Without those rules, remote coverage moves confusion from the front desk into a digital queue.
Integrating Remote Staff with Your Phone and EMR Systems
A remote receptionist can answer calls reliably and still create operational problems if the phone queue, EMR permissions, or message rules are unclear. A capable worker needs dependable tools, defined ownership, and written procedures. Without them, missed transfers, duplicate notes, and incorrect appointments quickly become a staffing headache.
Document the workflow before granting access. Trace each call from identification through appointment selection, documentation, escalation, and closure. Create separate instructions for new patients, established patients, cancellations, refill requests, referrals, billing questions, and potentially urgent messages. For details on how insurance verification fits into intake workflows, see our insurance verification services.
Build the technical connection in stages
Define the system of record. Decide whether the EMR, practice-management platform, phone system, or task queue holds the authoritative status for each activity. Recording the same update in several places makes omissions more likely.
Create individual accounts. Give each staff member a named login with only the permissions required for the role. Shared passwords and broad administrative access make accountability and access reviews harder.
Configure the phone queue. Set call groups, business-hour routing, voicemail rules, transfer destinations, hold messages, and fallback coverage. Document when the receptionist should keep a caller on the line, take a message, or escalate immediately.
Test EMR actions in a controlled environment. Verify appointment booking, cancellation, rescheduling, message entry, document upload, and task assignment. Confirm that audit logs identify the user who completed each action.
Write the escalation script. Include identity verification, emergency language, provider messages, interpreter requests, and the limits of administrative support. The script should guide the receptionist without inviting clinical advice.
HIPAA does not require a particular software brand or staffing location. A practice that gives a remote worker access to protected health information does need appropriate contractual and operational safeguards. Depending on the arrangement, these may include a Business Associate Agreement, role-based access, confidentiality commitments, secure transmission, workforce training, and documented incident procedures. Confirm specific obligations with qualified compliance counsel.
A phone intake layer can support the workflow, but it cannot correct unclear routing rules. If you are evaluating a voice lead capture system, test how it records, routes, and secures information against your HIPAA program and patient communication policy. Review transfer behavior, message ownership, and failure handling before connecting it to live calls.
LATAM coverage requires deliberate scheduling
LATAM-based staff can align with U.S. clinic hours, which often matters more than broad promises of round-the-clock availability. Primary care offices may need support during a Monday morning surge, a lunch-hour backlog, or a late-afternoon scheduling push. Therapy practices may need coverage while providers are in sessions. An English-Spanish bilingual receptionist can reduce handoffs for clinics serving multilingual communities.
Set the schedule around actual call patterns and provider availability. Define who supervises the worker, how schedule changes are communicated, and where every message is documented. Use a dedicated account, approved devices, secure password management, and a private workspace. Integration is complete only when the clinic can review access, assign responsibility, and trace each patient communication to a clear next action.
Human Remote Staffing vs. AI and Hybrid Solutions
Human, AI, and hybrid models solve different operational problems. A human remote receptionist provides judgment, empathy, flexible conversation, and direct accountability. AI can absorb repetitive requests and provide after-hours coverage. A hybrid model combines automated intake or overflow with a person who handles exceptions, escalations, and patient interactions that need context.
The choice should begin with two weeks of call logs, including volume by hour, average handle time, abandonment, transfer reasons, appointment requests, and message categories. Guidance on medical call-center management and Erlang C staffing emphasizes that coverage depends on call volume, average handle time, and target service level. A commonly cited operational benchmark is 80% of calls answered within 30 seconds, while typical handle time is 3 to 5 minutes, but those figures should be treated as planning references rather than universal requirements.
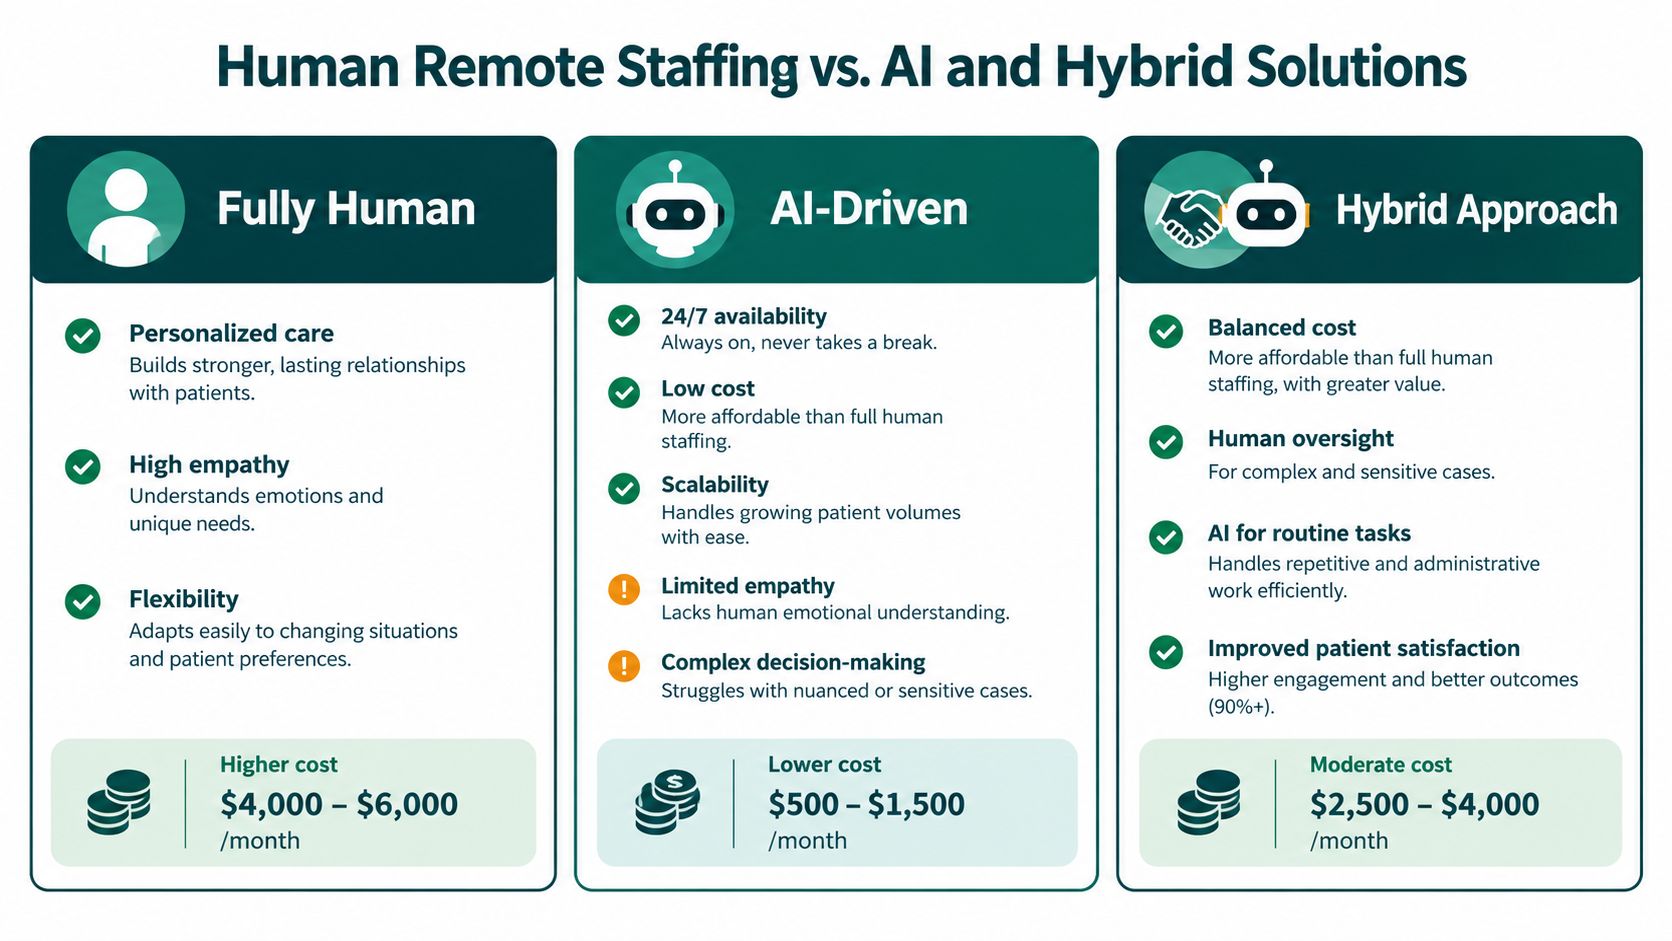
Match the model to the call pattern
| Model | Works well for | Weak point | Practical fit |
|---|---|---|---|
| Fully human | Live scheduling, bilingual conversations, complex patient questions, recalls, and message routing | Requires staffing coverage and supervision | Strong choice when patient interaction needs judgment |
| AI-driven | Simple requests, basic information, overflow, and after-hours intake | Can struggle with ambiguity, distress, exceptions, and nuanced scheduling | Useful when requests are predictable and escalation is reliable |
| Hybrid | Automated first contact with human handling of exceptions and priority calls | Requires careful handoff design and integration | Appropriate when demand fluctuates or after-hours intake matters |
Implementation speed is another trade-off. Guidance cited by the virtual medical receptionist overview from OHMD states that human remote services typically go live in 1 to 2 weeks, while AI or hybrid deployments may take 2 to 4 weeks, depending on EMR integration and scheduling complexity. A faster launch isn't automatically better, but a practice with immediate daytime coverage needs may reasonably start with a trained human and add automation later.
AI is most useful when the practice has a narrow, repeatable request set. It may collect a callback request, provide approved location information, or capture an appointment inquiry after hours. It becomes riskier when patients describe symptoms, ask whether a visit is medically necessary, or need a schedule exception. Practices exploring AI for after-hours support should define those boundaries before activation.
Use a simple decision test
Choose primarily human coverage when:
- The call requires context. Patients frequently explain complex scheduling constraints, referral questions, or sensitive concerns.
- The population needs language support. English-Spanish communication is central to access and trust.
- The schedule changes often. Human staff can handle cancellations, waitlists, provider changes, and exceptions more naturally.
- The practice needs daytime continuity. A remote receptionist working U.S. clinic hours may solve the underlying problem more directly than a 24/7 promise.
Consider AI or hybrid support when:
- Requests are repetitive. The practice receives many basic calls with predictable answers.
- After-hours capture matters. Patients need a way to leave structured information outside office hours.
- The queue spikes briefly. Automation can collect routine requests while human staff handle live callers.
- The handoff is explicit. Every automated path has a documented destination, response time, and owner.
Don't judge the model by availability alone. Judge it by completed bookings, accurate messages, timely escalation, and whether staff can tell what happened to each patient request.
How to Hire and Vet Remote Medical Talent
Hiring a remote medical receptionist should resemble hiring an in-office employee with additional controls for distance, system access, and communication. A polished phone voice isn't enough. The person must follow scheduling rules, document accurately, respect clinical boundaries, and stay calm when several demands arrive at once.
Start with a role scorecard. Separate reception from specialized work instead of combining every administrative function into one vague job description. A receptionist may manage calls and appointments, while an insurance verification specialist checks eligibility, a prior-authorization specialist tracks payer requests, and a billing assistant works denials and follow-up.
Evaluate the person in the work itself
Use a practical screening sequence:
Review relevant experience. Look for prior U.S. medical practice, billing, patient coordination, or call-center work that matches your specialty and systems.
Test the core skills. Give a simulated scheduling task, a message-routing exercise, an EMR navigation scenario, and a written documentation sample. Assess accuracy before speed.
Test language and phone judgment. A bilingual role requires more than conversational Spanish. Test the ability to explain administrative steps clearly in English and Spanish without improvising clinical advice.
Verify identity and background. Complete appropriate background checks and confirm work history according to your hiring arrangement and applicable requirements.
Train before access. HIPAA and privacy training should precede live PHI access. Add your own rules for identity verification, minimum necessary access, screen privacy, device use, and incident reporting.
Run a supervised launch. Start with a defined call queue or appointment type. Review recordings where legally and operationally appropriate, message accuracy, scheduling errors, and escalation decisions.
MedicalVirtual is one staffing option for U.S. practices seeking pre-vetted LATAM healthcare talent. Its placement model includes role scoping, a human-curated shortlist, candidate interviews, in-country employment and payroll support, confidentiality measures, HIPAA training, and Business Associate Agreement execution. The company places roles such as remote receptionists, patient intake coordinators, insurance verification specialists, billing assistants, records specialists, and prior-authorization support. Practices should still perform their own operational and compliance review before granting access.
Set performance expectations after hiring
A remote employee needs a manager, not just credentials. Assign one internal owner for schedule-rule updates, escalation questions, quality review, and access changes. Define what gets reviewed daily during the first stage, what gets audited weekly afterward, and which errors require immediate retraining.
Track operational measures that reflect the role's actual purpose:
- Answer and abandonment patterns: Identify the hours when callers wait or disconnect.
- Booking accuracy: Check appointment type, duration, provider, location, and patient instructions.
- Message completeness: Confirm that the reason for contact, callback details, and routing destination are clear.
- Escalation discipline: Review whether clinical or urgent matters reached licensed staff promptly.
- Recall execution: Check whether approved follow-up lists are worked consistently rather than sporadically.
- Authorization tracking: Confirm that submissions, payer responses, deadlines, and escalations are documented.
Prior authorization deserves its own workflow. The American Medical Association's physician survey found that 93% of physicians said prior-authorization delays care, and 29% said those delays led to a serious adverse event for a patient in their care. Another AMA report states that prior authorization consumes around 13 hours of physician and staff time per week, while 40% of practices have staff whose sole job is handling those requirements. Those figures support assigning administrative tracking to trained staff, but they don't authorize a remote coordinator to make clinical decisions.
For impacted Medicare Advantage, Medicaid CHIP, and Marketplace plans, CMS says that from January 1, 2026, expedited prior-authorization decisions must be sent within 72 hours, and standard decisions within 7 calendar days. Practices can use those limits as tracking and escalation targets, while recognizing that payer, plan, request type, and applicable rules still matter. An AMA survey summary also reported that 64% of physicians waited at least one business day, and 30% waited three business days or longer, for prior-authorization decisions, as reported by Healthcare Dive.
Use the talent FAQ for medical virtual assistant hiring to clarify questions about placement, systems, supervision, and role scope before signing an agreement. The right hire should reduce queue pressure without creating a second layer of uncertainty.
The Takeaway
A remote medical receptionist can handle meaningful call volume, but the practice must staff the role around hourly demand, handle time, service targets, and escalation needs. The work extends beyond answering phones to scheduling, recalls, message routing, intake, insurance verification, and administrative coordination. Clinical judgment stays with licensed staff.
For a U.S. practice using LATAM-based support, align coverage with U.S. clinic hours, use individual secure accounts, document permissions, confirm the Business Associate Agreement structure, and test the phone and EMR workflow before launch. Start with a narrow role, measure the queue and booking quality, then expand only when the process is stable. A human, AI, or hybrid model can work, but the decision should follow the call pattern rather than a generic promise of 24/7 availability.
MedicalVirtual connects U.S. medical practices with pre-vetted LATAM professionals for reception, scheduling, patient intake, insurance verification, billing, records, and prior-authorization support. Review the available staffing options at MedicalVirtual and request a role match based on your specialty, systems, language needs, and clinic hours.
At the end of a busy clinic day, the last patient leaves, the phones quiet down, and the provider opens a second shift inside the EHR. Notes remain unsigned, the assessment and plan needs careful reconstruction, and billing staff can't work from encounters that aren't closed. Choosing providers choice scribe services isn't just a decision between hiring help and buying software. It's a decision about who controls the documentation workflow, how much clinical context is preserved, and where review responsibility sits.
A provider-driven scribe model lets the practice define the EHR process, the specialty requirements, the review cadence, and the level of human oversight. A remote human scribe can listen during the encounter, draft directly in the chart, and leave the provider with a note to review and sign. Ambient AI tools can be faster to deploy and less expensive at the software-license level, but they may still leave providers editing, transferring, and validating notes later.
The right choice depends on visit complexity, EHR integration, provider preferences, privacy obligations, and the work that remains after the draft is created. The following guide focuses on those operational details, including measurable outcomes, daily workflow design, human and AI trade-offs, HIPAA responsibilities, and the broader remote staffing roles that can support a practice beyond clinical notes.
Taking Control of Your Documentation Workflow
At 6:15 p.m., a family physician finishes the final appointment but still has several open charts. One note needs a medication history reconciled, another requires a clearer assessment, and a third is waiting for the provider to confirm the plan before a charge can move forward. The physician can finish the work tonight, arrive early tomorrow, or carry the backlog into the next clinic session. None of those options fixes the underlying process.
Providers choice scribe services refers to a documentation model in which the practice chooses how the scribe participates, which EHR fields they use, what the provider reviews, and how the service is supervised. The phrase matters because a scribe isn't interchangeable with a transcription app. A human virtual scribe can follow the visit's context, recognize when the provider changes direction, work through templates, and ask for clarification through an agreed workflow. The provider still owns the clinical record and signs the final note.
A wound-care practice, for example, may need consistent descriptions of wound location, measurements, tissue characteristics, drainage, treatment, and follow-up. A general-purpose note generator may produce a readable draft while missing the fields that support continuity and coding. An accurate wound care charting template can help the practice define the required structure before training a scribe or configuring software.
The decision is about workflow ownership
A passive AI tool usually listens, generates a draft, and waits for the provider to correct it. That can work well for straightforward, predictable visits. It becomes less attractive when the provider needs the scribe to handle a specialty template, carry information into discrete fields, or manage documentation while the visit continues.
A dedicated human scribe creates a different operating rhythm. The scribe joins through an approved secure connection, listens in real time, drafts in the EHR, and follows the practice's rules for incomplete information, pending results, and provider review. This doesn't remove clinical accountability. It moves repetitive documentation work away from the clinician while preserving a defined sign-off step.
Practical rule: Choose the model that removes the work you actually want removed, not merely the model that produces a note fastest.
The first audit should therefore map the current process. Record where notes originate, who enters them, how often providers edit them, which fields cause delays, and what happens when a visit includes multiple problems. That map gives you a practical basis for selecting a human, AI, or hybrid model instead of accepting a vendor's default workflow.
Measuring the Impact of Scribe-Assisted Drafting
Scribe programs should be evaluated as operating changes, not as vague promises about convenience. The useful question is whether the practice closes encounters faster, reduces unfinished chart work, and preserves note quality without extending provider hours.
A multicenter primary-care quality-improvement study found that clinicians spent 20.4% less time in notes per appointment, falling from 10.3 to 8.2 minutes, after ambient scribing was implemented. The same study reported that same-day appointment closure rose 9.3 percentage points, from 66.2% to 72.4%, while after-hours work time fell 30.0% per workday, from 50.6 to 35.4 minutes. These findings are reported in the JAMA Network Open study of ambient scribing.
The operational meaning is straightforward. Same-day closure is a leading indicator of a smaller chart accumulation, fewer unsigned notes, and less risk that coding and billing work will wait for documentation. A few minutes saved on each encounter can also compound across a high-volume clinic day, creating capacity to close more encounters without extending the provider's schedule.
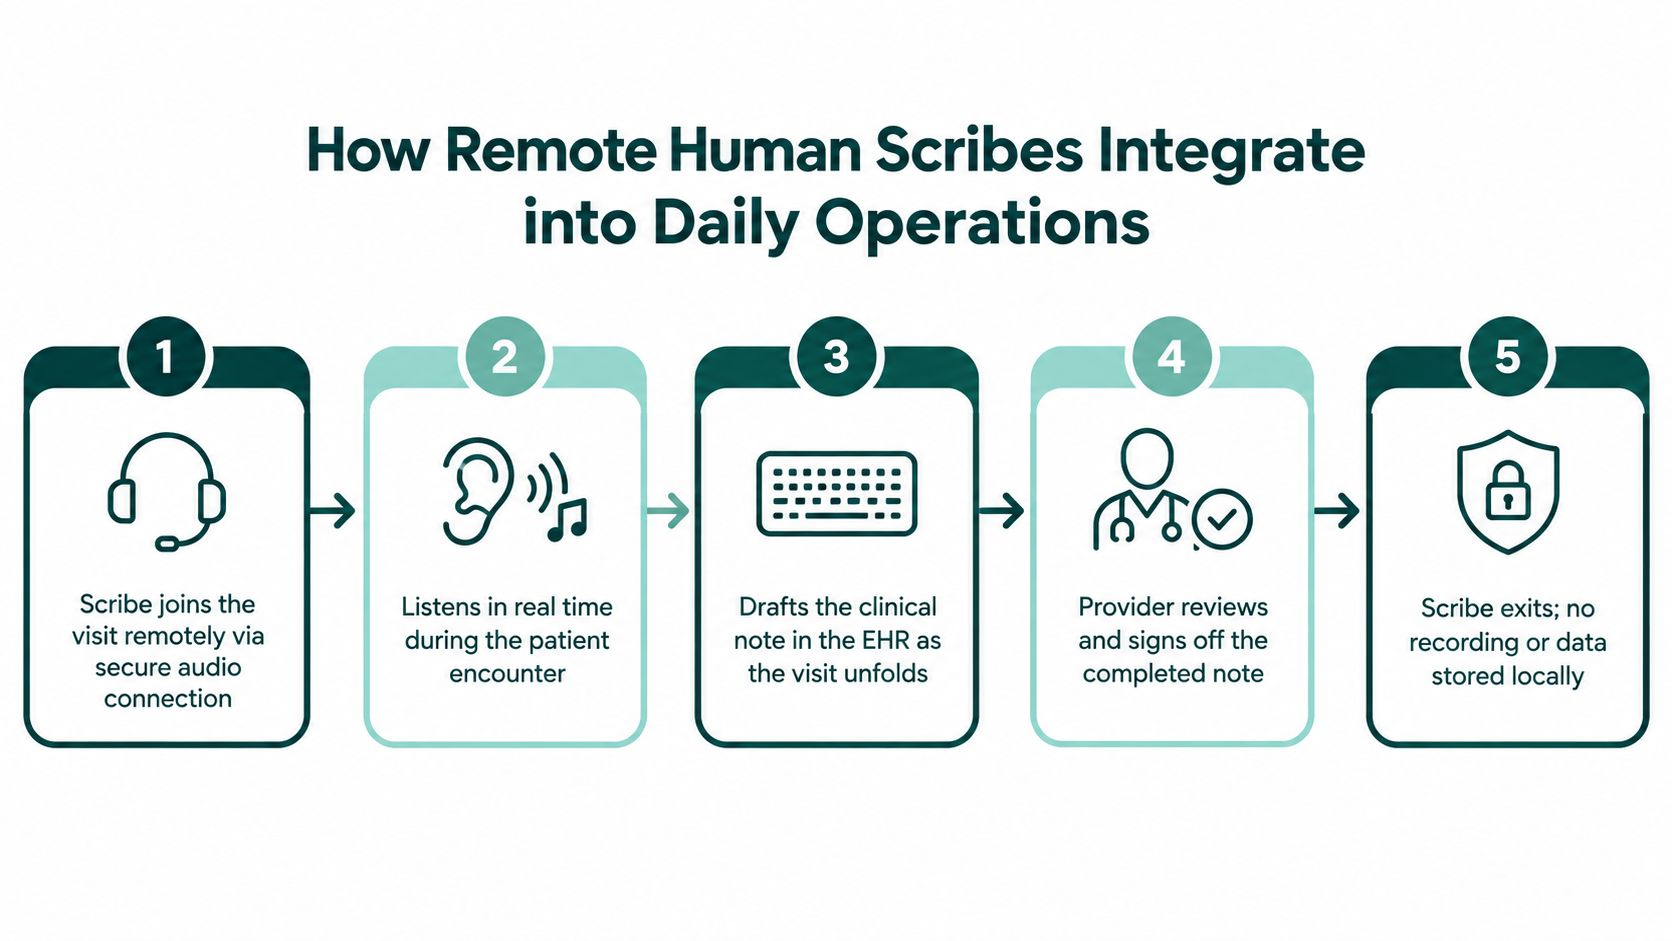
The measures that belong on your dashboard
A practice manager shouldn't rely on a single productivity number. Track the point at which documentation becomes operationally useful, then compare the baseline with the pilot period.
- Note time per appointment: Measure provider time spent creating, editing, and finalizing the note.
- Same-day closure: Count encounters signed before the clinic day ends.
- Next-business-day completion: Identify charts that remain open after the provider's scheduled review window.
- After-hours documentation: Track charting completed outside scheduled clinical hours.
- Correction patterns: Review whether errors cluster in histories, objective findings, or assessment and plan fields.
- Downstream readiness: Check whether coding, charge entry, referrals, and follow-up tasks can proceed from the signed note.
A crossover study of 18 primary-care physicians found that documentation was more likely to be completed by the end of the next business day during scribed periods, with an adjusted odds ratio of 2.8 and a 95% confidence interval of 1.2 to 7.1. The physicians were also more likely to close at least 95% of office, telephone, and virtual encounters by the target time. The findings appear in the crossover study of scribe use and documentation productivity.
Measure quality, not just speed
Faster closeout doesn't justify a workflow that creates unsafe or unreliable notes. The same research link reports a simulation study in which individual scribe accuracy ranged from 50% to 76%, with section-level accuracy of 72% for subjective fields, 60% for objective fields, and 56% for assessment and plan fields. The assessment and plan deserves the most deliberate review because it influences clinical decisions, coding, referrals, and follow-up instructions.
During a pilot, sample notes from each provider should be reviewed against the encounter and the final signed chart. Pay particular attention to medication changes, diagnoses, laterality, dosage instructions, test orders, and follow-up intervals. If the scribe produces a polished note but changes the clinical meaning of the plan, the practice hasn't solved its documentation problem.
A useful baseline review can cover a representative mix of routine, complex, telehealth, and procedure-related encounters. Use the results to set training priorities and determine whether the provider should review every section or focus on high-risk fields. The strongest business case combines time saved with acceptable correction effort and reliable same-day completion.
How Remote Human Scribes Integrate into Daily Operations
A remote human scribe works best when the practice treats the role as part of the clinical operating system rather than as an outside note-taking service. The scribe needs a defined login process, an approved communication channel, a schedule that matches the provider's clinic hours, and clear limits on what they can do in the EHR.
The daily workflow typically starts before the first appointment. The scribe confirms the provider's schedule, reviews the practice's note templates and instructions, and connects through the approved platform. During the visit, the scribe listens, identifies relevant clinical details, and drafts the note in the appropriate EHR location. The provider continues the encounter without dictating every sentence.

A workable visit-to-signature sequence
The scribe joins the encounter. The connection should use the practice's approved secure audio or telehealth workflow. The patient should understand that a scribe is participating when the practice's policy or applicable requirements call for disclosure or consent.
The scribe listens for clinical structure. They capture the history, symptoms, relevant negatives, examination findings, decisions, orders, and follow-up instructions. They shouldn't diagnose, select treatment, or independently interpret ambiguous information.
The note is built in the EHR. A trained scribe uses the provider's templates and enters information in the correct fields rather than leaving a large block of text for later sorting. This is where a human scribe can add value over a simple transcription workflow, particularly when the practice depends on structured documentation.
The provider reviews the high-risk content. The provider confirms that the history, objective findings, assessment, plan, medications, orders, and patient instructions accurately reflect the encounter. Any uncertainty should be corrected before signature.
The note is signed and the session ends. The scribe exits according to the practice's process. The service should define what happens to temporary notes, recordings, screenshots, and locally cached data, rather than leaving those questions to individual staff members.
The role also needs boundaries. A scribe may prepare a draft, organize information, and follow documentation instructions. They may not make clinical decisions, communicate a diagnosis as their own judgment, change orders without authorization, or sign on behalf of a licensed provider. Practices should document these boundaries in training materials and access policies.
Review cadence determines sustainability
Providers often resist scribe programs when the review step becomes unpredictable. A provider who reviews every note several hours later may still experience a delayed workload, even if the scribe created the draft in real time. A more sustainable cadence is usually a brief review immediately after the visit or during a defined block while the encounter is still fresh.
The difference between a medical assistant and a medical scribe is useful when assigning responsibilities. A medical assistant may support rooming, intake, orders, and administrative workflows, while a scribe's central responsibility is documentation under provider supervision. Combining the roles can work in a small practice, but only when the schedule leaves enough uninterrupted time for accurate charting.
Review the assessment and plan before you review the prose. A grammatically clean note can still contain a clinically wrong decision.
A monthly quality review can identify recurring problems without turning the program into a punitive audit. Look for missing details, inappropriate assumptions, template misuse, and corrections that should become part of the scribe's training. The practice should also maintain a fallback process for connection failures, unexpected volume, and visits that require the provider to document independently.
Comparing Human Virtual Scribes and Ambient AI Tools
Human and AI scribes solve different parts of the documentation problem. An ambient AI tool can capture a conversation and generate a draft without scheduling another person. A dedicated human virtual scribe can interpret the encounter's workflow context, manage the EHR while the visit unfolds, and apply practice-specific instructions. Neither option removes the provider's responsibility to review and sign the record.
A broader review found that scribe outcomes vary with workflow design. Physicians may still edit charts later, and the reduction in EHR time depends on choices such as when and how the provider reviews the note. The review also found that scribes can improve efficiency and job satisfaction, while the provider and scribe relationship can affect burnout and note length may increase even when documentation time falls. These considerations are discussed in the review of medical scribes and clinician workflow.
| Feature | Human Virtual Scribe | Ambient AI Scribe |
|---|---|---|
| Primary function | Listens, drafts, navigates the EHR, and follows practice-specific instructions | Captures conversation and generates a note draft |
| Context handling | Can recognize workflow cues and request clarification through an agreed process | May misinterpret speakers, chronology, abbreviations, or ambiguous statements |
| EHR work | Can enter information into designated fields when access and training permit | May require copy and paste, an extension, or a supported integration |
| Provider effort | Review remains necessary, but routine drafting and navigation can be delegated | Provider reviews and may need to correct or reorganize the generated note |
| Specialty fit | Training can focus on the practice's templates, terminology, and visit types | Performance may vary by specialty, visit length, audio quality, and complexity |
| Availability | Depends on staffing coverage, schedule management, and backup capacity | Available when the service and connection are functioning |
| Data handling | Requires controls for human access, temporary files, and communications | Requires review of recording, transcript, retention, training, and vendor access terms |
| Scaling | Adds a labor and management component | Adds software seats, usage, integration, and implementation requirements |
When human oversight earns its place
A human scribe is often a stronger fit when visits contain several active problems, when the provider relies on structured EHR fields, or when the practice has specialty-specific documentation requirements. Wound care, behavioral health, orthopedics, cardiology, and complex primary care can all require more than a fluent summary. The note must preserve distinctions that affect treatment, coding, and follow-up.
The human model also makes sense when the clinic has a predictable provider schedule and can maintain a dedicated working relationship. That continuity allows the scribe to learn the provider's templates and preferences. It doesn't eliminate training or quality review, but it can reduce the repeated explanation that occurs when a different tool or person handles each encounter.
Where ambient AI can be appropriate
AI may suit a solo provider who wants a low-friction trial, sees relatively consistent visits, and is comfortable reviewing the complete draft. It can also be useful when staffing coverage is difficult or when the provider wants documentation assistance without adding a scheduled participant to every visit.
The lower apparent cost of software isn't the same as lower total operating cost. The practice should include implementation, integration, provider learning time, correction work, and the consequences of notes that remain outside the EHR until someone transfers them. A tool that produces a draft quickly but leaves the provider with substantial editing may shift the burden rather than remove it.
A hybrid model can be sensible. AI can create an initial draft, while a human reviewer or dedicated scribe checks structure, enters information into the correct fields, or supports providers whose notes require more contextual judgment. That model adds coordination, so it should be tested against the actual workflow rather than adopted because it sounds like a one-size-fits-all fix.
Navigating HIPAA and Business Associate Agreements
When an outside scribe service handles protected health information for a medical practice, the compliance work starts before the first patient encounter. The practice needs to identify the vendor's role, the data the vendor can access, the systems involved, and the safeguards that govern that access.
Under HIPAA, an outside service handling PHI for a covered entity must have a written Business Associate Agreement. The agreement should define permitted uses and disclosures, require safeguards against unauthorized access, and require the vendor to report breaches or improper disclosures. The HHS sample business associate agreement provisions provide a useful reference for the subjects a BAA should address.
HHS also explains that business associates are directly liable for certain HIPAA requirements. The covered entity isn't required to monitor every safeguard used by the business associate, but it must obtain satisfactory written assurances through the BAA. That distinction matters. A practice still needs a due-diligence process, but it shouldn't treat a vendor's marketing statement as a substitute for a signed agreement and documented controls.
What to verify before access is granted
- Confirm the BAA: Obtain the final agreement, identify the parties, and confirm that the services and data flows are covered.
- Define permitted access: Limit the scribe's EHR permissions to the tasks they perform. Don't grant broad administrative access for convenience.
- Ask about recordings: Determine whether audio or video is created, where it is processed, how long it remains available, and how deletion is handled.
- Review breach duties: Confirm notification procedures, escalation contacts, cooperation obligations, and documentation requirements.
- Check workforce controls: Verify confidentiality agreements, HIPAA training, access termination, and supervision for every person who may handle PHI.
- Document the review: Keep vendor questionnaires, access decisions, training records, and periodic reassessments with the practice's compliance documentation.
HHS describes common business associate functions as including claims processing, billing, practice management, and related administrative services. That regulatory category aligns with remote staff handling front-desk, documentation, and care-coordination work, but the precise obligations can depend on the arrangement and the data involved. Practices should confirm their circumstances with qualified compliance counsel.
Don't confuse compliance with certification
There is no official HHS designation that makes a scribe service “HIPAA certified.” A vendor may hold security attestations or certifications under other frameworks, but those don't replace the BAA or prove that the practice's implementation is compliant. The practice remains responsible for configuring access, training its workforce, and following its own policies.
For organizations comparing phone, messaging, and patient communication systems alongside scribe services, a platform that documents BAAs and safeguards in one platform may be useful during vendor review. It still shouldn't replace an assessment of the specific scribe workflow.
The practical guide to HIPAA-compliant virtual assistants can help practice managers turn these requirements into a staffing checklist. The final decision should account for state privacy rules, specialty-specific confidentiality concerns, patient notices, and the practice's own security policies.
Expanding Remote Support Beyond the Clinical Note
A scribe can remove a documentation bottleneck, but a practice may still lose capacity through unanswered calls, incomplete insurance work, stalled authorizations, and inconsistent follow-up. Those problems often appear in the same daily workflow. The provider finishes the note, yet the appointment remains operationally incomplete because a referral wasn't sent or a payer request wasn't tracked.
Remote roles should therefore be designed around handoffs. A virtual medical receptionist can manage calls, scheduling, confirmations, and recall lists. An insurance verification specialist can check eligibility and benefits before the visit. A prior-authorization specialist can submit, track, and escalate requests. Billing support can work charge entry, claim submission, denial follow-up, and patient statements.
HHS identifies claims processing, billing, practice management, and related administrative services as common business associate functions in its overview of business associates. That doesn't make every remote staffing arrangement identical, but it shows why these administrative functions require the same deliberate privacy and contracting review as documentation work.
Match roles to the point of failure
A practice with a full voicemail queue doesn't need another billing specialist first. It needs coverage during clinic hours, a scheduling script, escalation rules, and access to the appointment system. A specialty group with clean front-desk operations but delayed imaging approvals needs prior-authorization support, not a broader generalist role.
- Front desk: A virtual receptionist or patient coordinator handles calls, appointment changes, reminders, intake forms, and records requests.
- Revenue cycle: A billing assistant enters charges, follows payer responses, works denials, and identifies missing documentation for escalation.
- Clinical administration: A medical records specialist coordinates referrals, outside records, and document routing.
- Provider support: A virtual scribe maintains the note workflow while the provider retains review and signature authority.
The roles can be separate or combined for a smaller practice, but combining them creates trade-offs. A person who is expected to scribe during visits may not be available to answer calls at the same time. A billing assistant who handles prior authorizations may need protected work blocks to avoid constant interruption.
Build one remote operating rhythm
Remote staff work best when the practice defines who owns each queue, which tasks require provider approval, and how unresolved items are escalated. Use the EHR task system, shared work queues, or another approved channel instead of relying on informal personal messaging. The manager should review open items, turnaround expectations, and error patterns at a regular operational meeting.
MedicalVirtual places pre-vetted LATAM healthcare talent for U.S. practices, including virtual scribes, receptionists, patient coordinators, billing assistants, insurance verification specialists, and prior-authorization support. Its overview of medical virtual assistant roles and hiring is relevant when a practice is considering a coordinated remote team rather than a standalone scribe.
Bilingual English and Spanish support, U.S.-hours alignment, prior healthcare experience, role-specific testing, confidentiality agreements, HIPAA training, and a BAA are useful criteria to verify during placement. The practice should still interview candidates, define permissions, test the workflow, and measure results after launch.
The Takeaway
Providers choice scribe services work best when the practice selects a documentation model around its real workflow rather than around a feature list. A human virtual scribe can provide structured EHR navigation, specialty-aware context, and a consistent same-day review process. Ambient AI can offer rapid adoption and flexible availability, but the practice must account for editing, integration, data governance, and the work that remains after the draft is generated.
Start with a short operational audit. Measure note time, same-day closure, next-business-day completion, after-hours charting, correction patterns, and the point at which billing or follow-up work is delayed. Then test the preferred model with representative visits, review assessment and plan accuracy closely, and define who owns every correction and escalation.
Before granting access, complete the BAA review, limit EHR permissions, document recording and retention practices, and train the remote workforce. If documentation is only one of several bottlenecks, scope a broader team with distinct responsibilities for reception, insurance, authorizations, billing, records, and care coordination. A deliberate provider-driven design is more likely to produce sustainable relief than adding another tool to the end of the workflow.
MedicalVirtual connects U.S. medical practices with pre-vetted LATAM healthcare professionals for virtual scribing, reception, billing, insurance verification, prior authorization, and care coordination during U.S. clinic hours. If you're evaluating a dedicated human scribe or a broader remote support team, visit MedicalVirtual to review role options and begin a specialty-specific conversation.
A referring physician is the licensed doctor who initiates a request for a patient to see another provider or receive a service, and that same clinician is often the person Medicare requires on claims and authorizations. Referral volume rose from 4.83% of physician visits in 1999 to 9.29% in 2009, while current industry reporting says only about half of referral requests are completed, making referral management a workflow issue rather than a vocabulary exercise.
A typical referral starts during an already crowded clinic session. A primary care physician identifies a cardiac concern, sends the patient to a cardiologist, requests relevant testing, and expects the specialist's findings to return to the primary care record. If the referral packet is incomplete, the specialist can't triage it properly. If the wrong clinician is entered on the claim, authorization, or order, staff may spend days correcting an administrative error that began with one unclear provider field.
That's the practical meaning of referring physician. The role connects clinical judgment with scheduling, records transfer, prior authorization, medical necessity documentation, claim submission, and continuity of care. This guide explains how Medicare uses the term, how it differs from ordering and attending providers, what a complete referral packet contains, why referrals fail after they're issued, and how practice managers can build a closed-loop process with the help of appropriately scoped remote administrative staff.
What Is a Referring Physician
The plain-English definition
A referring physician is the doctor who initiates a patient's movement to another clinician, facility, diagnostic service, or treatment pathway. The request may be for a specialist consultation, imaging, a procedure, therapy, or another covered service. In everyday conversation, people often describe this physician as “the doctor who sends you to a specialist.”
That description is useful, but incomplete. In a medical practice, the referring physician's identity can become the anchor for billing, prior authorization, clinical documentation, and provider-to-provider communication. The referral is not finished when a staff member faxes an order or sends an electronic message. The receiving practice needs to know who initiated the request, why the patient is being sent, what service is needed, and where the resulting report should go.
Consider a primary care visit for a patient with persistent exertional symptoms. The primary care physician may refer the patient to cardiology, request that the cardiologist evaluate a specific concern, and identify relevant test results in the chart. The cardiologist then reviews the request, schedules the patient, performs the consultation, and sends findings back to the referring practice. The primary care physician may continue managing the patient throughout the process.
That last point distinguishes a referral from a complete transfer of care. A consultation generally implies cooperation between physicians, with the original physician continuing responsibility for the patient during and after the specialist's input. A referral can involve transferring some or all care to another physician with specialized expertise or access to a facility. The historical distinction became clearer during the 1950s, and a review by the Massachusetts Medical Society describes the development of consultation and referral terminology.
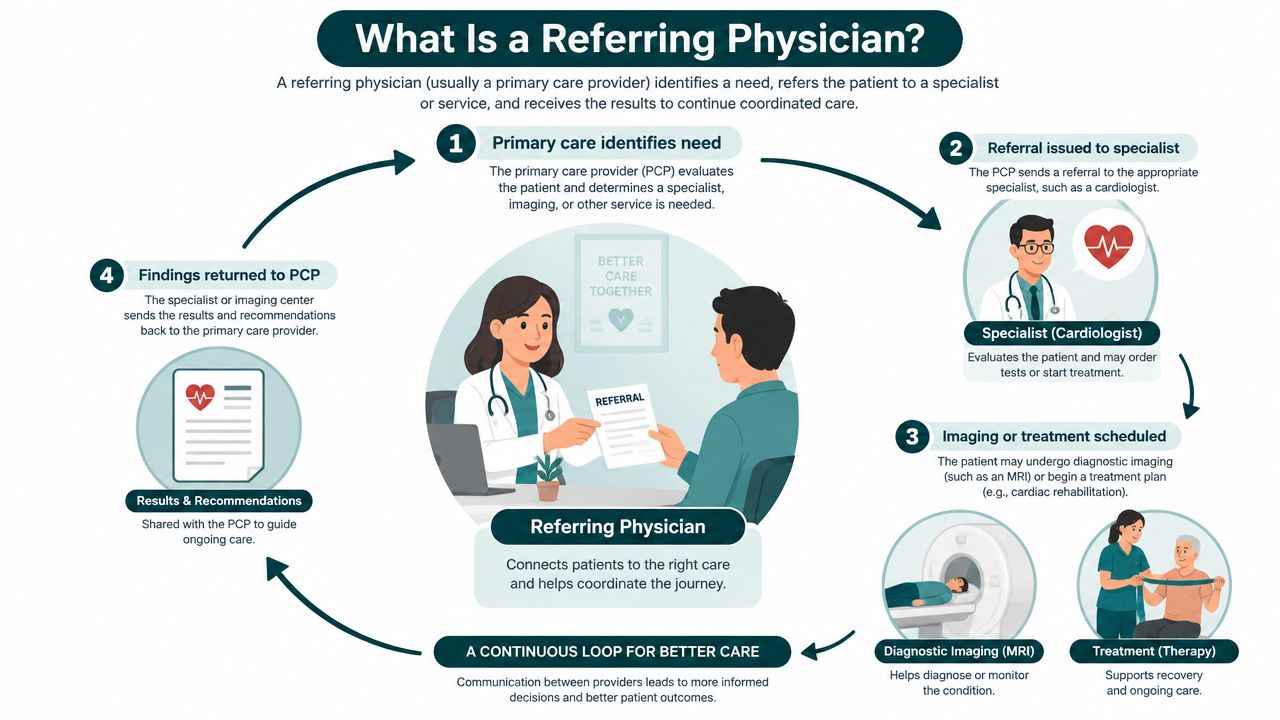
Why the identity matters after the referral is sent
The referring physician's name can appear in several connected workflows:
- Authorization: The payer or receiving office may need the clinician who initiated the service request.
- Claims: Medicare-related claims workflows distinguish the referring clinician from the attending, ordering, and rendering providers.
- Records: The specialist needs a clear destination for consultation findings and follow-up recommendations.
- Scheduling: Staff may need to confirm the referral source, specialty, urgency, and requested service before booking.
- Medical necessity: The clinical reason for the referral must support the requested service and be documented in the chart.
The role also isn't limited to a physician who personally hands a patient a referral form. Under the federal definition used in Stark law regulations, a referring physician can make a referral, direct another person or entity to make one, or control referrals made by another person or entity. That broader definition matters to practice owners because the term carries compliance significance beyond ordinary patient communication.
Practical rule: Treat the referring physician as a controlled data field, not a casual description. Confirm the clinician's identity at the point the referral is created, then preserve that information through authorization, scheduling, claims, and follow-up.
The referring physician may be a primary care doctor, but not always. Another physician involved in the patient's care may initiate the request. The same clinician may also be the ordering provider or attending provider, but practices shouldn't assume those roles are interchangeable. The correct answer depends on what the clinician did in that specific episode of care and what the payer or claim form requires.
The Medicare Definition and Compliance Rules
Medicare treats a referral as an operational and compliance event, not just a message passed between offices. It can be a physician's request for an item or service, including a request for consultation, or a physician-established plan of care that requires designated health services. The Medicare Part B guidance on referring providers and referrals explains why the referral can affect downstream billing and documentation.
The federal Stark law definition is broader than the common office meaning. A referring physician is someone who makes a referral, directs another person or entity to make one, or controls referrals made by another person or entity. The regulation also covers a consultation request and orders for tests or procedures connected with that consultation when Medicare Part B payment may be involved. The federal regulation defining referring physician provides the controlling legal reference for this definition.
How the definition developed
The distinction between referral and consultation became clearer in the 1950s, as medical organizations addressed uncertainty about whether the original physician continued to hold responsibility for the patient. The Stark law's referral definition was enacted at the federal level in 1989. CMS later explained that the original self-referral restriction covered only clinical laboratory services, while the ordering and referring requirement took effect on January 1, 1992.
Current Medicare rules still apply the term broadly. It may identify the physician who starts the request, directs someone else to start it, or controls referrals made by another person or organization. An administrative employee may submit the electronic or paper form, but that task does not automatically make the employee the referring physician.
What this means for claims and authorizations
A referring physician field should be treated as controlled claim data. Medicare data guidance uses the term for the clinician who sends a beneficiary to another provider for a service. If that clinician differs from the attending clinician, the referring provider may be required in the applicable claims workflow. The ResDAC explanation of referring, ordering, attending, and rendering provider variables helps staff assign the field based on the clinician's actual role.
Errors usually arise from workflow shortcuts. Staff may enter the specialist because that office submits the claim, select the attending physician even though another doctor initiated the service, or copy an old referral source into a new authorization. The patient can receive appropriate care while the practice still creates claim corrections, authorization delays, or compliance questions. Validate the field against the referral order and clinical note instead of relying on memory or a default EHR value.
Prior authorization requires the same control. For imaging, procedures, or specialty medications subject to payer review, the request should connect the service to the clinician who ordered or referred it. A documented prior authorization workflow for medical practices can separate clinical records, payer requirements, status tracking, and escalation responsibilities. Staff must still review each case because payer rules and state obligations vary.
Use one operating rule: document who requested what, for which patient, and for what clinical reason. Keep the referral order, supporting note, authorization record, and claim information consistent. Medicare and commercial payer requirements may differ, so billing leaders should escalate disputed or unusual cases to qualified compliance counsel.
Referring Physician vs Ordering vs Attending Provider
The terms referring physician, ordering physician, and attending provider describe different actions or relationships. They can refer to the same person in one encounter and three different people in another. The error occurs when staff treat the labels as permanent titles instead of asking what each clinician did in practice.
| Role | What the clinician does | Typical operational question |
|---|---|---|
| Referring physician | Initiates or directs the patient's request for another provider or service | Who sent the patient or service request into the next stage of care? |
| Ordering physician | Requests a specific test, treatment, item, or service | Who ordered this MRI, lab, procedure, or therapy? |
| Attending provider | Oversees or manages the patient's care in the relevant setting | Who is responsible for the patient's active care during this encounter? |
| Rendering provider | Performs the billed service | Who actually delivered the service being reported? |
When the roles overlap
A primary care physician may evaluate a patient, refer the patient to a neurologist, and order an MRI at the same visit. In that case, the PCP may be both the referring and ordering physician. The neurologist later becomes the attending or treating provider for the consultation and may order additional testing. The imaging facility or radiologist then has its own rendering and billing roles.
A different example involves a hospital patient. The attending physician may request a specialist consultation, making the attending and referring physician the same person for that request. The consulting specialist may order a test, making the specialist the ordering physician for the test while the attending remains the clinician directing the overall inpatient care.
This distinction matters because the provider field should follow the action, not the organizational hierarchy. A group practice's name, a facility name, or the physician who happens to be available for follow-up doesn't automatically replace the clinician who initiated the request.
A practical decision framework
Before entering a provider name, ask four questions:
- Who initiated the referral? Identify the doctor who requested another clinician's input or directed the patient to another service.
- Who ordered the specific service? Separate a broad referral from a particular MRI, laboratory test, procedure, or therapy order.
- Who managed the patient in the relevant setting? This helps identify the attending provider when the care episode involves a facility or active treatment relationship.
- Who performed the service? Confirm the rendering provider separately from the referral source.
The answer may be the same physician for multiple questions. That's acceptable when the documentation supports it. The problem is assigning one name to every field just because that clinician is the PCP, the practice owner, or the specialist receiving the patient.
The provider who receives a referral isn't automatically the provider who made it.
The distinction also helps practices outside traditional specialty medicine. A mental health clinician may refer a patient for neurological testing while another clinician orders a specific assessment. A physical therapy practice may receive a physician referral but rely on a separate order for the treatment plan. A dental office may coordinate with a physician for a medical necessity request without making that physician the attending provider for the dental service.
For teams working across specialties, even clinical terminology can require careful documentation. A practice that handles cognitive or neurological referrals may also benefit from keeping reference materials, such as this Australian psychology resource on the post-traumatic amnesia scale, separate from claim-role instructions. Educational clinical resources and billing role definitions serve different purposes, and staff shouldn't use one as a substitute for the other.
Referral Documentation Standards and Workflow
A referral works when the receiving clinician can understand the question and the administrative team can act without repeatedly contacting the referring office. Professional guidance emphasizes that the request should be specific, complete, and recorded in both the referring and consulting records. The American Academy of Family Physicians guidance on consultations, referrals, and transfers of care supports this continuity-of-care standard.
The Canadian guidance from the College of Physicians and Surgeons of Ontario on transitions in care provides a practical example of the information a referral should contain. Although U.S. practices must apply their own payer, state, and organizational requirements, the underlying operational principle is widely useful: the specialist should receive enough context to understand the requested consultation and determine the appropriate next step.

What belongs in the referral packet
Use a structured checklist rather than relying on free-text notes or a staff member's memory:
- Patient identifiers: Confirm the patient's identifying information and preferred contact details.
- Referring provider details: Include the physician's name, identifiers required by the workflow, contact information, and signature where applicable.
- Clinical question: State what the specialist is being asked to evaluate, treat, or recommend.
- Relevant history: Summarize the symptoms, working diagnosis, significant history, medications, allergies, and prior procedures.
- Urgency: Record whether the request is routine, expedited, or time-sensitive according to the provider's documented judgment.
- Supporting records: Attach relevant imaging, laboratory results, prior consultation notes, and other records needed for triage.
- Requested destination: Identify the specialty, preferred provider or facility when appropriate, and the service being requested.
- Return pathway: State where the consultant's report should be sent and how the referring practice will review follow-up recommendations.
Documentation should also show what happened after transmission. The referral coordinator needs a status such as prepared, sent, received, accepted, scheduled, completed, report received, or follow-up pending. A referral that has been faxed but not confirmed is not a closed referral.
A workable handoff sequence
- Prepare: The physician completes or dictates the clinical request, and staff assemble the supporting records.
- Validate: A coordinator checks patient identity, payer details, provider roles, required signatures, and attachment completeness.
- Transmit: Staff send the packet through the approved channel and record the transmission date and destination.
- Confirm receipt: The receiving office confirms that the packet is readable and sufficient for triage.
- Schedule: Staff document the appointment or the reason scheduling remains pending.
- Monitor: The referring office follows up on uncompleted or rejected referrals according to its internal policy.
- Close the loop: Staff obtain the specialist report, route it to the responsible clinician, and record any follow-up action.
Medical dictation can help clinicians capture the clinical question and supporting context while details are fresh. Practices evaluating medical dictation software for healthcare professionals should still require human review, because transcription tools don't replace provider judgment, chart verification, or referral-role validation.
For practices with recurring authorization work, a prior authorization specialist role can be assigned to gather records, submit requests, check status, and escalate missing information. That role should remain administrative and operate from documented provider decisions. It shouldn't diagnose, alter medical necessity, or independently select a treatment.
The Rise in Referral Volume and Completion Gaps
A referral can create work across several organizations before the patient sees a specialist. Physician practices coordinate with specialty offices, facilities, diagnostic centers, and payer systems, so the referring physician's role becomes an operational trigger for documentation, authorization, scheduling, and follow-up.
A peer-reviewed analysis of U.S. physician visits found that referrals increased from 4.83% in 1999 to 9.29% in 2009, a 92% increase over ten years. The PubMed Central's study of referral patterns in U.S. physician visits also distinguishes a referral from a consultation by whether the original physician continues caring for the patient.
The larger management problem appears after the request leaves the originating practice. Specialists receive more than 100 million referral requests annually, yet only about half are completed. That completion gap turns the referring physician's designation into more than a clinical label. It affects whether staff can identify responsibility, verify authorization, reconcile billing details, and confirm that the patient received the intended care.
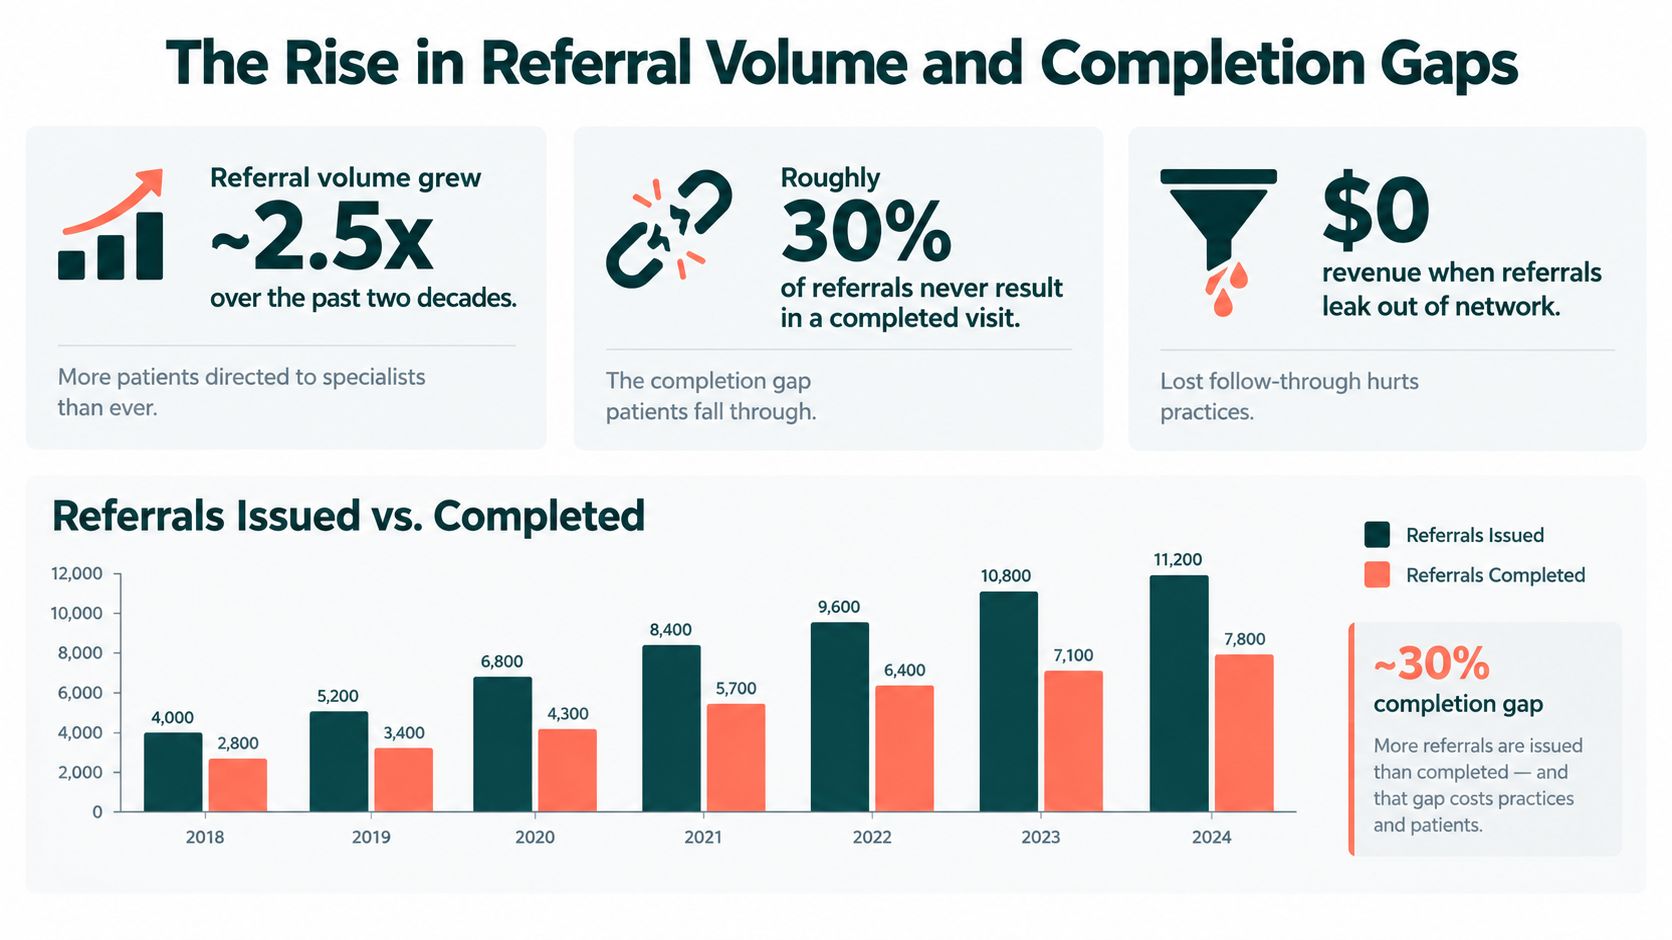
Why issued referrals disappear
A referral can fail at several points:
- The specialist never receives a usable packet. Missing records or an unclear clinical question may prevent triage.
- The payer requires authorization. Scheduling may pause while staff gather documentation or await a decision.
- The patient can't reach the receiving office. The referral is marked sent, but no one confirms an appointment.
- The specialist is out of network. Staff may identify the mismatch only after the patient attempts to schedule.
- The report never returns. The consultation occurs, but the referring practice does not receive or route the findings.
- The EHR status remains stale. A referral stays open without showing whether the patient was seen or whether follow-up is required.
Digital tools have not removed these failure points. MGMA reported in 2025 that 76% of medical groups managed referrals in their EHR or referral software, while 21% still relied on manual tracking. Technology may be available while the actual process still depends on spreadsheets, inbox searches, scanned documents, and staff memory. Managers should compare the system's stated status with evidence of receipt, scheduling, completion, and report routing.
A referral status of “sent” describes an administrative action. It doesn't prove that care was completed.
What the completion gap means for managers
An incomplete referral can leave the patient without specialty input and the primary care team without information needed for a treatment decision. Staff may repeat calls, billing teams may face uncertainty, and the practice may struggle to reconcile the referral source, order, authorization, and completed service.
Manual follow-up by every staff member creates inconsistent work. A more reliable design assigns responsibility by stage, uses defined statuses, sets escalation rules, and records report receipt before closing the referral. The referring physician field should support that process by identifying who initiated the request and who remains accountable for the clinical follow-up.
Improving Referral Management in Your Practice
Start with a single referral definition that every department uses. Train staff to identify the physician who initiated the request, the provider who ordered the specific service, the clinician managing the relevant encounter, and the provider who rendered the service. Put those fields into the referral template instead of leaving them to free-text notes.
Then build a closed-loop queue. The queue should show the patient, specialty, requested service, referring physician, authorization status, receiving office, appointment status, report status, and next action. Assign ownership to a person or team, not to a generic department. A referral without an owner is likely to remain “in progress” until a patient calls.
A practical implementation sequence
First, audit the current path. Select representative referrals from creation through report receipt. Look for missing clinical questions, unclear urgency, duplicate entry, rejected authorizations, and reports that arrive without being routed to a clinician.
Second, standardize the packet. Use required fields for the reason for referral, relevant history, medications, allergies, supporting tests, urgency, provider identifiers, and return destination. Make the EHR prevent transmission when essential fields are blank, where the system supports that control.
Third, define service-level expectations internally. Decide when staff confirm receipt, when they contact a patient, when they escalate an authorization, and when they notify the physician that a referral remains unresolved. These are operational policies, not universal legal deadlines, so document them according to your specialty, payer mix, staffing model, and compliance advice.
Fourth, separate administrative work from clinical judgment. A remote coordinator can request records, verify demographics, contact offices, monitor queues, and route reports. A provider must make clinical decisions, interpret findings, change treatment, and determine urgency.
Where remote support fits
Remote healthcare staff can support referral coordination when the practice supplies clear access controls, written procedures, training, and supervision. A virtual medical receptionist may handle calls and scheduling. A patient coordinator may collect forms and records. An insurance verification specialist may confirm benefits before an appointment. A prior authorization specialist may submit and track payer requests. A medical administrative assistant may maintain the referral queue and route returned reports.
For practices considering a virtual medical receptionist or another remote role, evaluate the person against the actual workflow. Look for reliable documentation, comfort with the EHR and phone system, familiarity with insurance terminology, appropriate escalation habits, and the ability to work the practice's U.S. clinic hours. Remote staff shouldn't independently diagnose, interpret clinical results, make medical decisions, or perform licensed work.
MedicalVirtual is one staffing option for U.S. practices that need pre-vetted LATAM healthcare talent for referral coordination and related administrative work. Its model includes U.S.-hours coverage, prior U.S. healthcare experience for shortlisted assistants, role-specific skills testing, HIPAA training, confidentiality agreements, and a Business Associate Agreement with each client. Practices should still define the role carefully and verify that the arrangement fits their own privacy, security, payer, and supervision requirements.
The Takeaway
The practical referring physician meaning is broader than “the doctor who sends a patient to a specialist.” It identifies the clinician who initiates or directs a request and may connect that request to claims, authorization, medical necessity, and continuity-of-care obligations. That clinician may or may not be the ordering, attending, or rendering provider.
To improve results, standardize provider-role fields, require complete referral packets, assign ownership after transmission, track every referral through appointment and report receipt, and keep administrative responsibilities separate from clinical decisions. A clear workflow protects the patient handoff and reduces avoidable billing rework.
MedicalVirtual can help your practice staff referral coordination, scheduling, prior authorization, records, and other administrative workflows with pre-vetted LATAM healthcare professionals working U.S. clinic hours. Review the available roles and discuss the coverage your referral process needs with MedicalVirtual.
ER scribes have no federal licensure requirement, so the bar is a high school diploma or equivalent, 40–70 WPM typing, English fluency, medical terminology comfort, and HIPAA training before touching PHI, with the note always attested by the treating clinician. In practice, the safest ER scribe requirements go beyond hiring filters and include EMR competency, defined role boundaries, controlled remote access, and auditable clinician review.
A practice manager usually encounters this question after a familiar problem appears: clinicians are moving from bed to bed, the waiting room is full, and unfinished charts are accumulating after the shift. The right scribe can document the encounter as it happens, but the wrong person, vendor arrangement, or access process can introduce omissions, privacy exposure, and confusion about who is responsible for the final note.
This guide focuses on the requirements that matter in an actual U.S. emergency department. It covers the work an ER scribe performs, the qualifications that recur in job postings, the technical skills that separate a workable hire from a dependable one, and the compliance mechanics behind HIPAA, BAAs, and note attestation. It also compares in-person, remote, and AI-assisted models, then provides a hiring and onboarding framework you can adapt to your ED.
What an ER Scribe Actually Does in a Modern ED
An ER scribe documents the clinical encounter in the electronic medical record while the physician, physician assistant, or nurse practitioner evaluates patients and makes treatment decisions. The scribe may enter the history and physical, provider-dictated assessment and plan, procedure details, consultations, diagnostic results, and disposition instructions directly into the EMR.
The role is live and workflow-oriented. A scribe tracks which patient is waiting for reassessment, which laboratory or imaging result has returned, and which chart still needs a disposition. That tracking helps the provider maintain continuity across multiple beds instead of reconstructing the encounter from memory at the end of the shift.
What the scribe can and cannot do
The boundary is straightforward, even when the environment is not. The scribe records what the clinician dictates, observes within the assigned documentation process, or directs the scribe to enter. The scribe does not triage patients, assess symptoms independently, prescribe medication, place clinical orders, select diagnoses, or make treatment decisions.
A unit clerk may manage calls, transport requests, registration details, or department paperwork. A medical assistant typically supports rooming, intake, clinical measurements, and other duties defined by the practice and applicable rules. A transcriptionist converts dictated material into text, often after the encounter. The ER scribe's distinctive function is real-time charting combined with chart tracking during active care.
Practical rule: If a candidate talks about “helping decide” what a patient needs, stop the interview and clarify the scope of the role.
Why live charting changes the ED workflow
Emergency documentation is rarely linear. A provider might begin an HPI, pause to evaluate another patient, review an EKG, return for a reassessment, speak with a consultant, and then discharge or admit the patient. The scribe must preserve the sequence without turning incomplete information into a finished clinical statement.
That requires attention to throughput as well as prose. A well-run scribe process can help providers keep charts current while they move through the department, but it doesn't remove the clinician's responsibility to review the note. The value comes from reducing clerical friction without shifting clinical judgment to unlicensed staff.
Baseline Qualifications Most ER Scribe Postings Require
Most U.S. ER scribe postings start with a high school diploma or equivalent, because the role generally isn't governed by a federal licensure standard. Some employers request college coursework, a bachelor's degree, or prior healthcare exposure, but postsecondary education and certification are commonly preferences rather than universal requirements. University of Michigan's medical scribe posting, for example, specifies a diploma, accurate typing at 70 WPM, clinical or medical terminology experience, and business software knowledge.
Typing thresholds commonly fall between 40 and 70 WPM, depending on the employer and the setting. A large health system may list 40+ WPM, English fluency, computer use for several hours per day, and the ability to manage a demanding workflow. These thresholds aren't a substitute for accuracy. A fast typist who mishears medication names or drops negations is a risk, not an asset.
The filters that deserve a closer look
English fluency usually refers to clear written and verbal communication, not a requirement that the scribe speak only one language. In a busy ED, the scribe must understand provider dictation, document concise clinical language, and communicate a question without interrupting a critical interaction. A bilingual skill set can help with general communication, but it doesn't authorize the scribe to interpret clinical information unless the organization has a separate, properly defined process.
Medical terminology is another practical filter. Candidates don't need to arrive as clinicians, but they should understand common anatomy, abbreviations, diagnostics, and emergency medicine vocabulary well enough to recognize when a phrase needs clarification. Prior experience as an EMT, CNA, medical assistant, student observer, or healthcare administrator can shorten the learning curve, although it isn't always required.
| Requirement | Typical threshold | Why it matters in the ED |
|---|---|---|
| Education | High school diploma or equivalent | Establishes the usual entry point for a role without universal federal licensure |
| Typing | 40–70 WPM, depending on employer | Supports real-time entry while the provider continues the encounter |
| Communication | Clear English reading, writing, and speaking | Reduces ambiguity in dictated notes and handoffs |
| Medical terminology | Basic working familiarity, often preferred | Helps the scribe recognize anatomy, tests, medications, and abbreviations |
| Computer skills | Comfort with EMRs and business software | Allows navigation between charts, results, templates, and provider queues |
| Schedule | Availability for assigned ED coverage | Emergency departments need coverage across demanding shifts |
| Physical tolerance | Ability to remain active through the shift | In-person scribes may stand, move between beds, and work at shared stations |
A useful hiring principle is to evaluate demonstrated ability rather than treating a degree as proof of performance. The Synopsix hiring approach offers a helpful framework for skills-based evaluation, which fits scribe hiring because a timed charting simulation often tells you more than a polished résumé.
For a clear distinction between documentation work and adjacent clinical support, compare the responsibilities in this guide to medical assistant versus medical scribe roles. The distinction matters because an ER scribe shouldn't be hired into a job description that implicitly expects clinical tasks.
Technical and Clinical Skills That Make an ER Scribe Effective
The strongest candidates can move through an EMR without losing the encounter's clinical thread. They know how to open the correct chart, locate prior information, use approved templates or smart phrases, enter dictated material into the right fields, and move between the note and pending results without creating duplicate documentation.
Experience with Epic, Cerner, or Meditech is useful, but it shouldn't be treated as an absolute requirement when the candidate demonstrates sound documentation habits. Every organization configures its EMR differently. What transfers is the ability to learn navigation, follow a template, use keyboard shortcuts appropriately, and recognize when an entry belongs in the HPI, review of systems, physical examination, medical decision-making, or disposition.
The working skill set
An ER scribe may need to track several clinicians, patients, laboratory results, imaging reports, consultations, and reassessments at once. The task isn't just typing what someone says. The scribe must listen for the clinical sequence, identify missing context, and ask a concise clarification question at a safe moment.
Basic EKG and radiology terminology can be preferred skills, especially in emergency settings, but the scribe shouldn't independently interpret either. A candidate who says, “I know when to flag a phrase for clarification, but I don't turn a tracing or image into a clinical conclusion,” understands the boundary.
The soft skills are less visible on a résumé:
- Situational awareness: The scribe knows when not to interrupt a resuscitation, procedure, or sensitive discussion.
- Calm under pressure: The work continues when several charts change at once.
- Concise handoff: A shift-change report identifies open charts, pending results, and unresolved documentation tasks without adding interpretation.
- Attention to detail: Negations, laterality, dosage wording, and disposition status require careful handling.
- Coachability: The scribe accepts chart corrections without defending an inaccurate entry.
A practical test should include an abbreviated ED encounter, a sample provider dictation, and a few result updates. Score whether the candidate preserves meaning, follows the template, distinguishes pending from completed information, and finishes the note without inventing content. That simulation is more predictive than asking whether the person is “comfortable multitasking.”
HIPAA, BAA, and Note Attestation Compliance
HIPAA compliance isn't a training certificate that makes a scribe safe by itself. It is a workflow involving access controls, permitted use of protected health information, supervision, documentation review, and contracts that match the staffing model.
Under HHS guidance on business associates, a covered entity may disclose PHI to a business associate only with satisfactory assurances, ordinarily documented in a signed Business Associate Agreement. The agreement must define permitted and required uses and disclosures and require safeguards against improper access or disclosure.
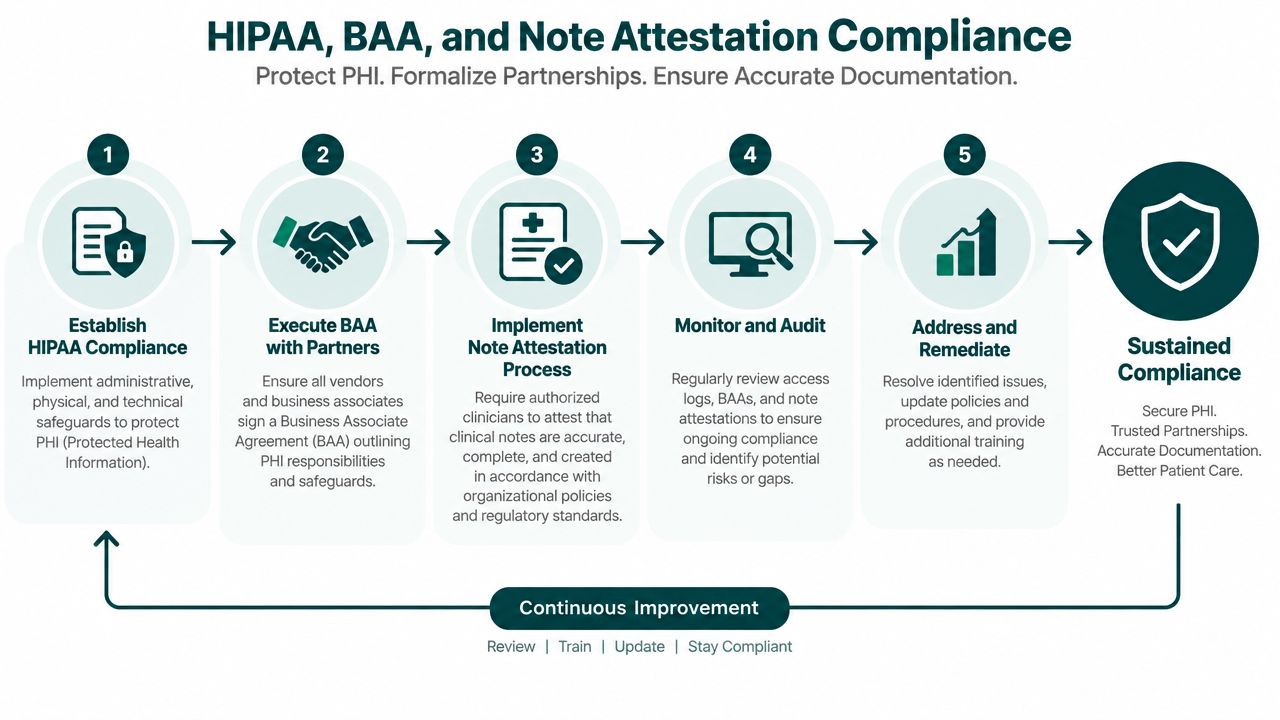
When the staffing model changes the contract
An in-person scribe hired as part of the practice or hospital workforce generally operates under the covered entity's workforce policies, confidentiality rules, access controls, and training program. A remote scribe service that accesses or receives PHI usually creates a business-associate relationship, so the practice should execute the BAA before the service receives access.
The exact arrangement depends on how the service works. A medical-insurance risk review of virtual scribes distinguishes between a service using proprietary software or receiving ePHI, where a BAA is needed, and an individual working only inside the organization's EHR without ePHI transmitted to the service provider, where the contracting structure may differ. Have qualified compliance counsel review the arrangement rather than relying on a vendor's label.
Who signs the note
The scribe drafts or enters the note. The treating physician, PA, or NP reviews the content, corrects errors, and attests or signs according to the organization's and payer's requirements. The clinician remains accountable for the accuracy of the professional service documentation.
ACEP notes that CMS doesn't require the scribe's signature, while some Medicare Administrative Contractors require the chart to identify the person acting as scribe for the clinician. That payer and regional variation means your policy should specify how the scribe is identified, how the provider attests, and which payer rules the billing team checks. ACEP's scribe guidance is useful background, but practices should confirm current requirements with their compliance and billing advisers.
Common ED failure points include:
- Shift handoffs: A departing scribe leaves pending documentation without a named owner.
- Visible screens: A monitor in a curtained bay exposes PHI to patients or visitors.
- Shared accounts: Staff use another person's credentials instead of an individual account.
- Overbroad access: A scribe opens charts unrelated to the assigned workflow.
- Unreviewed drafts: A clinician signs without checking copied-forward or misheard content.
A practice's remote staffing process should also address workstation privacy, secure authentication, access logging, device controls, incident escalation, and breach response. HIPAA rules and breach notification obligations can carry significant consequences, and the practice should obtain current guidance from its privacy officer or counsel rather than treating annual training as the entire control system.
In-Person, Remote, and AI-Assisted ER Scribe Models
The right model depends on how the ED communicates, how quickly providers need documentation, and whether the work requires physical presence. In-person scribes can hear and see the clinical workflow directly. Real-time remote scribes depend on a stable, secure audio or video connection and disciplined handoffs. AI-assisted tools can generate drafts, but they still require human review and clinical attestation.
A useful benchmark is same-day completion. One remote scribe vendor describes a workflow that delivers final notes within 1 hour and guarantees same-day completion, a concrete service-level reference for practices assessing whether remote coverage will reduce end-of-shift backlog. Scribe-X's remote workflow presents that benchmark as a vendor claim, so buyers should test it against their own acuity, connection quality, and review process.
Where each model fits
In-person coverage often fits high-acuity trauma, pediatric emergency care, or departments where providers rely on a scribe positioned beside the workstation or cart. The trade-off is less scheduling flexibility and a larger physical staffing footprint.
Remote coverage can work well for community EDs, overnight documentation, and services with reliable audio feeds and clear provider habits. It can fall short when multiple conversations overlap, the provider moves outside the capture area, or the connection drops during a critical part of the encounter.
AI-assisted documentation may fit lower-acuity fast-track encounters, follow-ups, and post-shift documentation cleanup. It is less suitable when the practice expects the system to recognize every nuance without review. The Commure overview of emergency scribes describes the expanding AI-assisted market and notes a U.S. market estimate of about $622 million in 2026, projected to reach $4.67 billion by 2035. Those figures indicate buyer interest, not proof that an AI workflow fits a particular ED.
| Dimension | In-person scribe | Real-time remote scribe | AI-assisted scribe |
|---|---|---|---|
| Latency | Immediate, if the scribe is present | Near real time when the feed is stable | Real time or shortly after the encounter, depending on the tool |
| Accuracy control | Scribe asks for clarification during the encounter | Depends on audio quality and communication discipline | Provider must review generated content carefully |
| BAA exposure | Usually workforce-based when employed by the covered entity | Service-provider access commonly requires a BAA | Vendor access to PHI commonly requires a BAA |
| Scheduling | Tied to physical coverage | More flexible across locations and shifts | Flexible, but depends on device and integration setup |
| Best fit | High-acuity, highly interactive environments | Stable remote workflows and overnight coverage | Lower-acuity or documentation-support workflows |
| Main limitation | Recruitment and physical coverage | Connection, privacy, and handoff failures | Hallucinated, omitted, or misattributed content if not reviewed |
Remote scribes don't independently practice medicine across state lines. The provider remains responsible for care, while the practice should confirm telehealth, privacy, employment, and organizational requirements that may apply to the communication method and locations involved. For broader remote staffing considerations, see this guide to medical virtual assistant tasks, costs, and hiring.
Onboarding, Training, and Supervision Expectations
A defensible onboarding process starts before the new scribe sees a chart. The practice should verify identity and employment details, complete required screening, provision an individual EMR account, and document privacy and security training before granting PHI access. The exact sequence varies by organization, but informal “learn while watching the board” onboarding is a poor fit for emergency documentation.
A staged onboarding path
Use a staged process that can expand or contract based on the candidate's experience:
- Pre-access screening: Verify the education requirement, test typing and medical terminology, complete background screening, and address any required drug screen or immunization verification for on-site access.
- Policy training: Complete HIPAA and HITECH awareness, security training, confidentiality expectations, code of conduct, and, for in-person staff, applicable OSHA bloodborne-pathogen awareness.
- EMR practice: Use a sandbox with sample ED encounters. Drill chart selection, templates, smart phrases, result tracking, handoffs, and note closure without exposing real PHI.
- Supervised shifts: Pair the new scribe with an experienced scribe or trainer, then assign charting alongside a designated clinician who can give immediate feedback.
- Controlled independence: Move to independent assignments only after the scribe meets the practice's accuracy, escalation, and completion standards.
A VA systematic review describes one scribe model using a 60-hour training program, 2 years of clerical experience, and software familiarity, with medical terminology and coding knowledge preferred. The review also found that scribed notes were often more thorough, comprehensible, and up to date, while benefits varied by encounter type and errors still occurred. The VA review of medical scribes supports structured training and review rather than assuming that speed alone produces quality.
Supervision and quality assurance
The clinician should know who is assigned to the chart, how to request a correction, and what happens when the scribe is uncertain. Supervisors should audit notes periodically, categorize errors, and feed those findings back into templates and training. Annual HIPAA refreshers and access reviews help keep the program current, but they don't replace day-to-day supervision.
A Practical Checklist for Hiring ER Scribes
A structured evaluation is more reliable than résumé screening because ER scribe performance depends on applied skills. Start with the basic filters, then test the candidate in a realistic documentation exercise before granting access to a live chart.
Screen for the minimum viable fit
Review the application for a high school diploma or equivalent, typing within the employer's 40–70 WPM range, EMR exposure, medical terminology coursework or experience, and shift availability that matches the ED. Epic, Cerner, or Meditech experience can reduce training time, but it shouldn't outweigh poor listening or weak documentation judgment.
A phone screen should test communication without turning into a casual conversation. Ask the candidate to explain what an ER scribe may not do, describe how they would handle an unclear medication name, and respond to a scenario in which two providers request documentation at once. Listen for calm prioritization and a willingness to escalate rather than improvise.
Use a paid charting simulation
Give the candidate a sample ED encounter with a short provider dictation, a result update, and a disposition change. Score the work against a defined rubric:
- Typing and timing: Can the candidate keep pace without sacrificing accuracy?
- Terminology: Are clinical terms, abbreviations, and negations captured correctly?
- EMR logic: Does the candidate place information in the right note fields?
- Scenario judgment: Does the candidate recognize uncertainty and ask for clarification?
- Scope awareness: Does the candidate avoid adding diagnoses, orders, or treatment decisions?
- Communication: Can the candidate deliver a concise handoff about incomplete work?
Red flags include discomfort with patient-facing environments, a vague understanding of HIPAA, inability to follow a documentation template, resistance to correction, or an expectation that the role includes independent clinical decisions. References should confirm performance in a fast-paced, detail-sensitive setting, not just attendance or general administrative reliability.

Weight typing, terminology, EMR comfort, and scenario performance evenly instead of letting a degree or confident interview style dominate the decision. If you're evaluating a remote candidate, add a connectivity test, a private-workspace confirmation, and a walkthrough of how the person will handle interruptions or a lost audio feed.
The core ER scribe requirements are simple to state but demanding to operate. MedicalVirtual can help practices evaluate pre-vetted remote healthcare staff with U.S. practice experience, HIPAA training before start, EMR-focused skills testing, U.S.-hours coverage, and BAA support. Visit MedicalVirtual to discuss a remote scribe profile that matches your ED workflow, specialty, software, and coverage needs.
A patient arrives at the pharmacy on Monday morning expecting to start a newly prescribed medication. The pharmacist submits the claim, the system rejects it, and a short message says prior authorization required. The patient is directed to call the medical office, while the pharmacy sends a fax that may sit in a shared inbox until someone notices it. The prescription hasn't been denied clinically, but the patient still leaves without the medication.
That scene captures the practical problem with pharmacy prior authorization. The process is presented as a payer review, yet it often begins with a rejected claim at the pharmacy counter. The clinic then has to identify the reason for the rejection, collect supporting records, submit the request, monitor the decision, respond to denials, and confirm that the patient receives the drug.
Prior authorization is widespread in drug coverage, particularly for specialty therapies. It can protect formularies from inappropriate use, but it can also create delays, rework, confusion, and abandonment. This guide explains what happens after the rejection, how the workflow should be divided among staff, where electronic tools help, and why approval is only a midpoint rather than a completed access event.
What Happens at the Pharmacy Counter
The rejection becomes the patient's problem first
The pharmacist runs the patient's prescription through the pharmacy benefit system. Instead of a payable claim, the response may include a reject code indicating that the medication needs prior authorization, that the drug isn't covered, that a preferred alternative must be tried, or that the quantity exceeds the plan's limit. The message shown to the pharmacy may be abbreviated and may not explain the clinical documentation the payer expects.
The pharmacy places the prescription on hold. Staff may contact the prescriber through a fax, telephone call, electronic pharmacy message, or payer-linked portal. The patient may see only one part of this chain: a medication that isn't ready and a request to contact the doctor.
That communication gap matters. The pharmacist often knows that the claim failed, but not whether the prescriber has received the payer's criteria. The practice may receive a fax without a clear indication of whether the issue is a simple quantity correction or a full clinical review. The patient assumes one organization owns the entire problem, while responsibility is split across the pharmacy, prescriber, payer, and pharmacy benefit manager.
Practical rule: Treat every pharmacy rejection as an access event that needs an owner, not as a message waiting for someone to interpret later.
Soft and hard rejects require different responses
A soft reject may allow the pharmacist to resolve the issue through an override, clarification, quantity adjustment, or direct outreach. For example, the pharmacy may be able to correct a billing detail or ask the prescriber to resend a prescription that fits the plan's limits. A pharmacist-initiated intervention can sometimes prevent a formal prior authorization from entering the clinic queue.
A hard reject generally requires prescriber action. The pharmacy can't override the payer's clinical requirement, and the clinic must submit information such as diagnosis, treatment history, laboratory findings, or evidence that preferred alternatives weren't appropriate. Staff should record the exact rejection message and any reference number before contacting the payer or pharmacy.
The distinction isn't always obvious from a fax. A practice that treats every message as a standard prior authorization may waste time on an issue the pharmacist could resolve. A practice that assumes every rejection is administrative may miss a hard clinical requirement and delay treatment further.
The counter is the first handoff
Prior authorization expanded steadily in Medicare Part D. One industry summary reported that it applied to 8% of covered drugs in 2007 and 24% in 2019, while Medicare prescription drug plans and Medicare Advantage prescription drug plans reached 28% and 26% of drugs subject to prior authorization in 2021, respectively (industry summary of prior authorization utilization). Specialty drugs face a heavier burden, with prevalence above 40% in several therapeutic areas, including multiple sclerosis, chronic myeloid leukemia, multiple myeloma, psoriasis, and rheumatoid arthritis, according to the same cited analysis.
The pharmacy counter therefore isn't an edge case. It's often the front door to a workflow that affects specialty care, maintenance therapies, and new prescriptions alike.
How Pharmacy Prior Authorization Works
Start with the claim, not the form
At the pharmacy counter, the process starts with a rejected claim, not a completed authorization form. The sequence usually looks like this, although payer portals and pharmacy benefit managers can change who handles each step:
The prescription reaches the pharmacy. The pharmacy submits the claim to the patient's pharmacy benefit. If prior authorization is required, the response identifies the coverage obstacle and may indicate whether the issue involves authorization, coverage, routing, or another claim condition.
The clinic confirms the requirement. Staff should verify the rejection reason, payer, member information, drug, strength, quantity, and dispensing pharmacy. An outdated insurance record or incorrect payer can create what appears to be a clinical problem.
The request is initiated. The pharmacy may start the request, or prescriber staff may submit it through an electronic portal, EHR workflow, fax, or telephone process. The practice needs to confirm which route the payer accepts for that product and plan.
The payer reviews the criteria. Reviewers may assess diagnosis, labeled use, prior treatment, contraindications, laboratory findings, quantity, and prescriber information. Some requests can be resolved from the submitted records. Others require clarification, an appeal, or a peer-to-peer conversation.
The pharmacy receives the decision. Approval does not dispense the medication automatically. The pharmacy still has to reprocess the claim, confirm the prescription is routed correctly, and address any remaining cost, network, quantity, or availability issue.
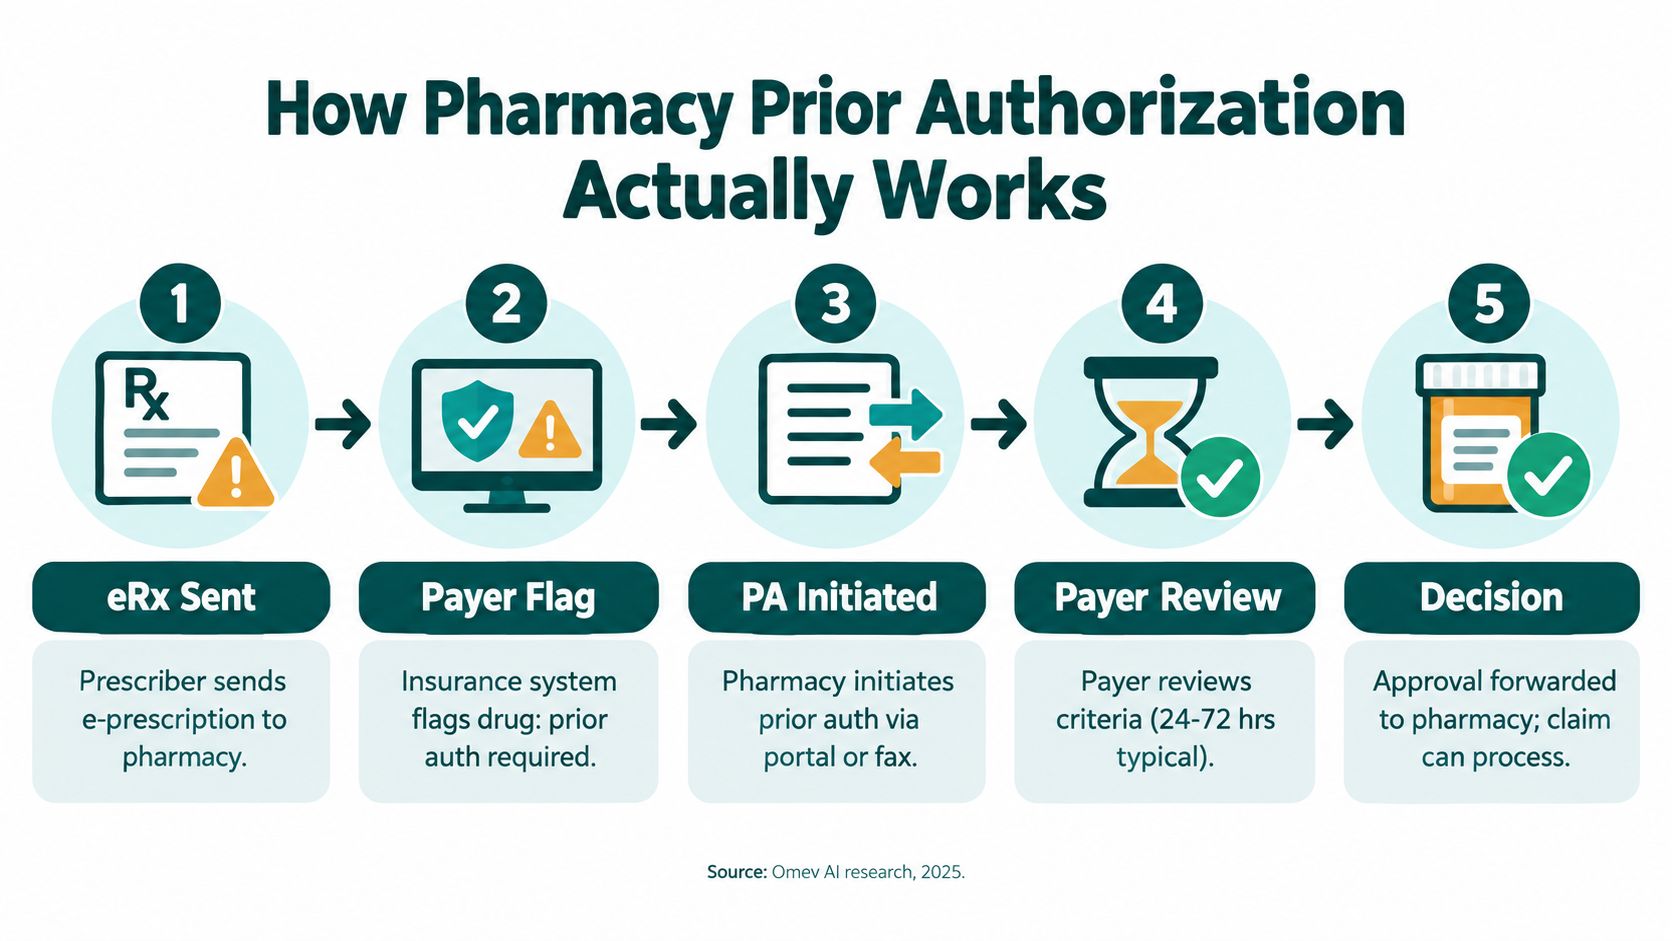
Match documentation to the payer's question
Build the request around the specific coverage rule rather than a generic clinical narrative. If the payer asks whether the patient tried a preferred drug, provide the medication name, dose, dates, response, and reason for discontinuation. If it requests a laboratory value, submit the result, date, and relevant reference information. For use outside the labeled indication, explain the medical rationale and supporting evidence without claiming that the plan covers more than its policy allows.
A new start may require the initial diagnosis and baseline documentation. A maintenance medication may require evidence of continued response, adherence, monitoring, or prior approval history. Staff should check the authorization's expiration date and determine whether the next request is a renewal instead of a new submission.
The pharmacy benefit manager generally administers coverage for drugs dispensed through a pharmacy. A medication administered in a clinic may route through the medical benefit instead, with different forms, coding, vendors, and review rules. The same active ingredient can therefore follow different authorization paths based on its formulation, administration site, and billing method.
For a plain-language explanation of the operational handoffs, practices can review PatientNotes prior authorization insights. Practices serving Medicaid patients may also need Medicaid prior authorization support, since portal requirements, state rules, and renewal processes can differ.
A pharmacy prior authorization utilization analysis reported that approximately 70% of prior authorization requests begin at the pharmacy after a rejected claim. In the same transaction-level evidence, only 7% were approved on the patient's first fill attempt, while 54% were ultimately approved. The practical lesson is direct: capture the rejection early, assign follow-up, and track the claim through the pharmacy's next billing attempt. A “submit and wait” workflow leaves too many requests stalled between the counter and the clinic.
Common Denial Reasons and How to Address Them
Denials fall into two practical groups. Clerical denials involve member details, prescriber identifiers, incomplete forms, wrong pharmacy routing, or missing signatures. Clinical denials involve medical criteria, preferred alternatives, diagnosis, quantity, or evidence. Route clerical issues to the staff member who can correct the transaction. Send clinical disputes to the prescriber or clinical reviewer.
The strongest appeal doesn't argue that the drug is generally valuable. It explains why this patient meets the plan's stated criteria and why the requested treatment is appropriate now.
| Denial reason | What the payer wants | Documentation to submit | Typical outcome with strong evidence |
|---|---|---|---|
| Step therapy not met | Proof that preferred alternatives were tried or aren't appropriate | Medication history, dates, doses, response, adverse effects, and contraindications | The payer may approve after the sequence is documented or an exception is supported |
| Diagnosis doesn't match labeled criteria | A covered diagnosis or a substantiated exception | Assessment, relevant chart notes, diagnostic findings, and a focused medical-necessity explanation | The request may be reconsidered if the diagnosis was entered incorrectly or the exception is allowed |
| Quantity exceeds plan limits | A reason the higher quantity is clinically necessary | Dosing rationale, treatment schedule, prior response, and the plan's applicable limit | A corrected quantity may process, or an exception review may follow |
| Drug is non-formulary | Medical necessity for an exception | Preferred-drug history, intolerance, contraindications, and supporting clinical literature when relevant | Approval depends on the plan's exception criteria |
| Lab values are missing | Objective evidence tied to the policy | Dated laboratory results, relevant ranges, and interpretation in the clinical record | A complete submission can resolve an otherwise incomplete review |
| Preferred alternative failure isn't documented | A clear record of treatment failure | Chart notes showing inadequate response, adverse effects, or clinical unsuitability | The payer may accept the exception when the record directly answers the requirement |
Write to the criterion
A useful appeal sentence has three parts: the patient's condition, the failed or unsuitable alternative, and the requested exception. For example: “The patient has [diagnosis] and experienced [documented response or adverse effect] with [preferred alternative] during [treatment period]. Because [specific clinical reason], I'm requesting coverage of [drug and dose] under the plan's medical-necessity exception.”
Don't attach a large undifferentiated chart and expect the reviewer to find the answer. Highlight the relevant visit note, medication history, laboratory result, and prior authorization reference. Peer-reviewed evidence can support the rationale when the plan permits it, but published literature won't repair a missing diagnosis or an absent treatment history.
Practices should maintain a payer-specific denial log. Record the drug, plan, rejection reason, missing item, submission route, decision, and next action. Over time, that log can reveal recurring clerical errors, outdated templates, or payer criteria that staff should check before the prescription reaches the pharmacy.
A dedicated insurance prior authorization workflow can help separate intake, clinical review, submission, follow-up, and appeal ownership. The value comes from consistent execution, not from assigning every denial to the same person.
Urgency Pathways and Decision Timeframes
At the pharmacy counter, a patient may have only a few doses left when the claim rejects. The practice should choose the response based on clinical urgency, drug type, payer rules, and current supply. “Urgent” means that standard processing could materially affect care or cause an inappropriate interruption. It does not mean the office wants a quicker answer.
| Pathway | Typical timeframe | Qualifying criteria | Federal coverage under CMS-0057-F |
|---|---|---|---|
| Standard | Payer-specific, often several business days or longer | Routine initiation, renewal, or exception request without immediate clinical risk | CMS requires 7 calendar days for covered standard requests, but the rule's decision-time requirements do not apply to drugs |
| Expedited | Payer-specific and clinically justified | Delay could seriously jeopardize the patient's life, health, or ability to regain maximum function | CMS requires 72 hours for covered expedited requests, with the drug exception noted above |
| Emergency supply or emergency route | Defined by payer or state program | The patient needs temporary access while formal review is pending | Rules vary by program and state, so staff must verify the applicable requirement |
The table requires careful interpretation. CMS's final rule applies to Medicare, Medicaid, CHIP, and Marketplace payers covered by the rule. CMS states that covered payers will generally need to implement prior authorization API requirements beginning January 1, 2027. The rule also requires specific denial reasons beginning in 2026, while its decision-time requirements do not apply to drugs. See the CMS interoperability and prior authorization final rule.
A Medicare Advantage or Medicaid patient therefore does not automatically receive a seven-day or 72-hour pharmacy decision. Staff must confirm whether the request concerns a drug or a service, whether the payer falls within the rule, and which pharmacy-benefit standards the plan applies.
Use a defensible urgency note
An expedited request should describe the risk of delay rather than rely on the word “urgent.” Include the diagnosis, current symptoms or treatment status, medication, consequence of interruption or delay, and requested response time. The prescriber makes the clinical judgment. Staff must send the explanation with the supporting records and confirm that the payer received them.
For Medicare Advantage Part D drugs, the plan's expedited process may use a faster window than the federal rule described above. Medicaid programs may provide emergency supplies under state or plan rules. Commercial plans differ, so staff should follow the plan's published instructions and document the representative's name, call reference, date, and promised timeframe.
The counter outcome still depends on follow-up. A request marked urgent can remain unresolved if the pharmacy, payer, and practice do not share the same status, so assign ownership for checking the claim and updating the patient.
Electronic Prior Authorization and the Federal Rule Shift
Electronic prior authorization can remove manual handoffs, but it does not remove payer criteria or incomplete records. A useful setup connects prescribing with benefit information, identifies requirements before the patient reaches the pharmacy, and carries structured clinical data into the request. That timing matters at the counter, where an unresolved electronic request can still become a rejected claim or an abandoned prescription.
Common components include NCPDP SCRIPT transactions for pharmacy-benefit workflows, payer portals for plans that use a different route, and EHR prompts that appear when a prescriber selects a medication. Electronic benefit verification and real-time prescription benefit tools can show coverage conditions, restrictions, or a prior authorization flag earlier in prescribing. They also expose a practical trade-off. A covered alternative may be easier to obtain, while the clinically preferred drug may require a complete exception request.

What the federal rule changes
CMS's rule addresses interoperability and prior authorization for covered medical items and services. It requires affected Medicare Advantage, Medicaid managed care, CHIP, and certain Marketplace payers to support applicable APIs and provide decision information within specified timeframes. The rule's decision-time provisions do not cover pharmacy-benefit drug decisions, so practices must separate medical-service requirements from drug-authorization procedures. The CMS implementation information explains the implementation timeline and scope.
The timeline spans the 2026 denial-reason requirements and API deadlines beginning in 2027. For pharmacy teams, the operational question remains immediate: which requests follow federal requirements, and which follow the plan's pharmacy process? A portal may be electronic while still requiring manual document selection, separate credentials, or a phone call. Electronic submission does not prove that the request is complete or that the pharmacy received the determination.
CMS's Part D guidance requires sponsors to submit utilization-management rules at the point of sale, including prior authorization, step therapy, and quantity limits that are not based on FDA maximum daily dose limits. It also identifies practices that are not allowable, including steering physicians or beneficiaries toward a sponsor's or PBM's mail-order pharmacy through prior authorization (CMS Part D Benefits Manual).
Automation still needs human review
Specialty injectables, biologics, oncology medicines, and other complex therapies often require information that the EHR does not structure reliably. A reviewer must confirm that the diagnosis, treatment history, laboratory findings, and requested dose match the payer's criteria. Practices should test whether electronic submissions produce traceable confirmations and whether staff can see pending, approved, denied, and expired requests in one queue.
The workable design is controlled automation. Software reduces repetitive entry, while staff handle clinical judgment, exceptions, patient communication, and escalation. That division protects the patient from a silent gap between electronic approval and what the pharmacy can dispense.
Templates and Workflow for Prescribers and Staff
A pharmacy prior authorization process works better when each handoff has a named owner. The prescriber makes the clinical decision. Staff gathers and transmits records. The pharmacy reports the claim response and dispensing status. A manager monitors aging requests and escalates exceptions.
Ready-to-use communication templates
Prescriber-to-pharmacy callback
“This is [practice name], calling about [patient name or identifier] and [drug, strength, and quantity]. Please provide the exact reject message, the payer reference number, whether this is a soft or hard reject, and the accepted submission route. We'll confirm the next action and document it in the patient's authorization record.”
Prescriber-to-payer medical-necessity request
“Patient: [name]. Diagnosis: [diagnosis and ICD-10]. Requested medication: [drug, strength, dose, and quantity]. Preferred alternatives tried: [names, dates, doses, response, and reason stopped]. Relevant laboratory values: [test, result, and date]. Clinical reason for exception: [concise patient-specific rationale]. Please review under the plan's applicable exception criteria.”
Patient message when treatment is delayed
“Your pharmacy reported that the insurance plan requires prior authorization for [medication]. Our office has submitted the request or is gathering the information needed to submit it. We'll update you when we receive a decision. Please contact us promptly if you're running out of an existing medication or if your condition worsens.”
The patient message should never promise approval or imply that the pharmacy alone controls the timeline. Practices can adapt these scripts alongside top business process documentation templates to create consistent internal procedures.
Assign work by role
| Role | Primary responsibility | Required handoff |
|---|---|---|
| Prescriber | Confirm indication, clinical urgency, alternatives, and medical rationale | Signs or approves the request and participates in peer-to-peer review when needed |
| MA or LPN | Gather chart notes, medication history, laboratory results, and payer details | Sends a complete packet to the authorization queue |
| Prior authorization specialist | Submit, track, respond, appeal, and document every status change | Reports pending, denied, approved, and aging requests to the practice manager |
| Pharmacy technician | Capture the exact rejection, reference number, and pharmacy status | Communicates whether the claim processed and whether the medication is available |
| Front office or patient coordinator | Notify the patient and confirm pickup or next pharmacy action | Records contact attempts and unresolved barriers |
A remote authorization specialist can fit into this model when request volume is uneven, staff coverage is limited, or clinicians are spending time on payer follow-up. The role should have restricted access, documented escalation rules, and no authority to make a clinical decision. Practices evaluating that option can review the responsibilities of a prior authorization specialist.
Workstation checklist
- Capture the rejection: Record the exact message, date, pharmacy, payer, drug, quantity, and reference number.
- Classify the issue: Mark it clerical, clinical, soft reject, hard reject, renewal, standard, or expedited.
- Confirm ownership: Assign one staff member and a due date.
- Collect evidence: Attach the diagnosis, treatment history, labs, and relevant chart note.
- Submit and verify: Save the confirmation number and submission route.
- Schedule follow-up: Set a payer-specific check date instead of relying on memory.
- Escalate deliberately: Contact the payer when the stated timeframe passes or the request remains untraceable.
- Close the loop: Confirm approval, claim adjudication, pharmacy availability, patient notification, and pickup status.
Track submission time, decision time, denial reason, appeal status, and final fill outcome. A workflow can't improve what the practice doesn't record.
Why Approval Does Not Always Mean the Patient Fills
A payer approval can arrive while the prescription still sits unresolved at the pharmacy. In transaction-level evidence involving 205,896 branded medication dispensations initially rejected for prior authorization, 35% were processed in one day. The remaining 65% took a median of 6 days to resolve, and only 54% were ultimately approved. Approval is therefore a midpoint, not proof that treatment started.
The final barrier may be the pharmacy claim, the patient's cost, network routing, inventory, transportation, or uncertainty about the next step. A patient may hear that the authorization was approved but receive no call that the prescription is ready. A specialty medication may need transfer to an in-network pharmacy. A later refill can fail because the authorization expired or the approved quantity was exhausted.
Find the dropout point
Keep the case open until the dispensing process has been checked. A practical post-decision sequence includes:
- Same decision day: Confirm that the approval reached the dispensing pharmacy and that the claim processes.
- Next business-day check: Ask whether the medication is available and whether the patient has been notified.
- Patient contact: Confirm the expected pickup, delivery, specialty-pharmacy transfer, or remaining barrier.
- Exception handling: Send cost, network, or clinical questions to the appropriate staff member.
- Renewal planning: Record the authorization expiration and begin renewal work before the final fill is at risk.
A useful dashboard separates approved, filled, picked up, transferred, patient unreachable, and abandoned. Those categories identify whether the practice has a submission problem or a post-approval access problem. The counter is where that distinction becomes visible.
The systematic review in the Journal of Managed Care & Specialty Pharmacy found that pharmacy prior authorization can delay treatment initiation by 3.6 to 31 days, depending on drug class, with payer processing times ranging from 6.7 to 21 days (systematic review of prior authorization delays). The operational implication is clear: staff must follow the request after submission and continue checking after approval.
A tightly controlled workflow can produce a different result. A multicenter retrospective study of 1,744 specialty-medication submissions found a mean turnaround time of 2.1 days in an integrated, electronic, centralized specialty-pharmacy process (peer-reviewed electronic prior authorization study). That result is not a promise for every practice. It shows how completeness checks, standardized documentation, centralized tracking, and immediate escalation can shorten delays.
Ask one practical question: “Where did access stop?” If staff cannot answer, the authorization was not managed to completion.
The 2025 Surescripts survey found that 29% of patients reported a prior-authorization delay in the previous 12 months, rising to 36% among patients taking two or more daily prescriptions (Surescripts prior authorization survey). Those patient-reported results support follow-up after approval as part of access management, rather than an optional courtesy.
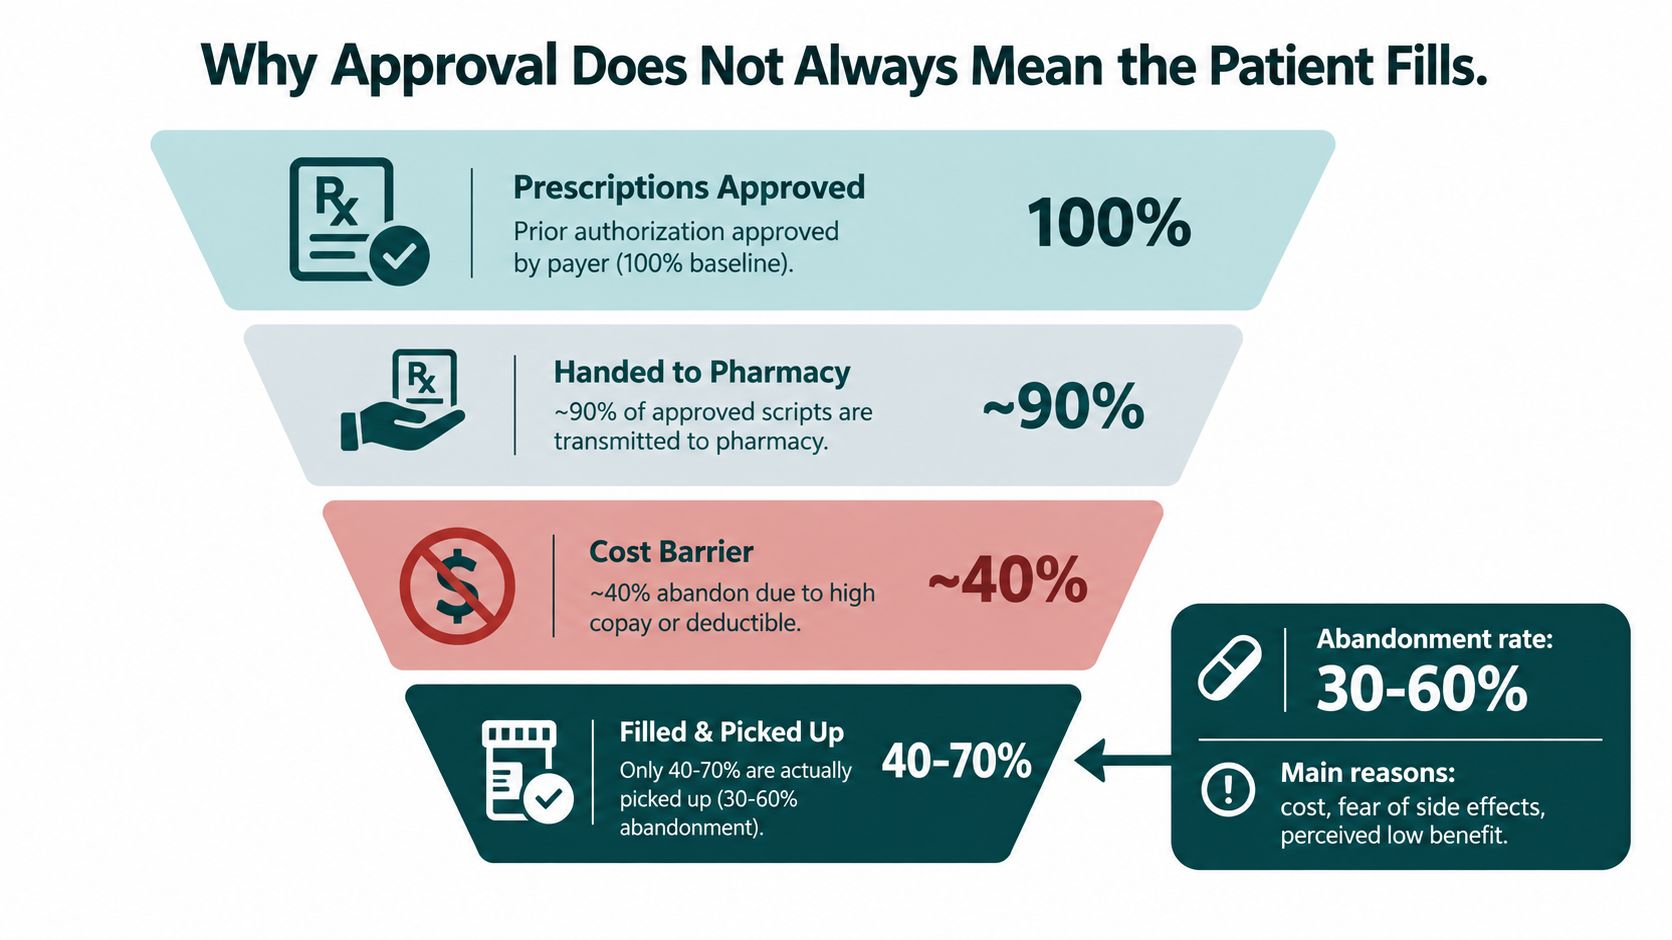
The Takeaway
Pharmacy prior authorization begins at the counter, but it ends only when the patient can obtain and use the medication. Practices should capture the exact rejection, assign ownership, submit evidence that answers the payer's criteria, monitor the decision, and confirm the pharmacy claim and patient pickup.
Build the workflow around the points where requests fail, especially unclear handoffs, incomplete documentation, missed follow-up, and post-approval barriers. Review payer-specific rules regularly, distinguish pharmacy-benefit drug requirements from medical-benefit processes, and confirm how CMS requirements apply to the particular request before promising a timeframe.
MedicalVirtual connects U.S. medical practices with pre-vetted LATAM staff who can handle prior authorization submission, tracking, payer follow-up, and patient-status communication during your clinic hours. If your team needs consistent ownership of the authorization queue, visit MedicalVirtual to discuss the role and workflow that fit your practice.
On a typical Tuesday in a four-physician primary care group, the day doesn't end at 5 p.m. The front desk is still returning calls, billing is waiting on signed encounters, and one clinician is staring at a screen at 8 p.m. trying to finish charts that should've closed hours ago. That's the problem virtual scribe services are built to solve, they separate the cognitive work of the visit from the clerical work of documentation so the clinician can move on after clinic instead of carrying the chart home.
In plain terms, a virtual scribe listens to, or reviews, the encounter, turns the conversation into an EMR-ready note, stages the useful parts of the visit, and routes the draft for clinician review and sign-off. In practice, that can mean fewer late-night charting sessions, cleaner same-day closure, and less friction between the exam room and the billing team. It does not mean the scribe takes over coding decisions, prior authorizations, or inbox triage, those are different jobs and they should stay separate unless you've explicitly scoped the role that way.
The right answer for most practices isn't “scribe or no scribe.” It's choosing the model that fits your visit type, your EMR, your oversight capacity, and your tolerance for rework. If you're also comparing broader remote staffing options, top platforms for virtual assistants can help you think about the market in a wider way, while a role-specific comparison like medical assistant vs medical scribe helps clarify where documentation support ends and clinical-adjacent admin begins.
What Virtual Scribe Services Actually Do for a Practice
On a practical level, a virtual scribe is there to keep the provider focused on the patient while someone else handles the note structure. In many clinics, that means the scribe is capturing the history, organizing the assessment, staging the plan, and keeping the EMR populated so the clinician isn't starting from a blank screen after each visit. That workflow matters because the most expensive part of documentation isn't the typing, it's the interruption, the mental switching, and the backlog that builds when charts don't close on time.
A good scribe doesn't just transcribe. They understand the note format your practice uses, know which fields matter for your specialty, and leave enough room for the clinician to edit the parts that require judgment. That's why practices should think of scribing as a workflow design choice, not a staffing shortcut. If the note lands in the chart but creates more clean-up later, the practice hasn't reduced burden, it's moved it.
What usually sits inside the scribe role
A well-scoped virtual scribe often handles the note draft, pulls forward relevant chart history, and stages the encounter in the EMR for review. In some settings, the scribe also queues follow-up items for sign-off, such as orders, referrals, or patient instructions, depending on the practice's policy and EMR permissions. The key is that the clinician stays responsible for the final content and any action that requires licensed judgment.
Practical rule: if a task affects diagnosis, treatment choice, or billing authority, keep it under clinician control unless your compliance team has explicitly approved a narrower support role.
That distinction matters because the biggest mistakes I see come from blurred expectations. A practice hires for “documentation support,” then expects the scribe to cover inbox messages, prior auth, coding, and scheduling cleanup too. The result is slow response times, inconsistent notes, and a frustrated team that never agreed on what “scribe” meant in the first place.
If you're comparing models beyond a pure scribe function, remember that some remote staff can cover adjacent work like patient coordination or reception, but that's a separate operating model. A virtual scribe should reduce charting load first, not become an all-purpose catchall for every admin gap in the clinic.
Real-Time, Asynchronous, and Ambient AI Models Compared
The workflow question matters more than the technology label. A human scribe joining the visit in real time, a human scribe working after the encounter, and an ambient AI tool all promise documentation relief, but they shift the work in different directions. One keeps the chart moving during the visit, one protects the clinician's flow but delays the note, and one cuts drafting time but often increases the clinician's review burden.
The choice gets sharper once you look at latency to closure. If your specialty needs the note ready before the next room turnover, real-time support often fits better. If your clinic can tolerate a later return of the note and wants to preserve the visit flow, asynchronous support can work. If your team is comfortable editing AI drafts and governing note quality closely, ambient AI may be a sensible option, but only if you're honest about oversight.
Where each model fits best
| Model | Where It Fits Best | Latency to Note Closure | Common Failure Mode |
|---|---|---|---|
| Real-time human scribe | Procedural and high-acuity visits, clinics that need immediate note readiness | During or immediately after the visit | Distraction if the clinician multitasks or the audio feed is poor |
| Asynchronous human scribe | Primary care, routine outpatient visits, practices that can accept delayed closure | Later the same day or by an agreed SLA | Missed nuance when the visit depends on context that isn't obvious from the recording |
| Ambient AI scribe | High-volume documentation-heavy settings with strong clinician review habits | Fast draft, then clinician sign-off | Incorrect details, overconfident phrasing, or note bloat that needs editing |
That table makes the trade-off clearer than any vendor brochure. Real-time human scribes are often stronger when the physician wants the chart ready before moving on, but they depend on stable audio and a disciplined visit flow. Asynchronous scribes protect the pace of the appointment, but they move the burden to the end of the day. Ambient AI can be fast, but its value rises or falls on how well the practice reviews what it creates.
The real question isn't whether scribing helps. It's which workflow gets the note closed with the least rework.
For practices that care about same-day closure, the practical test is simple, not theoretical. Pick the model that your clinicians can sustain on a busy day without creating a second job for themselves at night. The cheapest option on paper can become the most expensive one if it adds clean-up time, coding uncertainty, or a steady stream of edits.
Connecting Scribes to Your EMR Without Breaking the Workflow
Most implementation failures start with access. If a scribe has too much access, you create privacy and audit problems. If they have too little access, they end up working around the EMR instead of inside it, which defeats the point. The clean setup is usually a role-based access model with unique credentials, limited templates, and a permissions matrix that spells out exactly what the scribe can see and stage.
The next layer is the documentation environment itself. Smart phrases, note templates, problem list staging, medication reconciliation, and order queues all need to be mapped before go-live. If your practice uses Epic, athenaOne, or eClinicalWorks, the implementation questions are less about whether the system can store text and more about whether the scribe can work inside the exact fields your clinicians rely on without creating clutter or bypassing controls.
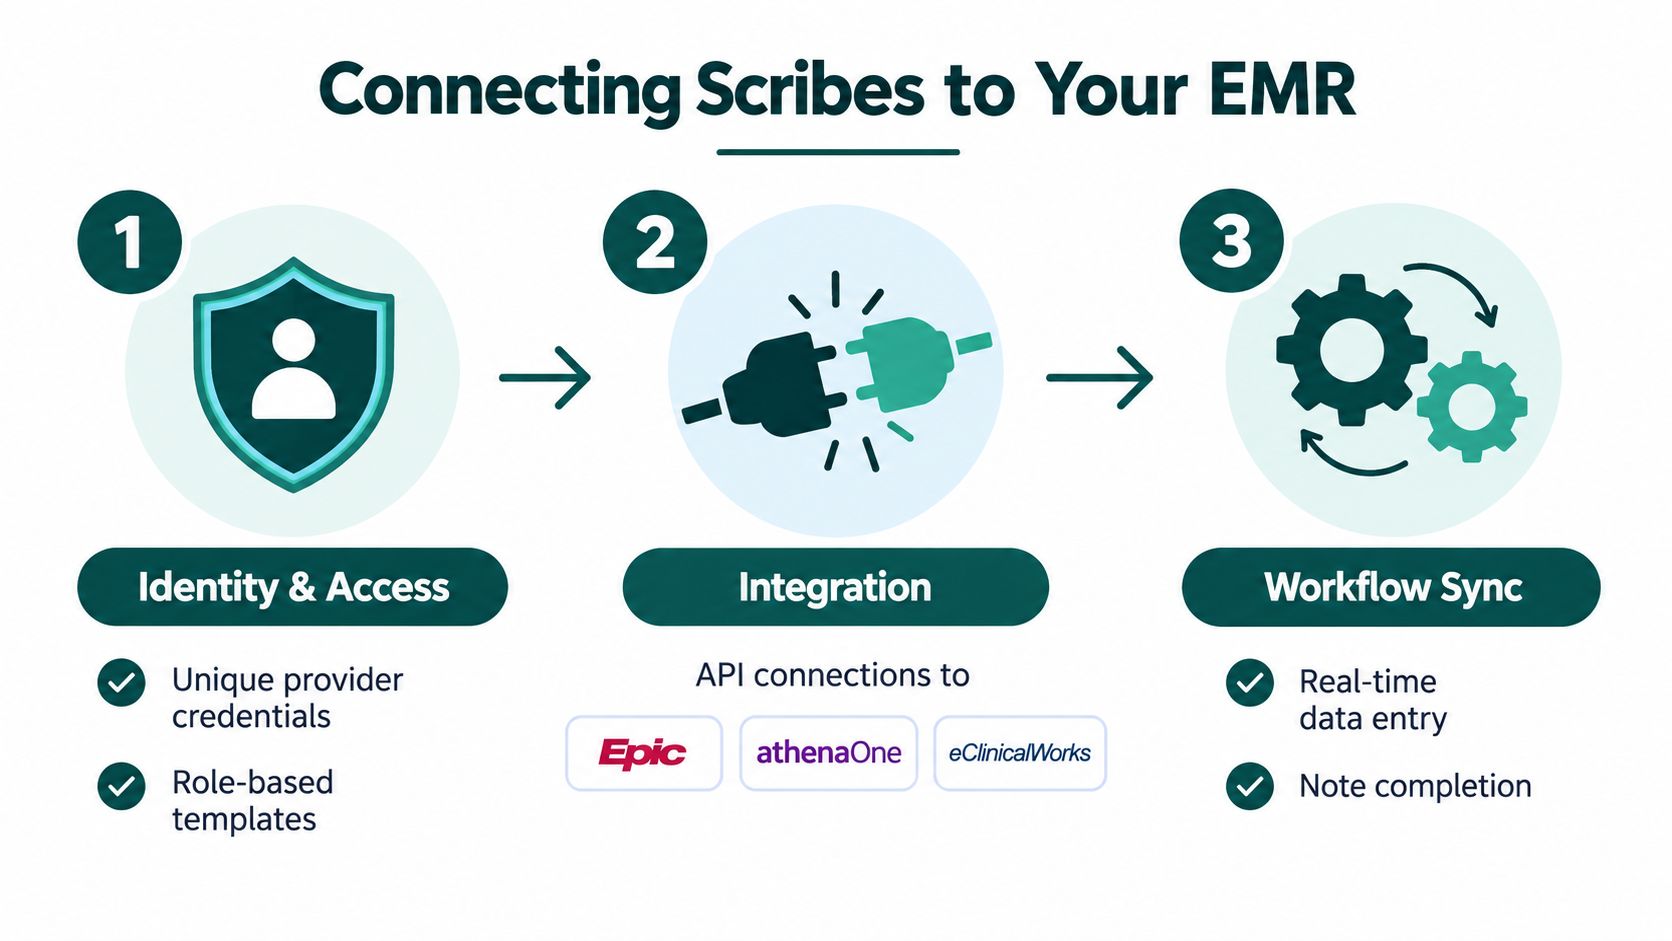
The access model that keeps you sane
Start with unique logins and least privilege. The scribe should have the schedule, chart sections, and template access needed to do the job, but not billing controls, admin settings, or anything that could expose more chart data than necessary. Two-factor authentication should be standard, and session timeouts should be enforced on shared workstations or remote access sessions.
Then define what the scribe can stage versus what the clinician must complete. In many practices, the scribe can prepare history, exam, and plan sections, but the provider still has to verify diagnoses, sign orders, and finalize anything that affects treatment. That split keeps the chart moving while preserving accountability where it belongs.
What to build before go-live
- Permissions matrix: list which note sections, orders, and patient-facing outputs the scribe can touch.
- Consent workflow: decide how the patient is informed that a scribe is involved and how consent is documented.
- Audit review cadence: decide who checks logs, how often, and what triggers an escalation.
- Offboarding checklist: revoke access immediately, rotate shared passwords if used, and review recent chart activity.
The end of the engagement matters too. A scribe should lose access the moment the relationship ends, not at the next billing cycle. That last-month activity review is one of the easiest ways to catch lingering permissions or unusual chart access before they become a bigger issue.
What the Research Actually Shows on Time Saved and Burnout
The evidence is more useful when you look at it as operations data instead of marketing copy. In a 144-physician, two health-system quality-improvement study, virtual scribes were associated with a mean reduction of 5.6 minutes of total EHR time per appointment, 1.3 minutes of note time per appointment, and 1.1 minutes of “pajama time” per appointment, with all three changes statistically significant, according to the study linked in the brief. That's the kind of shift that can matter when the backlog is cumulative rather than occasional.
Another pilot found a more modest but still meaningful change, with average time in notes per appointment falling from 8.54 minutes to 7.04 minutes over 30 days, while the authors reported positive movement in quality, time savings, burnout, and productivity. A separate ambient AI study reported a 20.4% reduction in time spent in notes per appointment, from 10.3 minutes to 8.2 minutes, along with a 9.3% increase in same-day appointment closure and a 30.0% reduction in after-hours documentation. Those outcomes matter because they point to the metrics practices feel, not just the software dashboard.
What transfers, and what doesn't
The benefit tends to transfer more cleanly in primary care and general internal medicine, where notes are structured enough for a scribe to learn the pattern. It's less predictable in specialties where the visit content is more variable, the assessment is more complex, or the documentation carries more medicolegal nuance. That doesn't mean scribes don't work there, it means the practice has to match the workflow to the visit type instead of assuming one setup fits all.
Burnout is harder to measure cleanly. Some studies report meaningful relief, others show smaller or inconsistent shifts, and a few note that productivity doesn't always rise even when documentation time falls. For an operations lead, the more reliable signals are total EHR time, chart closure latency, addenda volume, and the amount of patient-facing time a clinician gets back.
| Study / Source | Setting | Minutes Saved per Encounter | Same-Day Closure Change | Burnout / Time-Burden Effect |
|---|---|---|---|---|
| Two-system QI study | 144 physicians across two health systems | 5.6 minutes total EHR time, 1.3 minutes note time | Not reported in the verified data | 1.1 minutes less pajama time, statistically significant |
| 30-day virtual scribe pilot | Mixed outpatient pilot | 8.54 to 7.04 minutes in notes | Not reported in the verified data | Positive movement in quality, time savings, burnout, and productivity |
| Ambient AI scribe study | Outpatient documentation workflow | 10.3 to 8.2 minutes in notes | 9.3% increase | 30.0% reduction in after-hours documentation |
| AI medical scribe study | Mixed workflow | Not reported in the verified data | 3% decrease in same-day chart closure | Other documentation measures improved, which shows closure and speed don't always move together |
A useful caution is that many studies measure short pilot periods, not the messier reality of steady-state use. A tool can look excellent in a funded rollout and still create more cleanup later if the templates are too loose or the specialty fit is weak. That's why the chart closure rate and note quality need to be tracked together, not treated as separate conversations.
HIPAA, Business Associate Agreements, and Data Safeguards
A virtual scribe that sees PHI turns compliance into a workflow question, not a theory exercise. The HHS business associate agreement provisions require downstream service providers to use appropriate safeguards against unauthorized use or disclosure, including Security Rule safeguards for electronic PHI, and to report any non-permitted use or disclosure, including breaches of unsecured PHI, according to HHS guidance on BAA provisions. That means the vendor relationship needs to be written down, reviewed, and enforceable.
The contract should say what PHI can be used for, how subcontractors are handled, how breach notice works, and what happens to data when the agreement ends. On the operational side, I look for encryption in transit and at rest, role-based access, session timeouts, and a clear ban on local downloads to personal devices. If a vendor cannot explain those controls without jargon, they are not ready for patient data.
What to verify before you let a scribe touch the chart
The best checks are practical. Ask for workforce training records, background screening documentation, and a clear map of where the work is routed. If you are comparing domestic-only support with offshore coverage, decide whether that model is allowed at all and whether patients are told when it matters.
A short access audit before go-live catches more problems than a polished policy packet. I also recommend a two-week review of who accessed what, when, and why, because weak permissions and sloppy handoffs show up there before they become reportable incidents. For a plain-language reference on the contract side, the HIPAA BAA requirements guide is useful while you review language, not just policy headings.
For a broader checklist on vendor controls, the HIPAA-compliant virtual assistants guide helps separate marketing claims from the controls a practice should verify.
Practical rule: if the vendor cannot show who accessed what, when, and why, the security review is not finished.
Do not accept the phrase “HIPAA certified” in vendor conversations. HHS does not issue that kind of certification. Ask for evidence of controls, contract terms, and a real process for handling mistakes when they happen.
Quality Controls That Protect Notes and Coding Accuracy
Faster notes aren't automatically better notes. If the scribe drafts a clean-looking chart that still misses nuance, inflates wording, or creates cleanup for coding, the practice has bought speed at the cost of rework. That's why quality control has to be built into the workflow from the start, not bolted on after someone notices a billing problem.
The simplest way to keep the process honest is a regular audit cadence. Weekly random chart pulls should be scored against a rubric that checks HPI completeness, assessment-plan alignment, copy-forward hygiene, and code specificity. Monthly, the billing team should reconcile scribed notes against coder output so the practice can see whether documentation quality is supporting revenue integrity rather than just making notes look full.
What to look for in the note itself
The most common problems are easier to spot than people think. Note bloat shows up as long repetitive ROS blocks that don't add clinical value. Hallucinated history appears when a scribe or AI draft inserts details that weren't said. Inconsistent attribution shows up when part of the note sounds clinician-authored and part sounds like someone else stitched it together.
If your practice uses macros heavily, governance matters. Templates should make documentation faster without manufacturing findings that weren't observed. That's especially important when the note feeds E&M level selection or supports a higher code than the encounter really justifies.
Escalation should happen before sign-off
When a same-day note misses nuance, the clinician of record needs a clear path to send it back before signing. That applies whether the draft came from a human, an asynchronous service, or an ambient AI tool. The scribe can help draft the note, but the clinician owns the final content and the legal responsibility for signing it.
For teams that want to keep documentation and revenue cycle closer together, medical billing services are often discussed alongside scribing because cleaner notes affect the next step in the workflow. That doesn't mean the same person should do both jobs, it means the documentation standard has to support the billing standard from the outset.
Pricing, ROI, and a 90-Day Implementation Plan
Pricing models vary, but the operating question should stay the same: what does a note cost once you include setup, review time, and rework? A monthly retainer may feel simple, a per-encounter fee may look flexible, and ambient AI subscriptions may appear inexpensive, but the cost shows up in closure speed, edits, and the amount of clinician time pulled back into documentation.
For cost comparison, one helpful outside reference is AI transcription pricing, but the better internal metric is your cost per completed visit note. That number should include the vendor fee, the time the clinician spends reviewing the chart, and any added work created for billing or compliance review. If you can't get to a cost per usable note, you're comparing quote sheets instead of workflows.
A simple 30 60 90 day rollout
- Days 1 to 30, pilot one provider and one visit type. Tune the template, define the BAA scope, and measure edit time alongside note closure.
- Days 31 to 60, expand to two more clinicians. Track rework, confirm whether the same templates work across styles, and adjust macros where they're creating clutter.
- Days 61 to 90, scale to the full panel. Shift to an in-house audit cadence and assign a single owner for vendor management and issue escalation.
A useful vendor scorecard is short and blunt. Ask about turnover, access logs, escalation path, and how quickly they can produce an audit trail when something looks off. If the vendor can't answer those four items cleanly, they're not ready for a practice that cares about same-day closure and documentation defensibility.
Hiring checkpoint: select for consistency, not just speed. A fast note that needs heavy cleanup is a slow process wearing a different label.
For practices exploring broader staffing support, MedicalVirtual places pre-vetted Latin America-based assistants who work U.S. clinic hours and can cover documentation, front-desk, billing, and coordination tasks as separate roles. For a scribe evaluation specifically, that matters because it gives you a way to compare dedicated documentation support against other remote coverage models without mixing job functions.
The Takeaway
The key question isn't whether virtual scribe services save time. It's which model matches your visit profile and your tolerance for review work. Real-time human scribes tend to fit procedural and high-acuity visits, asynchronous scribes fit routine outpatient work where delayed closure is acceptable, and ambient AI fits lean documentation environments only when the practice is willing to govern the output closely.
The decision becomes practical when you stop treating it as a technology contest and start treating it as a workflow and oversight problem. A properly scoped BAA, clear permissions, a defined audit cadence, and clinician sign-off on every note matter more than the brochure language. Track same-day closure and coding accuracy as the key ROI signals, because faster notes only help if they're also clean, billable, and defensible.
If you're evaluating whether a remote scribe, billing assistant, or front-desk role belongs in your clinic workflow, MedicalVirtual can help you scope the role and match it to your practice hours, specialty, and EMR setup. Visit MedicalVirtual to review the available staffing options and start with a role fit that's built around your current documentation bottlenecks.